EX-99.1
Published on September 15, 2026

Evommune Corporate Presentation September 2026 © Evommune, Inc.

Disclaimers This presentation has been prepared by Evommune, Inc. (“we”, “us” or “our”) and contains forward-looking statements, including: statements about our expectations regarding the potential benefits, clinical activity and tolerability of our product candidates; our expectations with regard to the results of our clinical trials, preclinical studies and research and development programs, including the potential therapeutic benefit of EVO756, EVO301 and EVO646, the design, objectives, initiation, timing, progress and results of current and future preclinical studies and clinical trials of our product candidates, including the ongoing and planned Phase 2 clinical trials for EVO756, EVO301 and EVO646; anticipated cash runway; and continued advancement of our portfolio. These statements involve substantial known and unknown risks, uncertainties and other factors that may cause our actual results, levels of activity, performance or achievements to be materially different from the information expressed or implied by these forward-looking statements. We may not actually achieve the plans, intentions or expectations disclosed in our forward-looking statements, and you should not place undue reliance on our forward-looking statements. Actual results or events could differ materially from the plans, intentions and expectations disclosed in the forward-looking statements we make. These and other risks are described more fully in our Annual Report on Form 10-K for the year ended December 31, 2025 and our other filings with the Securities and Exchange Commission (the “SEC”) and our other documents subsequently filed with or furnished to the SEC. All forward-looking statements represent our views as of the date of this presentation. All forward-looking statements contained in this presentation speak only as of the date on which they were made. Except to the extent required by law, we undertake no obligation to update such statements to reflect events that occur or circumstances that exist after the date on which they were made. This presentation also contains estimates made by independent parties relating to industry market size and other data. These estimates involve a number of assumptions and limitations, and you are cautioned not to give undue weight on such estimates. We have not independently verified the accuracy or completeness of such information and we do not take any responsibility with the accuracy or completeness of such information. The trademarks included in this presentation are the property of the owners thereof and are used for reference purposes only. © Evommune, Inc.
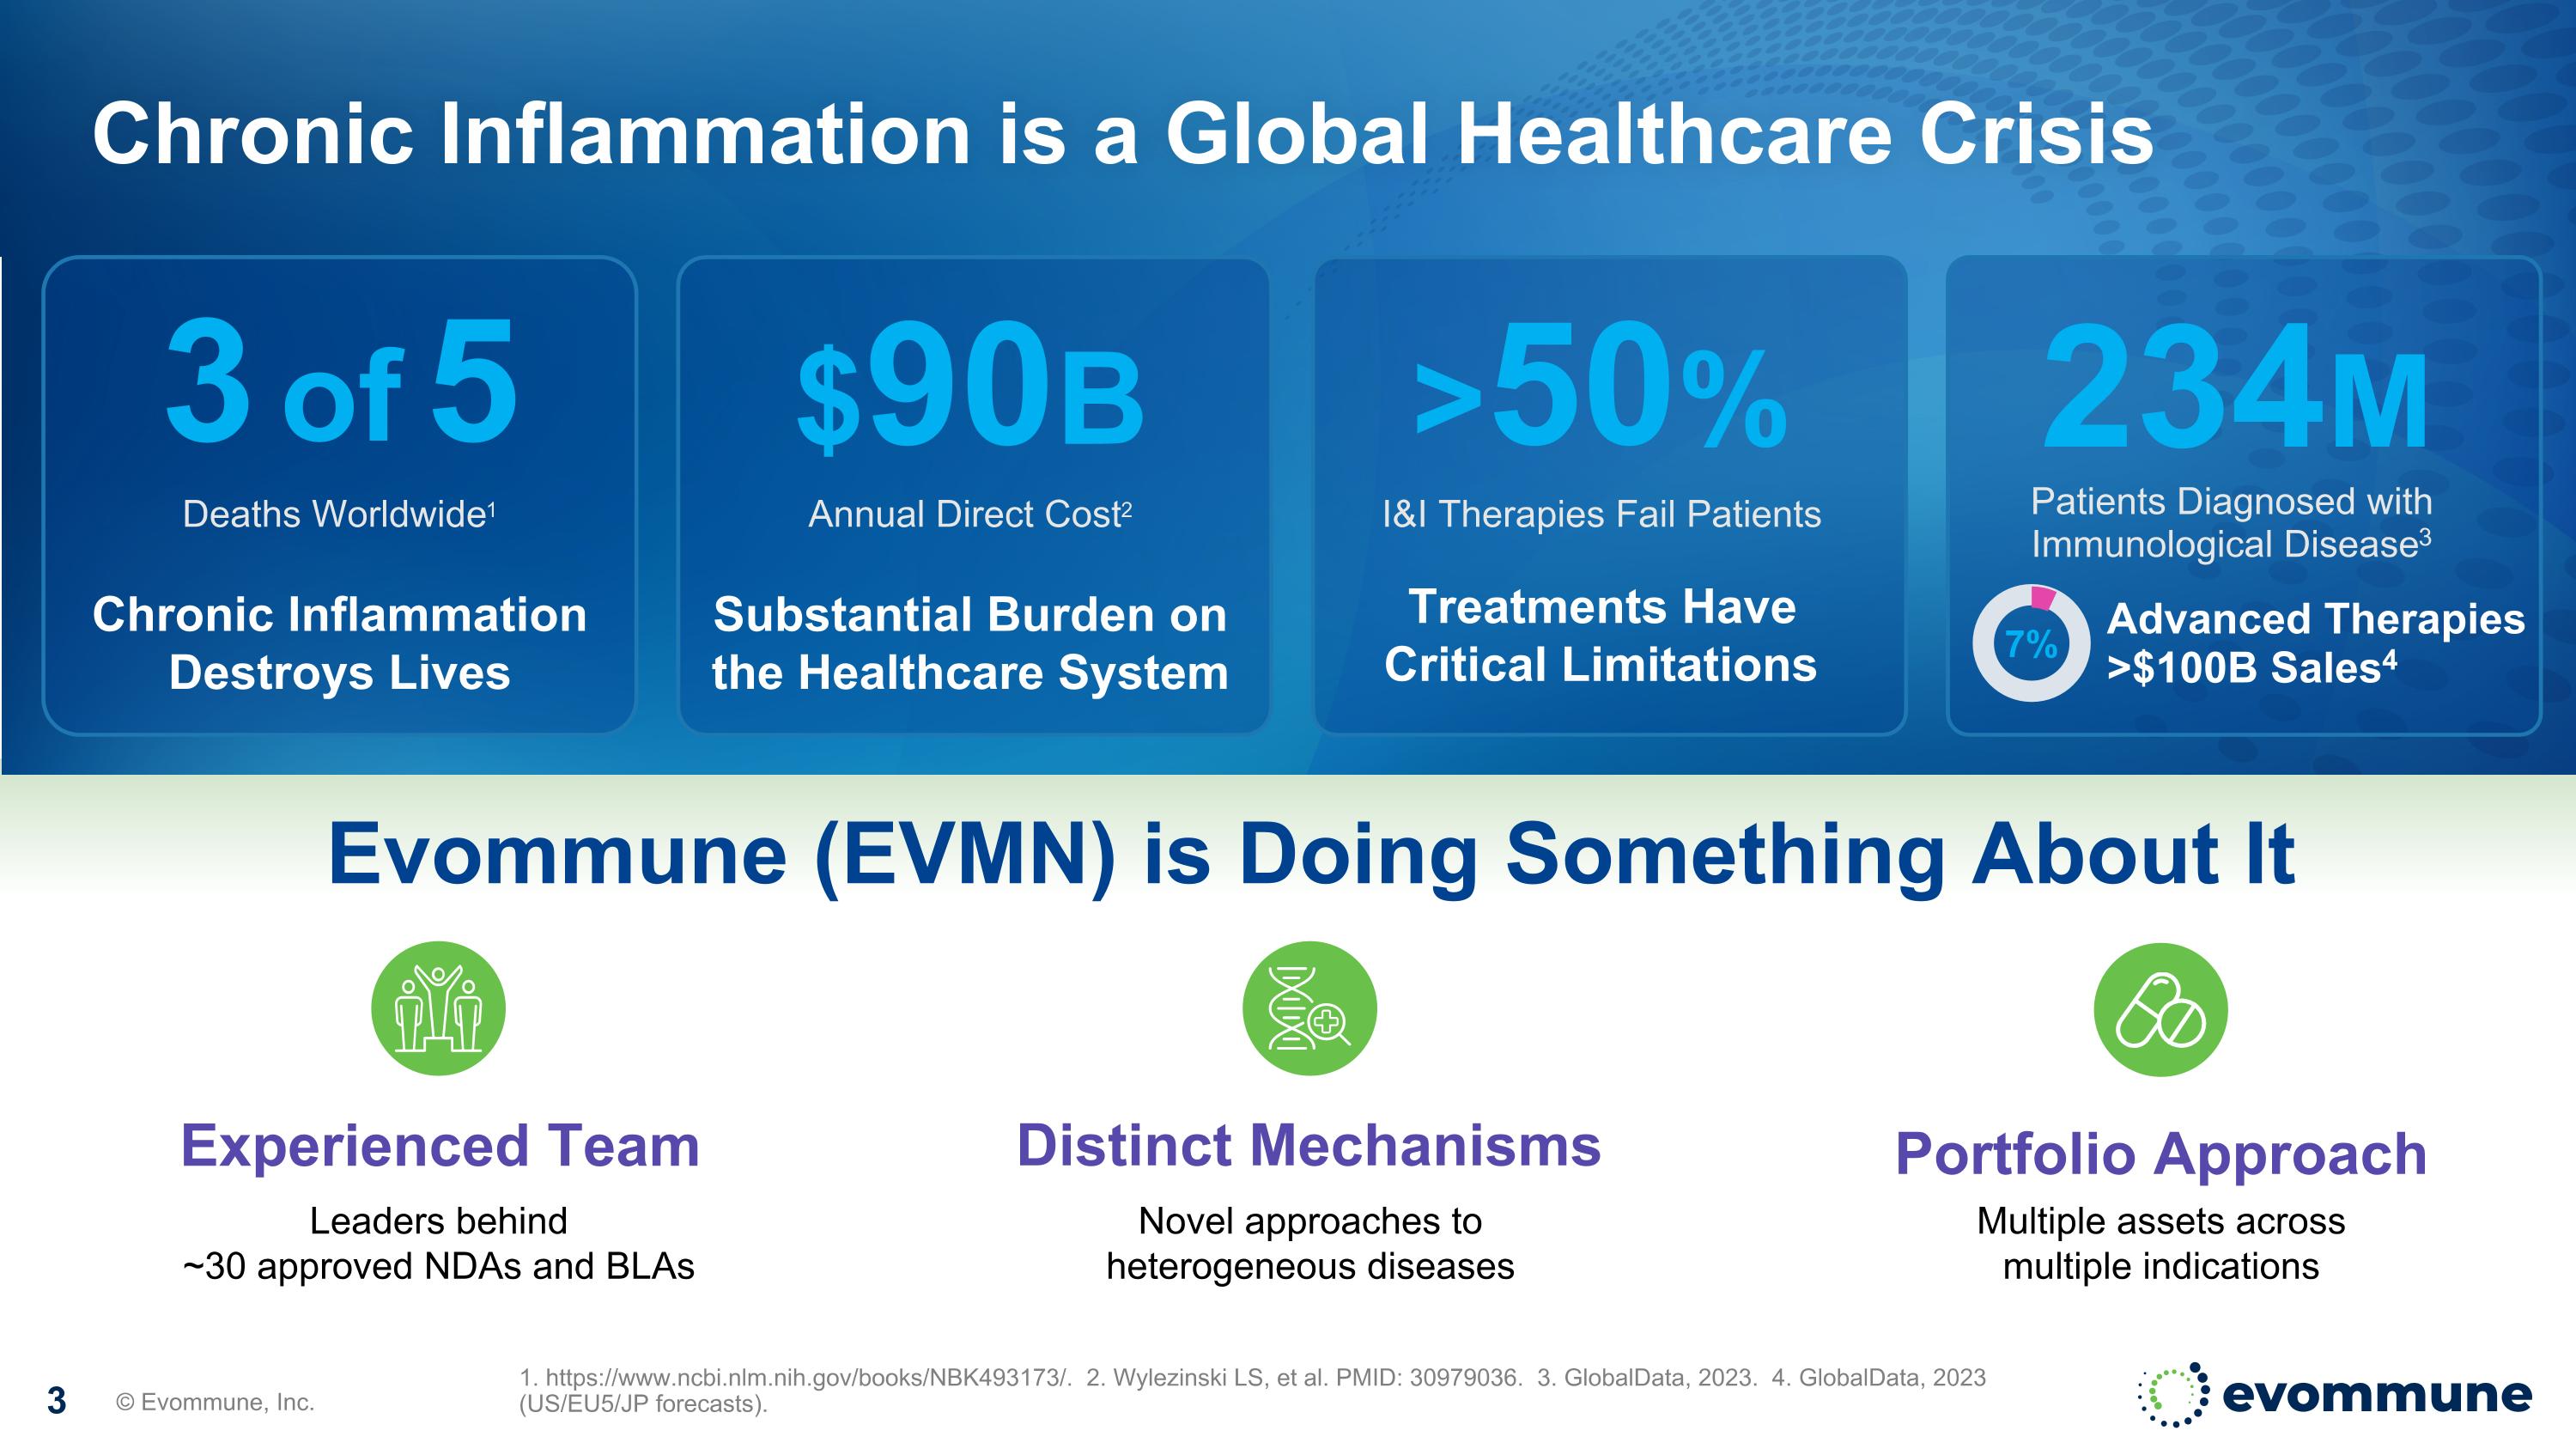
Chronic Inflammation is a Global Healthcare Crisis © Evommune, Inc. 1. https://www.ncbi.nlm.nih.gov/books/NBK493173/. 2. Wylezinski LS, et al. PMID: 30979036. 3. GlobalData, 2023. 4. GlobalData, 2023 (US/EU5/JP forecasts). Annual Direct Cost2 $90B I&I Therapies Fail Patients >50% Deaths Worldwide1 3 of 5 Experienced Team Distinct Mechanisms Portfolio Approach Substantial Burden on the Healthcare System Treatments Have Critical Limitations Chronic Inflammation Destroys Lives Leaders behind ~30 approved NDAs and BLAs Novel approaches to heterogeneous diseases Multiple assets across multiple indications Evommune (EVMN) is Doing Something About It Patients Diagnosed with Immunological Disease3 234M 7% Advanced Therapies >$100B Sales4
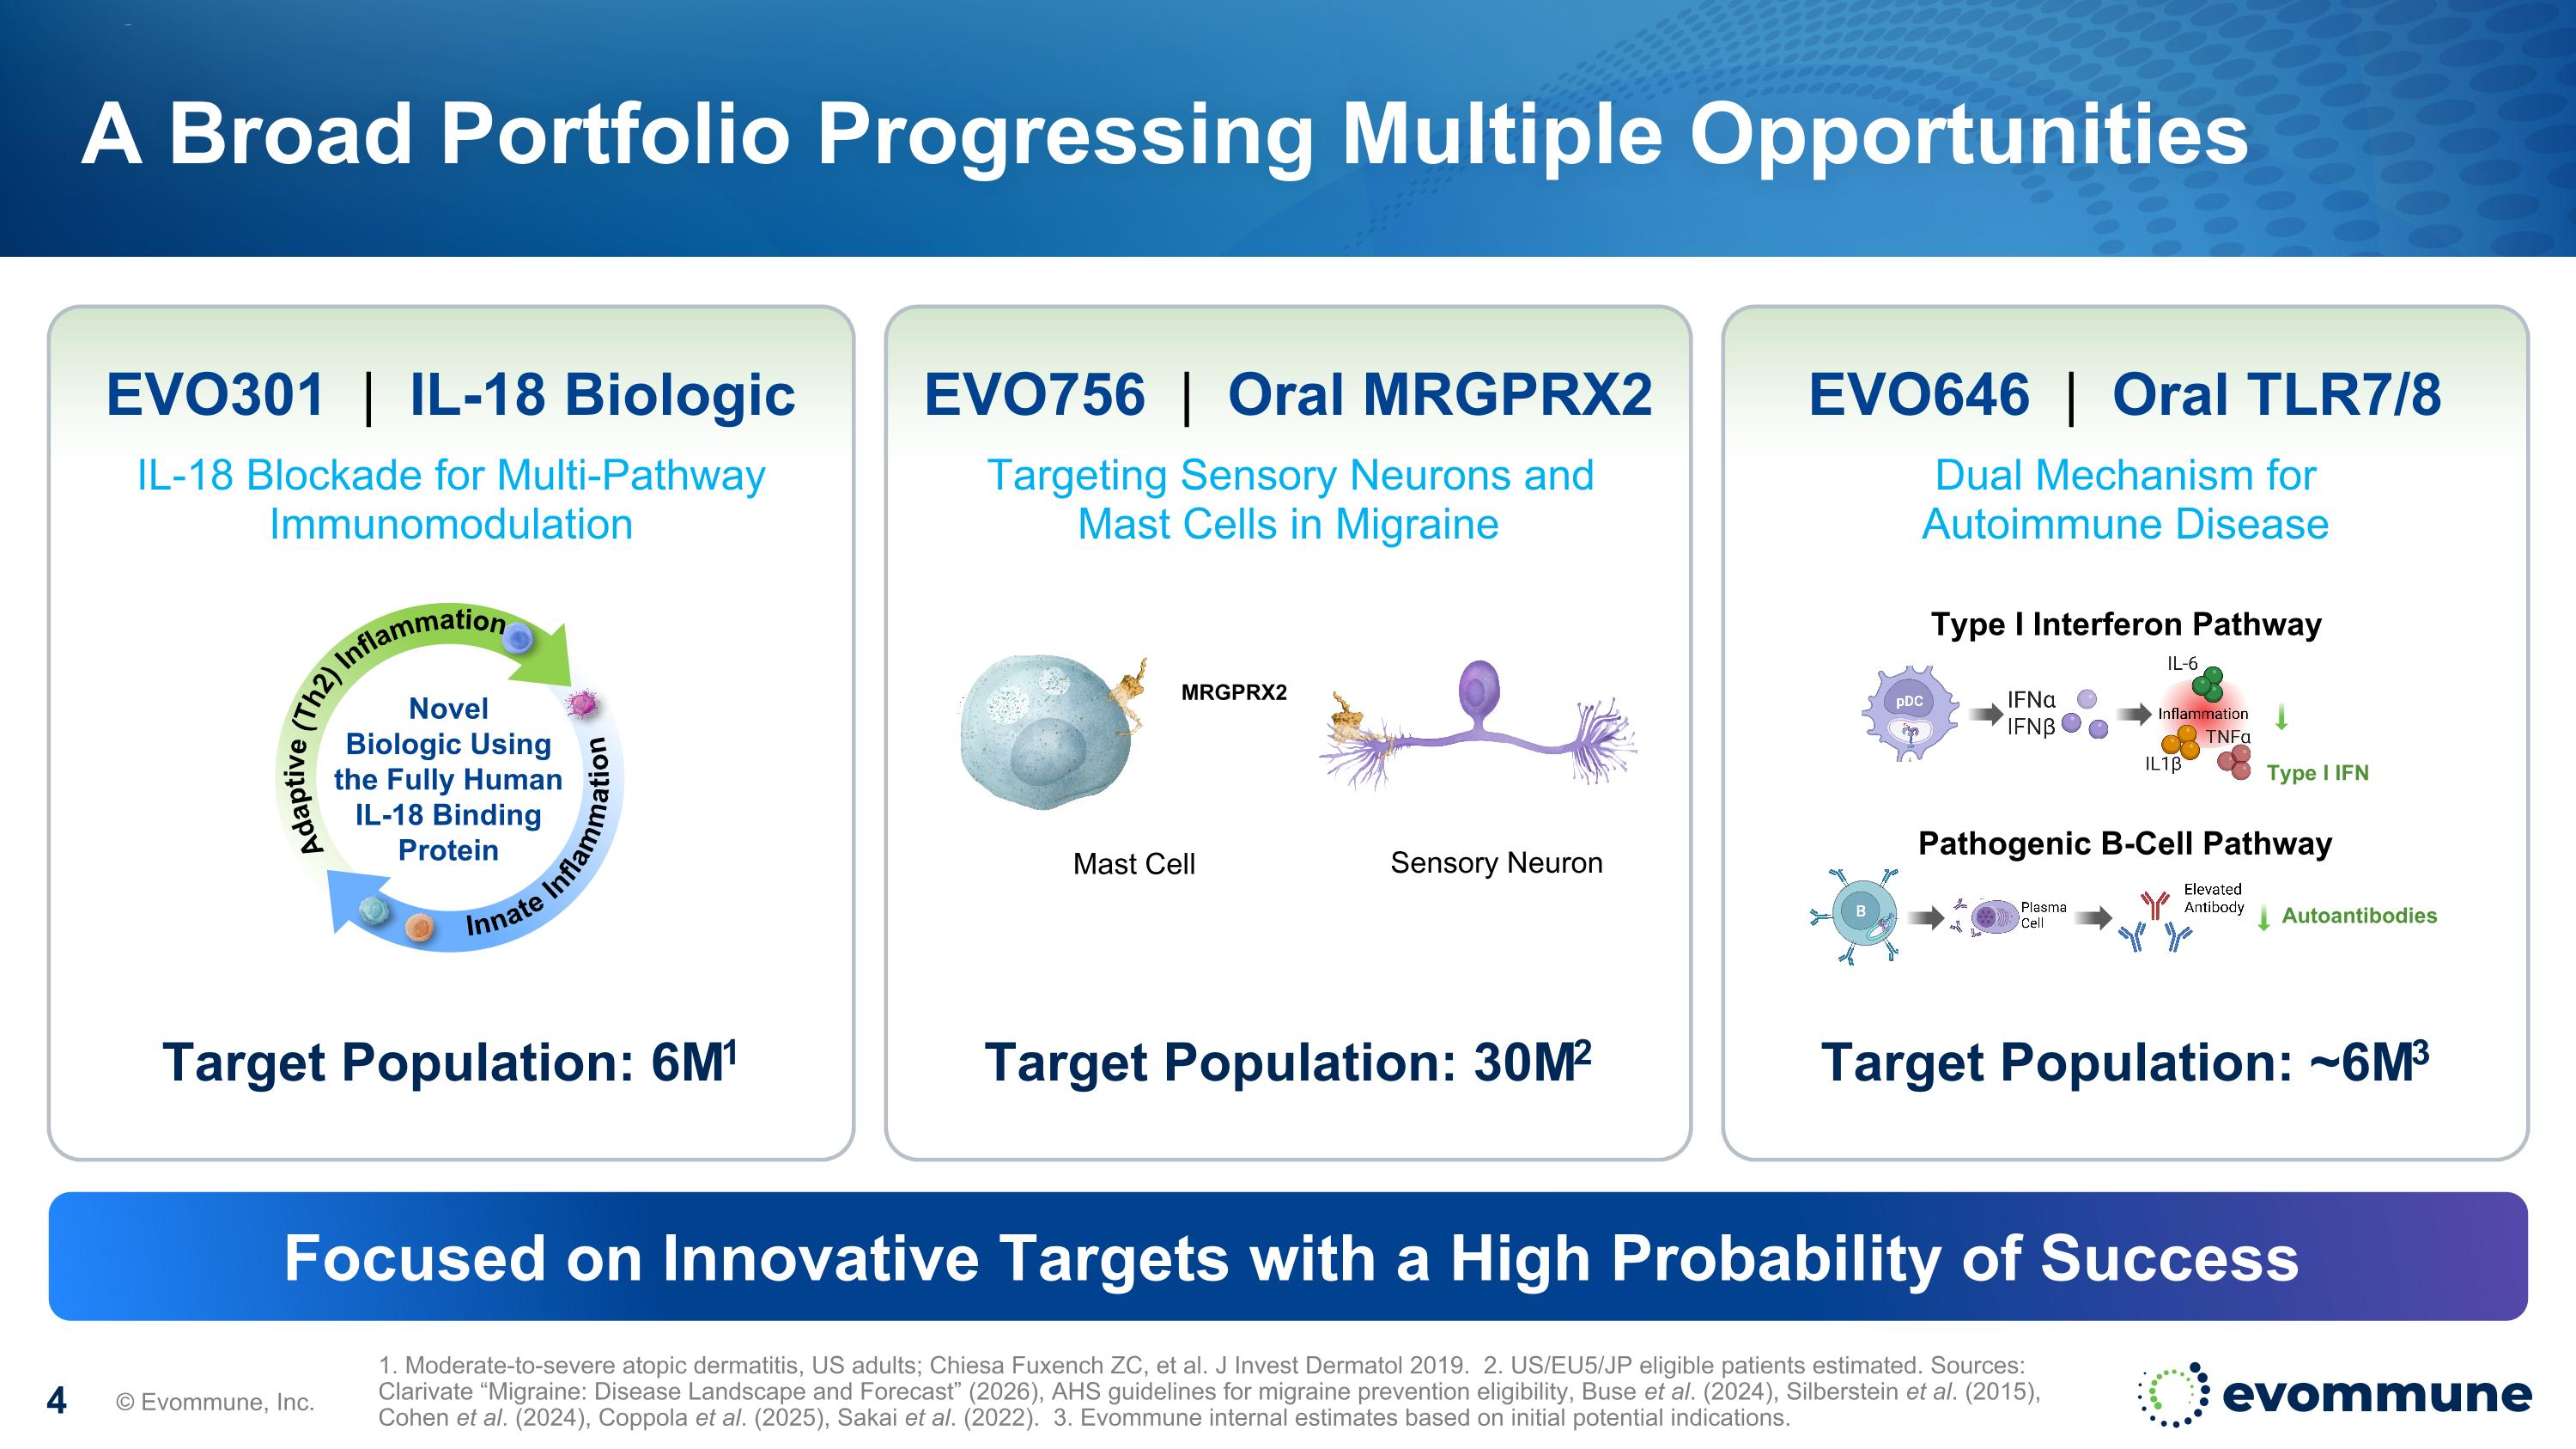
A Broad Portfolio Progressing Multiple Opportunities © Evommune, Inc. 1. Moderate-to-severe atopic dermatitis, US adults; Chiesa Fuxench ZC, et al. J Invest Dermatol 2019. 2. US/EU5/JP eligible patients estimated. Sources: Clarivate “Migraine: Disease Landscape and Forecast” (2026), AHS guidelines for migraine prevention eligibility, Buse et al. (2024), Silberstein et al. (2015), Cohen et al. (2024), Coppola et al. (2025), Sakai et al. (2022). 3. Evommune internal estimates based on initial potential indications. EVO756 | Oral MRGPRX2 EVO301 | IL-18 Biologic Focused on Innovative Targets with a High Probability of Success Targeting Sensory Neurons and Mast Cells in Migraine IL-18 Blockade for Multi-Pathway Immunomodulation Sensory Neuron Mast Cell Target Population: 30M2 Target Population: 6M1 EVO646 | Oral TLR7/8 Dual Mechanism for Autoimmune Disease Target Population: ~6M3 MRGPRX2 Novel Biologic Using the Fully Human IL-18 Binding Protein Adaptive (Th2) Inflammation Innate Inflammation Type I Interferon Pathway Pathogenic B-Cell Pathway Type I IFN Autoantibodies
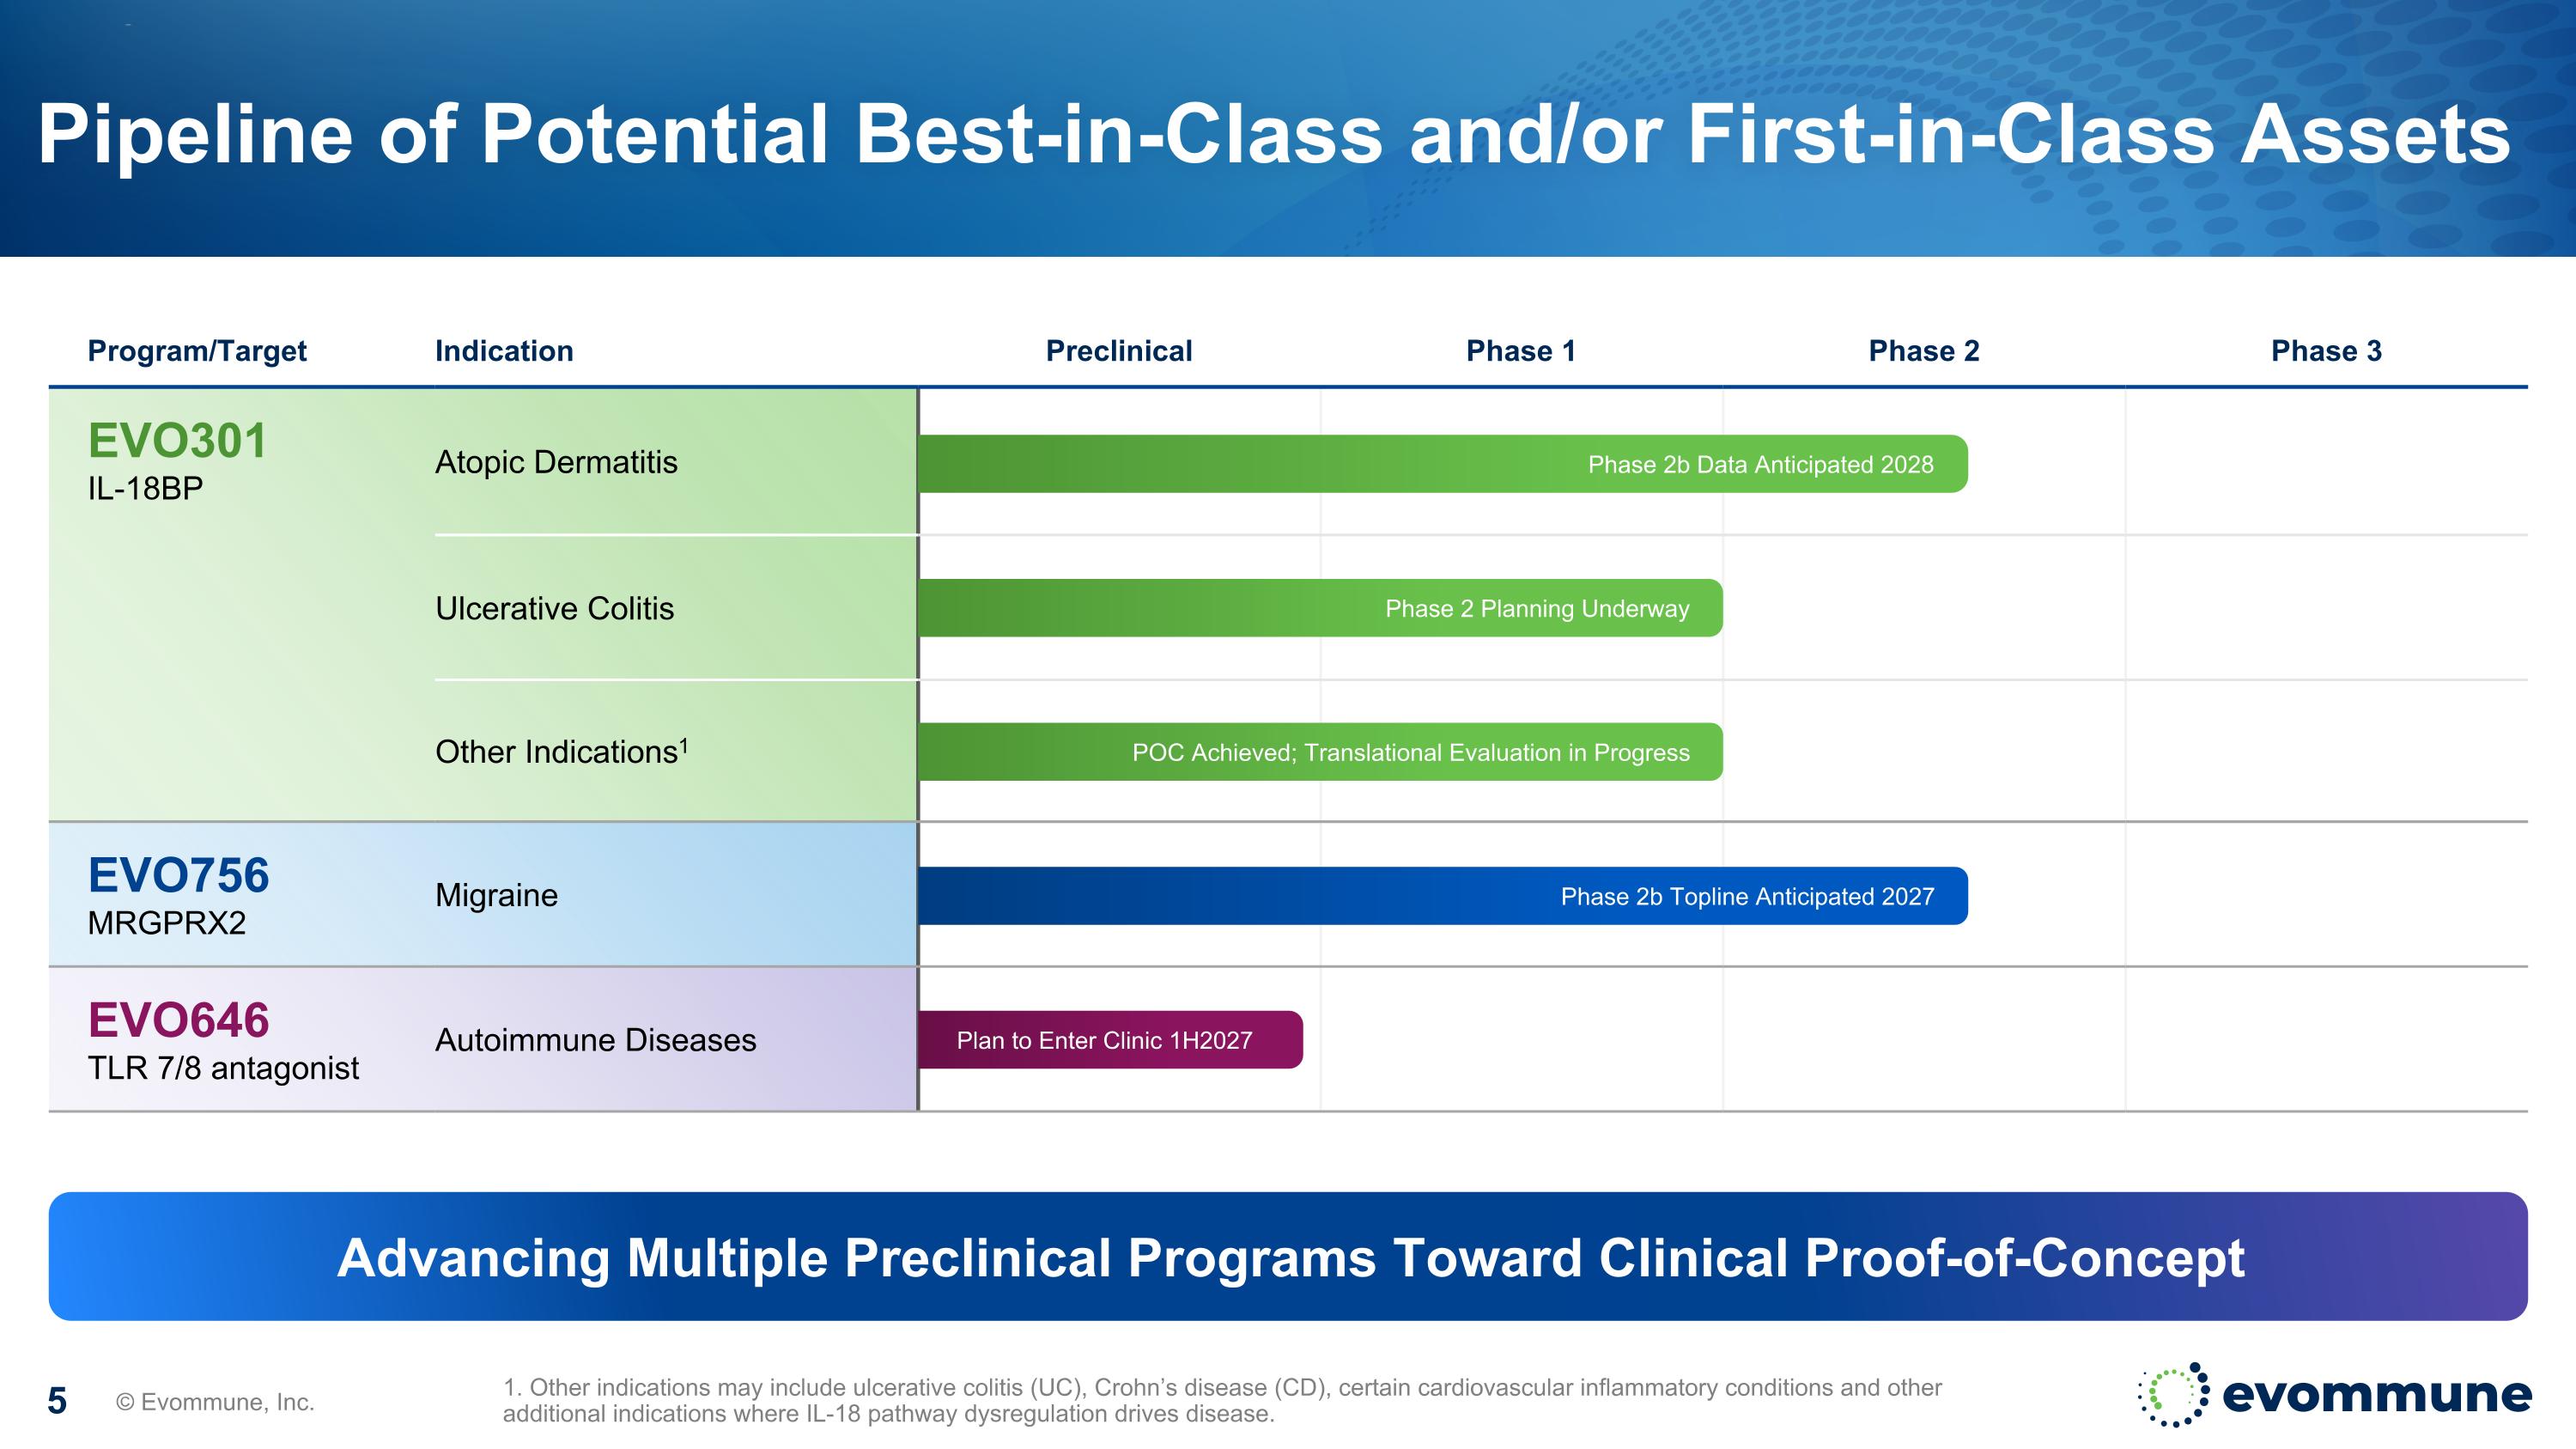
Pipeline of Potential Best-in-Class and/or First-in-Class Assets © Evommune, Inc. Program/Target Indication Preclinical Phase 1 Phase 2 Phase 3 EVO301 IL-18BP Atopic Dermatitis Ulcerative Colitis Other Indications1 EVO756 MRGPRX2 Migraine EVO646 TLR 7/8 antagonist Autoimmune Diseases Phase 2b Data Anticipated 2028 Phase 2 Planning Underway Phase 2b Topline Anticipated 2027 POC Achieved; Translational Evaluation in Progress Plan to Enter Clinic 1H2027 Advancing Multiple Preclinical Programs Toward Clinical Proof-of-Concept 1. Other indications may include ulcerative colitis (UC), Crohn’s disease (CD), certain cardiovascular inflammatory conditions and other additional indications where IL-18 pathway dysregulation drives disease.
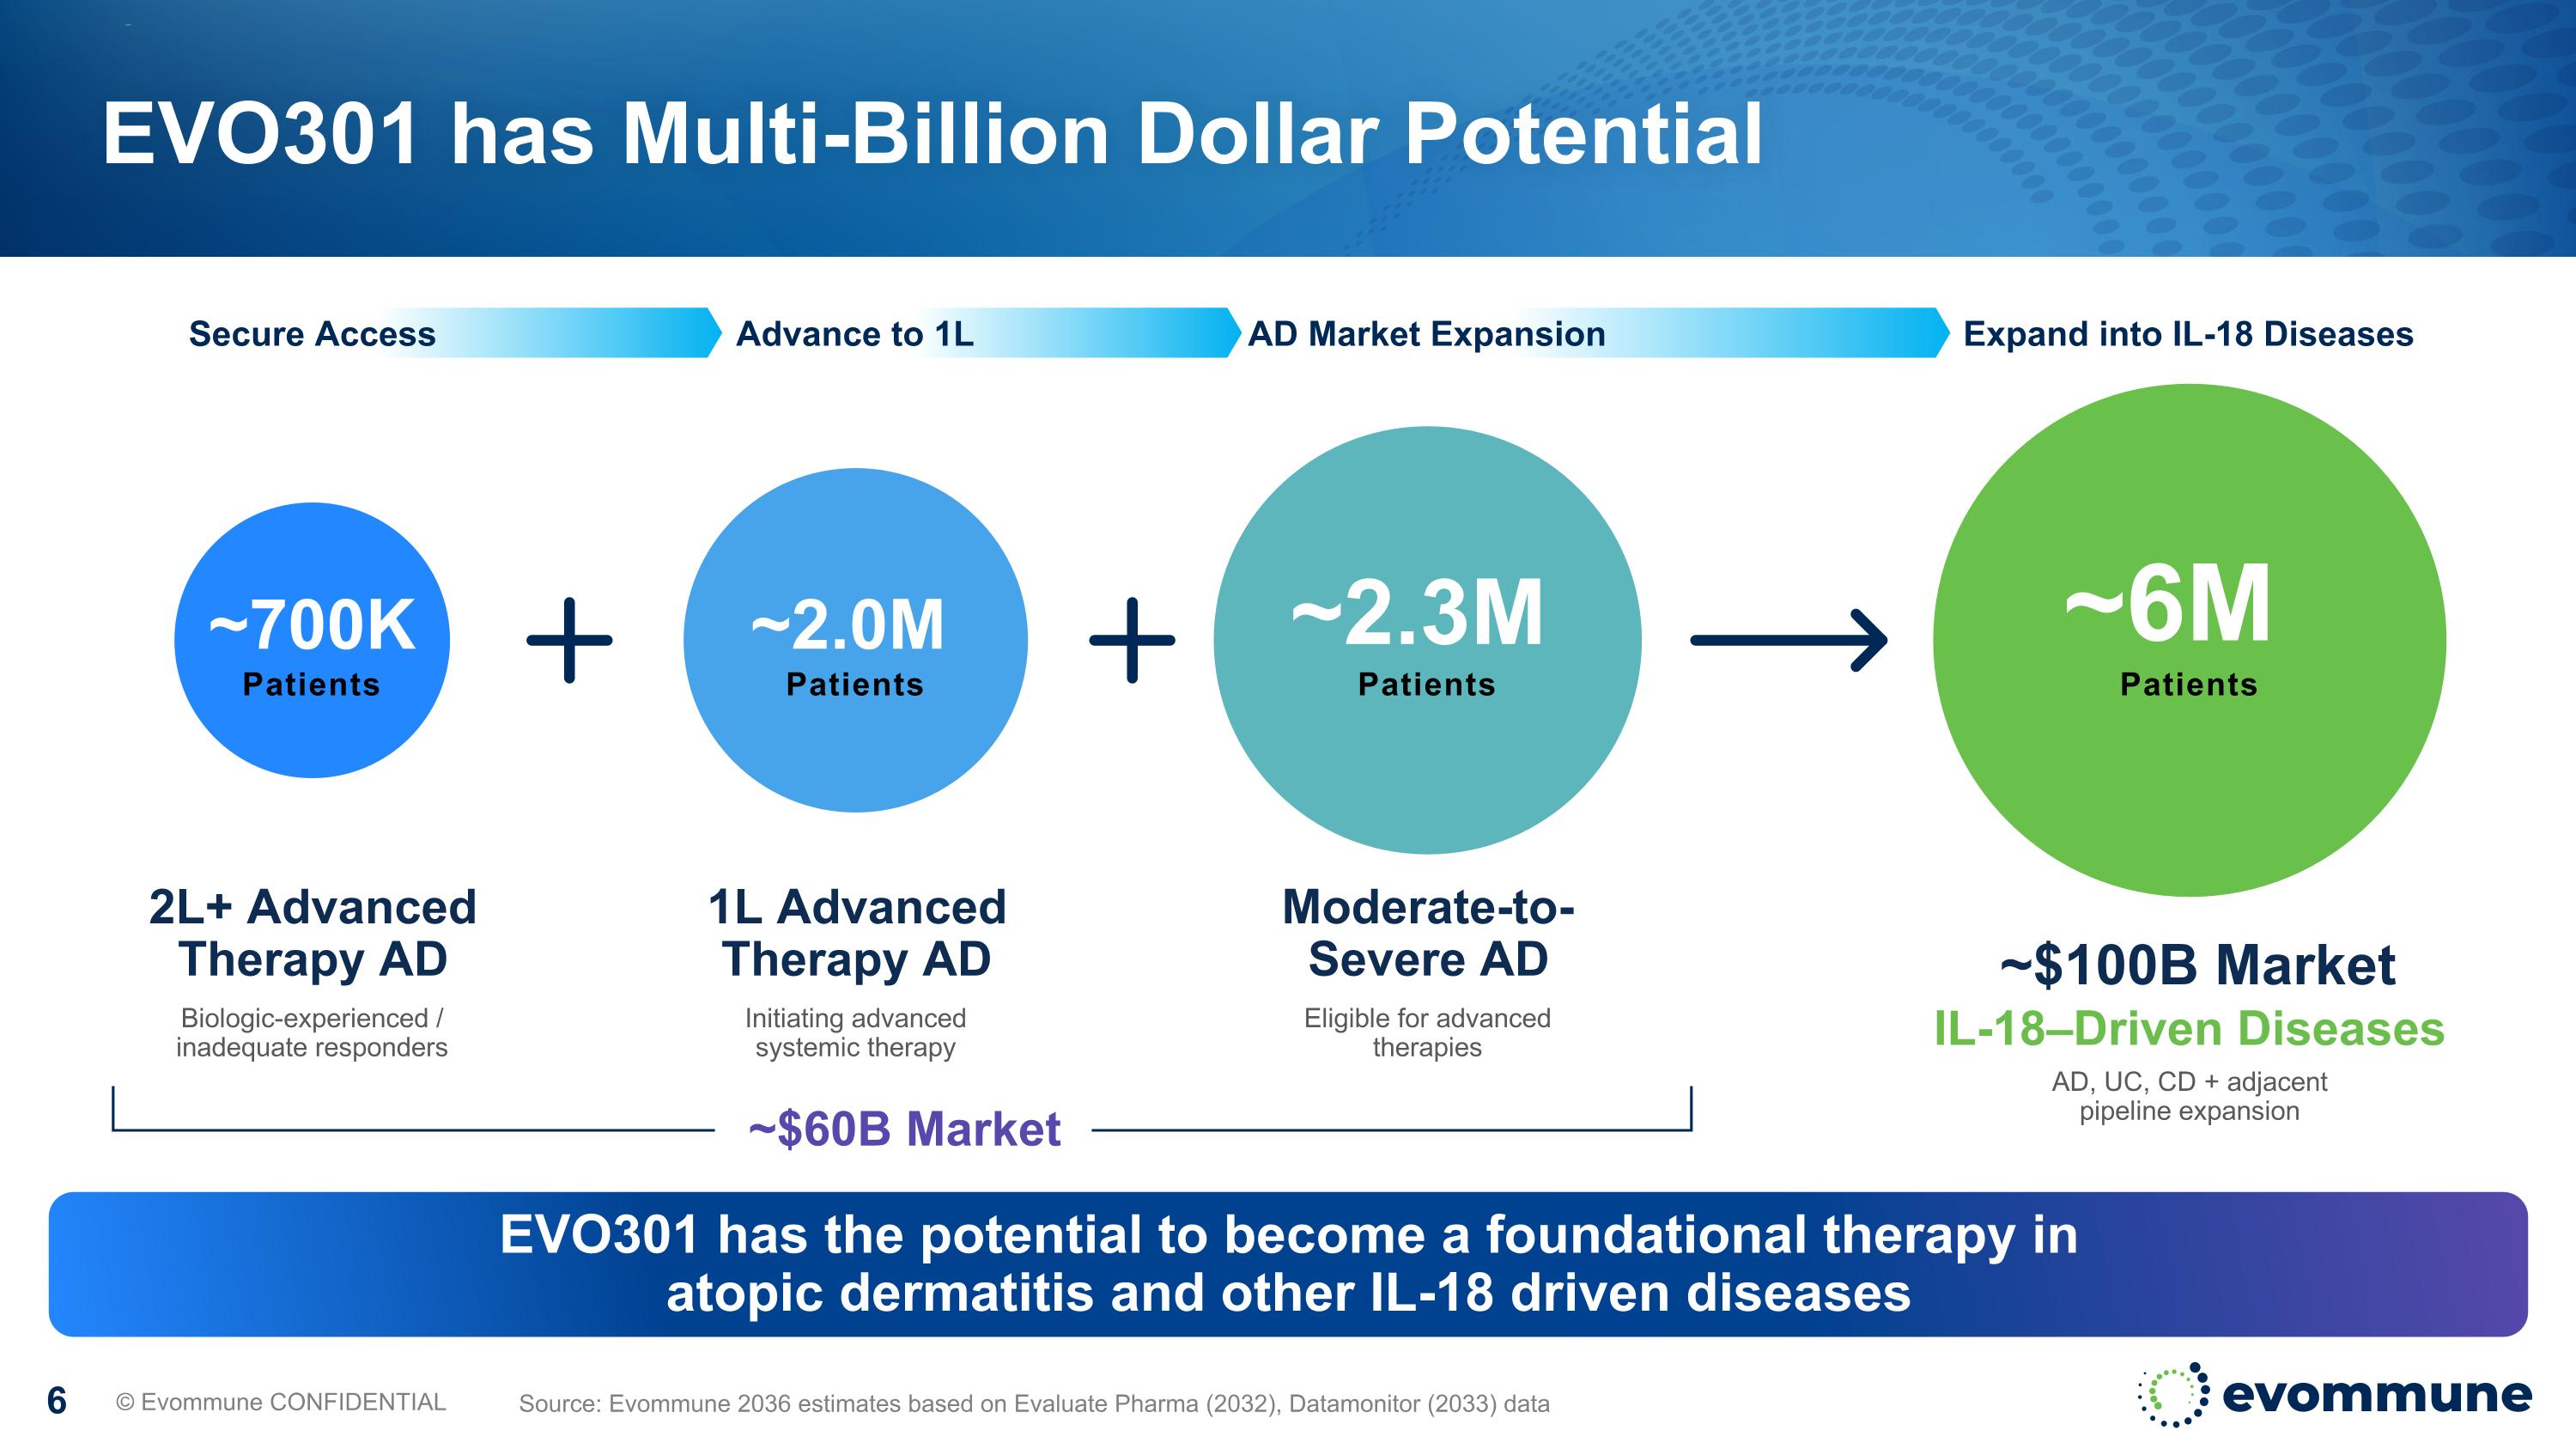
EVO301 has Multi-Billion Dollar Potential © Evommune CONFIDENTIAL Source: Evommune 2036 estimates based on Evaluate Pharma (2032), Datamonitor (2033) data ~$100B Market IL-18–Driven Diseases 2L+ Advanced Therapy AD Biologic-experienced / inadequate responders 1L Advanced Therapy AD Initiating advanced systemic therapy Expand into IL-18 Diseases Secure Access Advance to 1L AD Market Expansion Moderate-to-Severe AD Eligible for advanced therapies AD, UC, CD + adjacent pipeline expansion EVO301 has the potential to become a foundational therapy in atopic dermatitis and other IL-18 driven diseases Patients ~6M Patients ~700K Patients ~2.0M Patients ~2.3M ~$60B Market
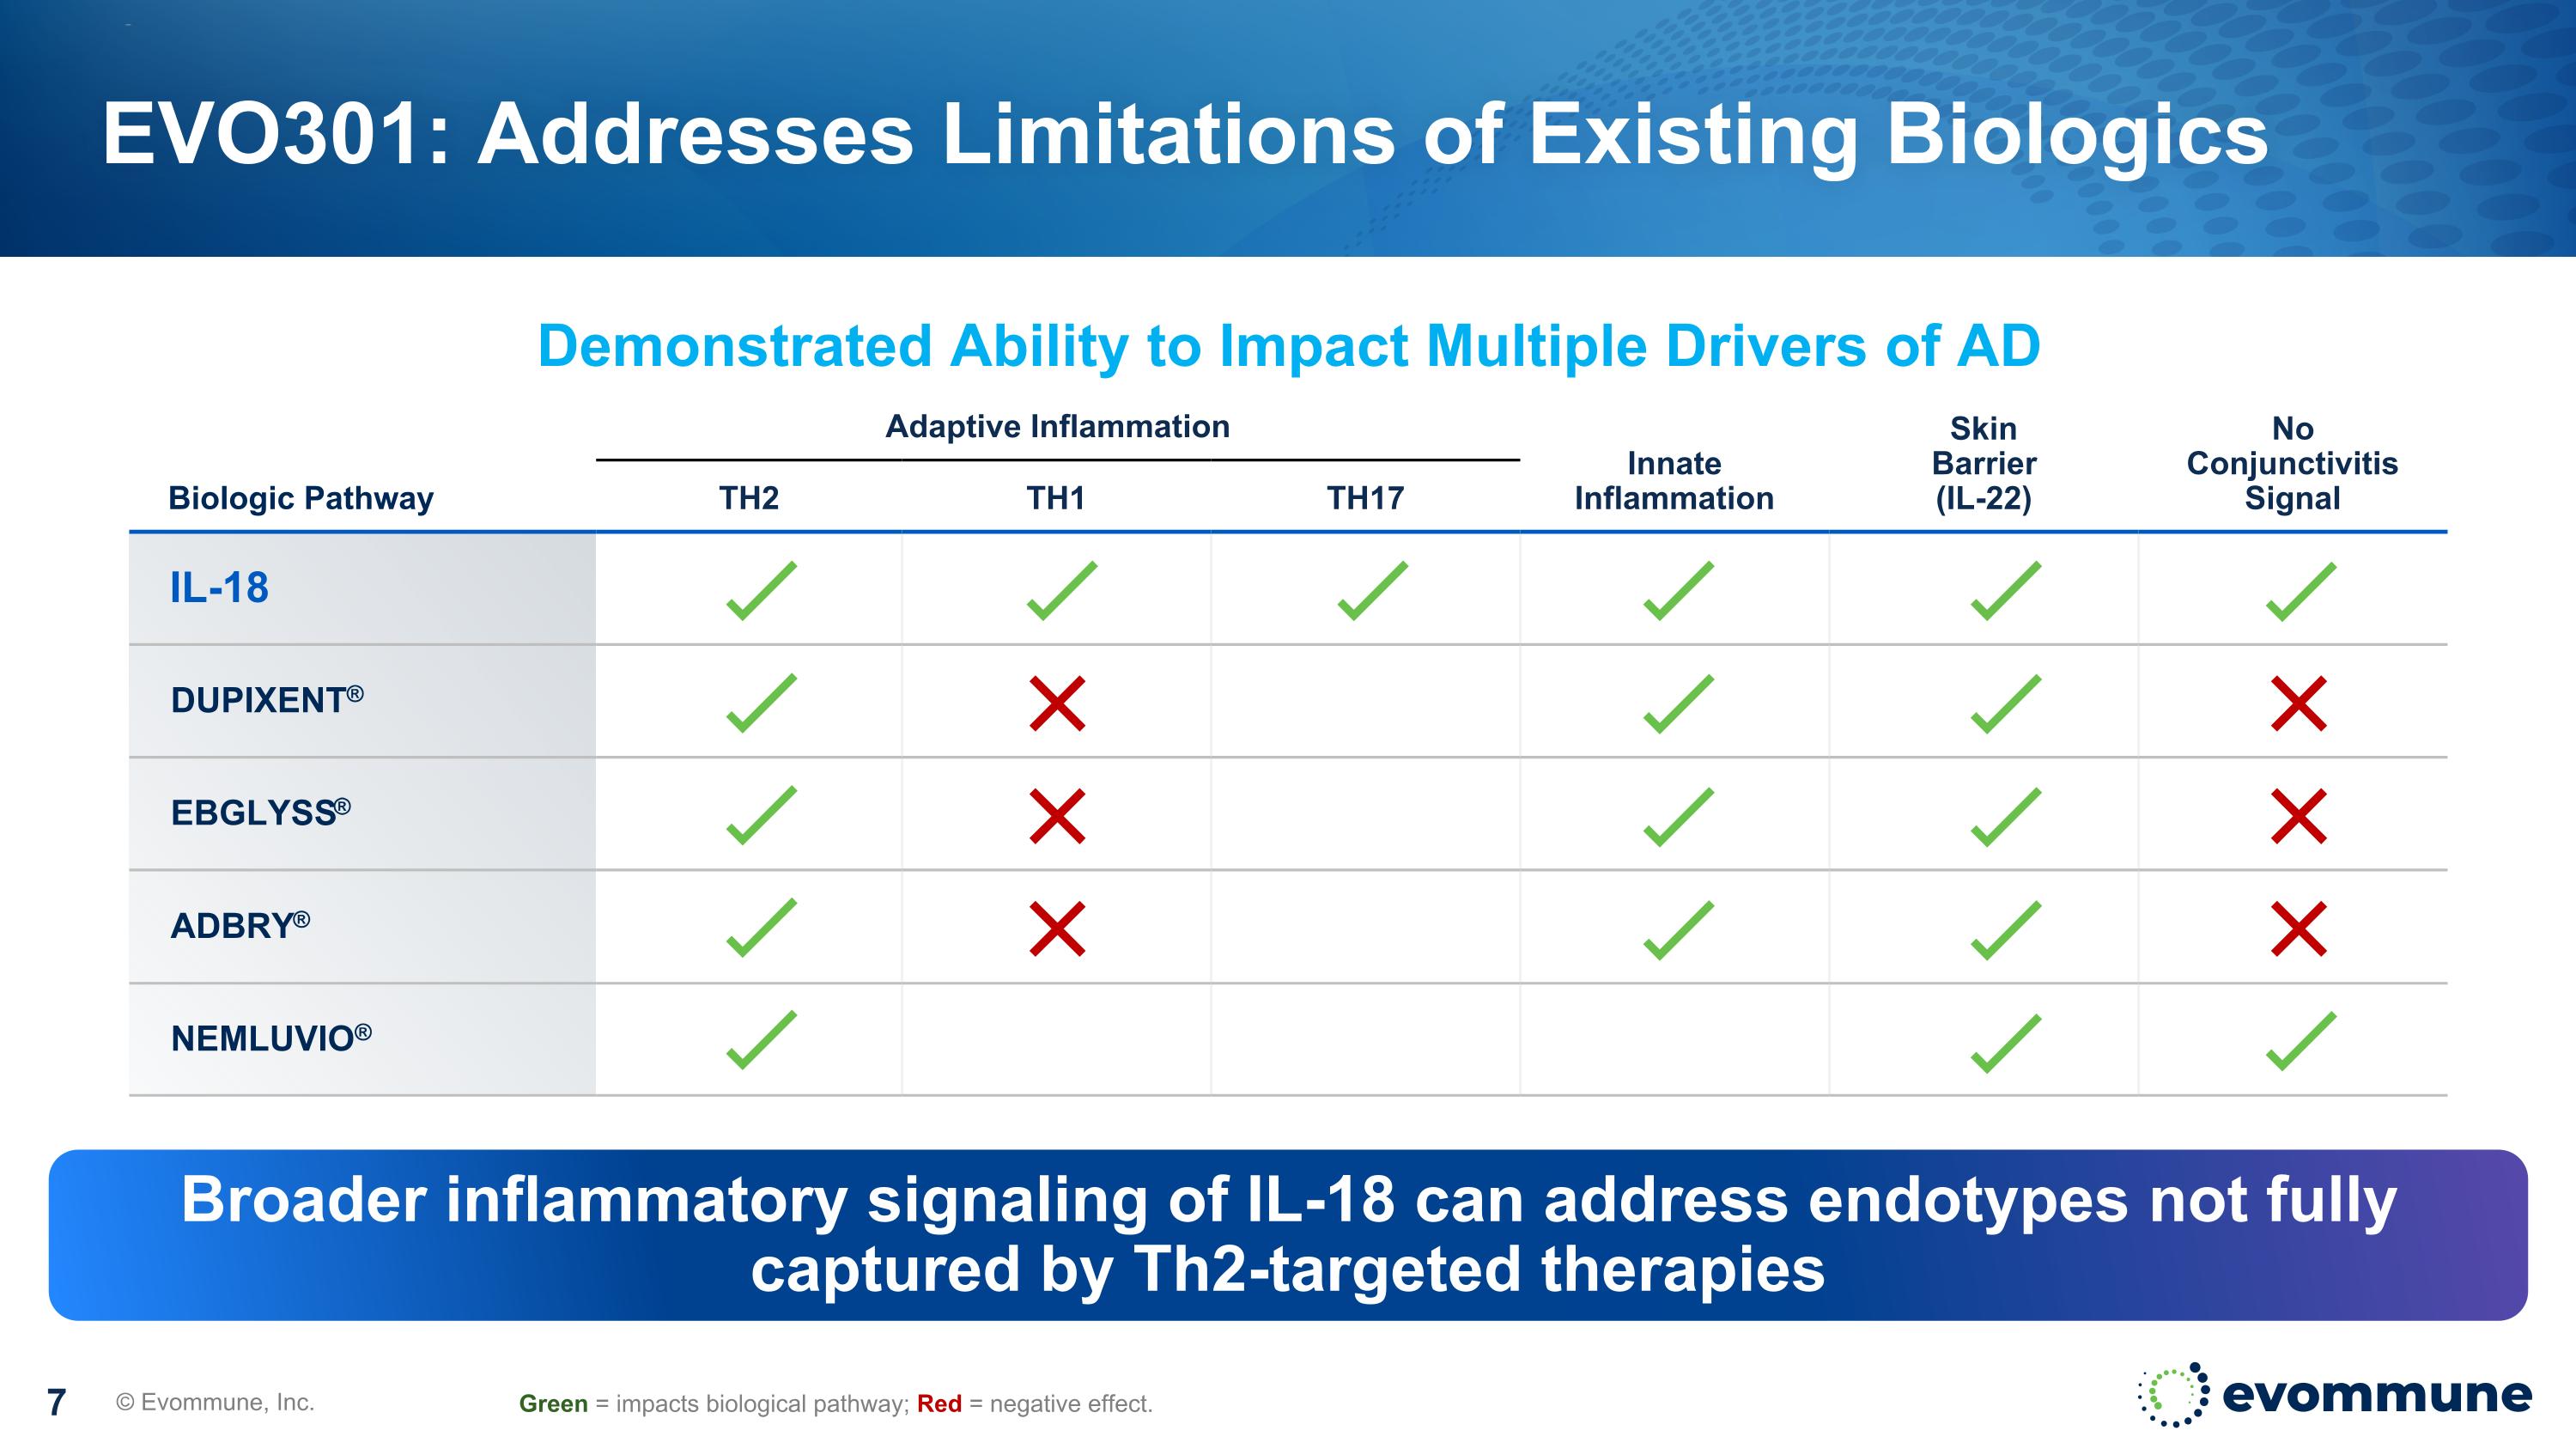
Biologic Pathway Adaptive Inflammation Innate Inflammation Skin Barrier (IL-22) No Conjunctivitis Signal TH2 TH1 TH17 IL-18 DUPIXENT® EBGLYSS® ADBRY® NEMLUVIO® EVO301: Addresses Limitations of Existing Biologics © Evommune, Inc. Green = impacts biological pathway; Red = negative effect. Demonstrated Ability to Impact Multiple Drivers of AD Broader inflammatory signaling of IL-18 can address endotypes not fully captured by Th2-targeted therapies

Key Milestones Ahead For Evommune (NYSE: EVMN) © Evommune, Inc. ~$287M Cash and Investments; Expected Runway Into 2029 Championing Innovation for Chronic Inflammation EVO301 IL-18BP Plan to initiate Phase 2b in AD with subcutaneous formulation in mid-2027 EVO756 MRGPRX2 Expect top-line data from Phase 2b migraine trial in 2027 EVO646 TLR7/8 Plan to initiate Phase 1 in 1H 2027 Research Anticipate new programs entering the clinic with a steady cadence

EVO301: Potential Best-in-Class IL-18BP Fusion Protein Long-Acting Serum Albumin-Binding Injectable Therapeutic Fusion Protein Designed to Neutralize IL-18 Signaling © Evommune, Inc.
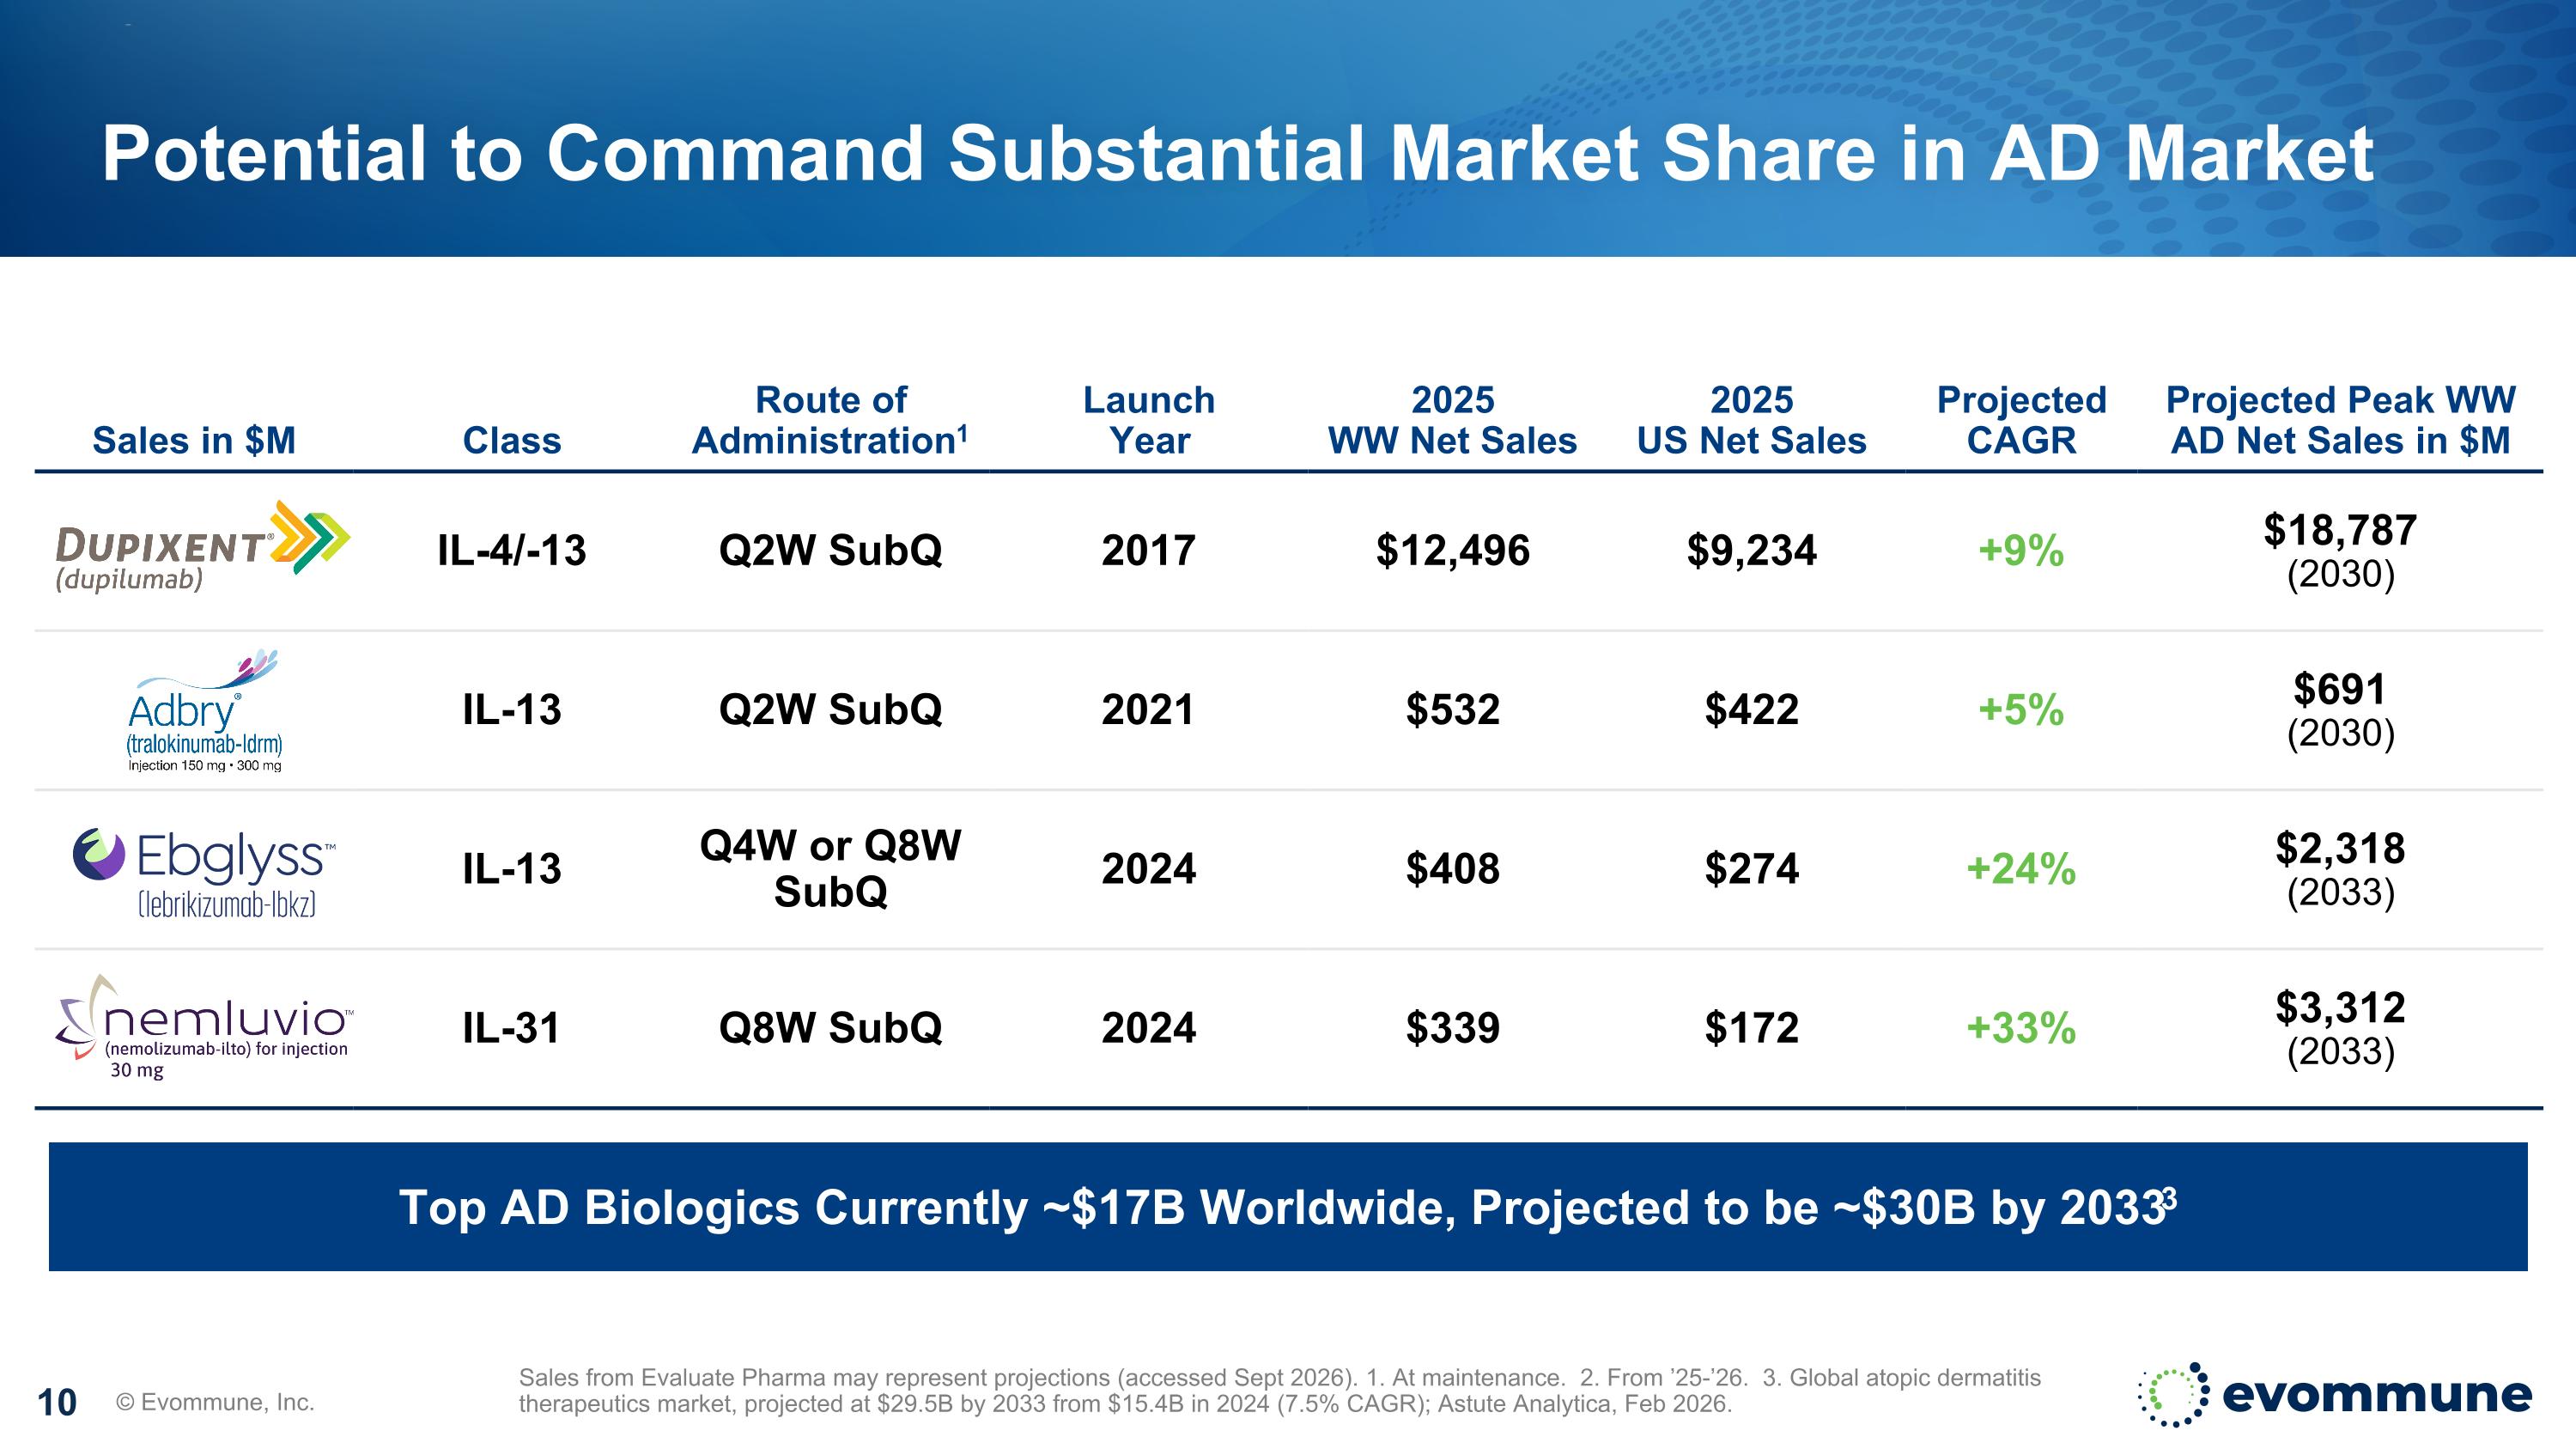
Potential to Command Substantial Market Share in AD Market © Evommune, Inc. Sales from Evaluate Pharma may represent projections (accessed Sept 2026). 1. At maintenance. 2. From ’25-’26. 3. Global atopic dermatitis therapeutics market, projected at $29.5B by 2033 from $15.4B in 2024 (7.5% CAGR); Astute Analytica, Feb 2026. Sales in $M Class Route of Administration1 Launch Year 2025 WW Net Sales 2025 US Net Sales Projected CAGR Projected Peak WW AD Net Sales in $M IL-4/-13 Q2W SubQ 2017 $12,496 $9,234 +9% $18,787 (2030) IL-13 Q2W SubQ 2021 $532 $422 +5% $691 (2030) IL-13 Q4W or Q8W SubQ 2024 $408 $274 +24% $2,318 (2033) IL-31 Q8W SubQ 2024 $339 $172 +33% $3,312 (2033) Top AD Biologics Currently ~$17B Worldwide, Projected to be ~$30B by 20333
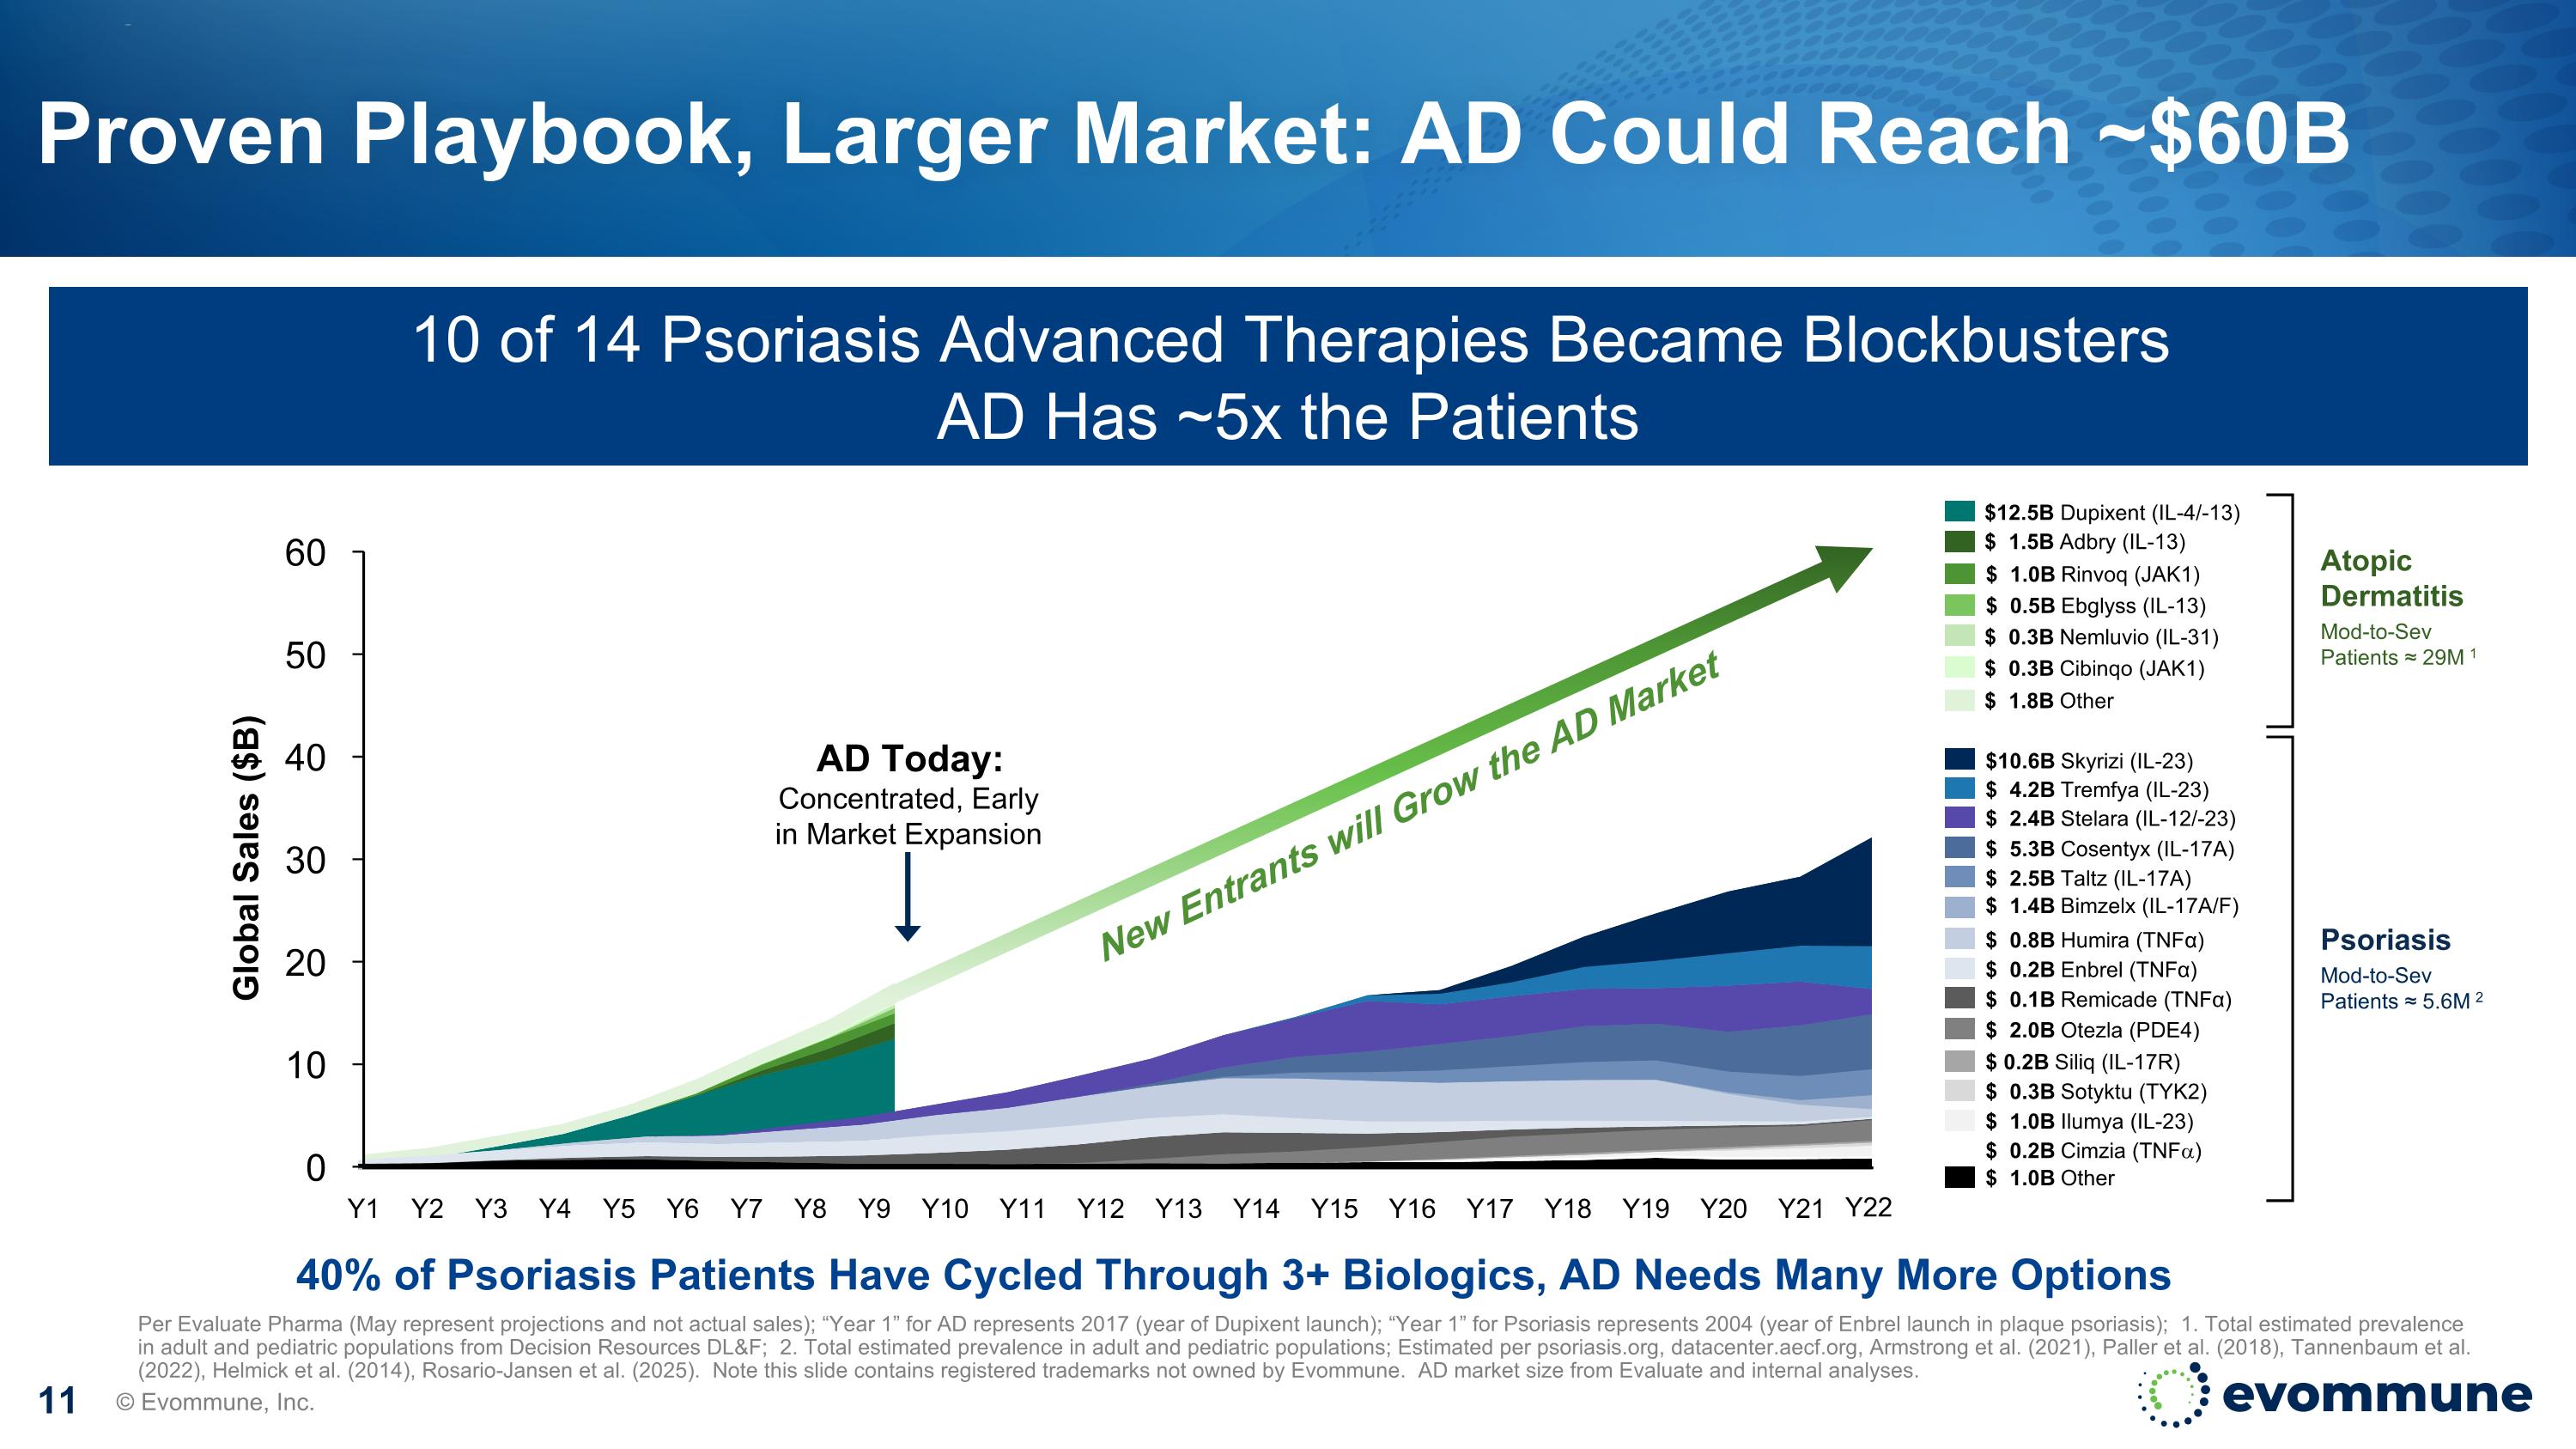
10 20 30 0 50 60 40 Proven Playbook, Larger Market: AD Could Reach ~$60B © Evommune, Inc. Per Evaluate Pharma (May represent projections and not actual sales); “Year 1” for AD represents 2017 (year of Dupixent launch); “Year 1” for Psoriasis represents 2004 (year of Enbrel launch in plaque psoriasis); 1. Total estimated prevalence in adult and pediatric populations from Decision Resources DL&F; 2. Total estimated prevalence in adult and pediatric populations; Estimated per psoriasis.org, datacenter.aecf.org, Armstrong et al. (2021), Paller et al. (2018), Tannenbaum et al. (2022), Helmick et al. (2014), Rosario-Jansen et al. (2025). Note this slide contains registered trademarks not owned by Evommune. AD market size from Evaluate and internal analyses. Atopic Dermatitis Mod-to-Sev Patients ≈ 29M 1 AD Today: Concentrated, Early in Market Expansion Psoriasis Mod-to-Sev Patients ≈ 5.6M 2 $12.5B Dupixent (IL-4/-13) $ 1.5B Adbry (IL-13) $ 1.0B Rinvoq (JAK1) $ 0.5B Ebglyss (IL-13) $ 1.8B Other $10.6B Skyrizi (IL-23) $ 4.2B Tremfya (IL-23) $ 2.4B Stelara (IL-12/-23) $ 5.3B Cosentyx (IL-17A) $ 2.5B Taltz (IL-17A) $ 1.4B Bimzelx (IL-17A/F) $ 0.8B Humira (TNFα) $ 0.2B Enbrel (TNFα) $ 0.1B Remicade (TNFα) $ 2.0B Otezla (PDE4) $ 0.2B Cimzia (TNFa) $ 0.3B Nemluvio (IL-31) $ 0.3B Cibinqo (JAK1) $ 1.0B Ilumya (IL-23) $ 0.3B Sotyktu (TYK2) $ 0.2B Siliq (IL-17R) $ 1.0B Other New Entrants will Grow the AD Market Global Sales ($B) Y1 Y2 Y3 Y4 Y5 Y6 Y7 Y8 Y9 Y10 Y11 Y12 Y13 Y14 Y15 Y16 Y17 Y18 Y19 Y20 Y21 Y22 40% of Psoriasis Patients Have Cycled Through 3+ Biologics, AD Needs Many More Options 10 of 14 Psoriasis Advanced Therapies Became Blockbusters AD Has ~5x the Patients
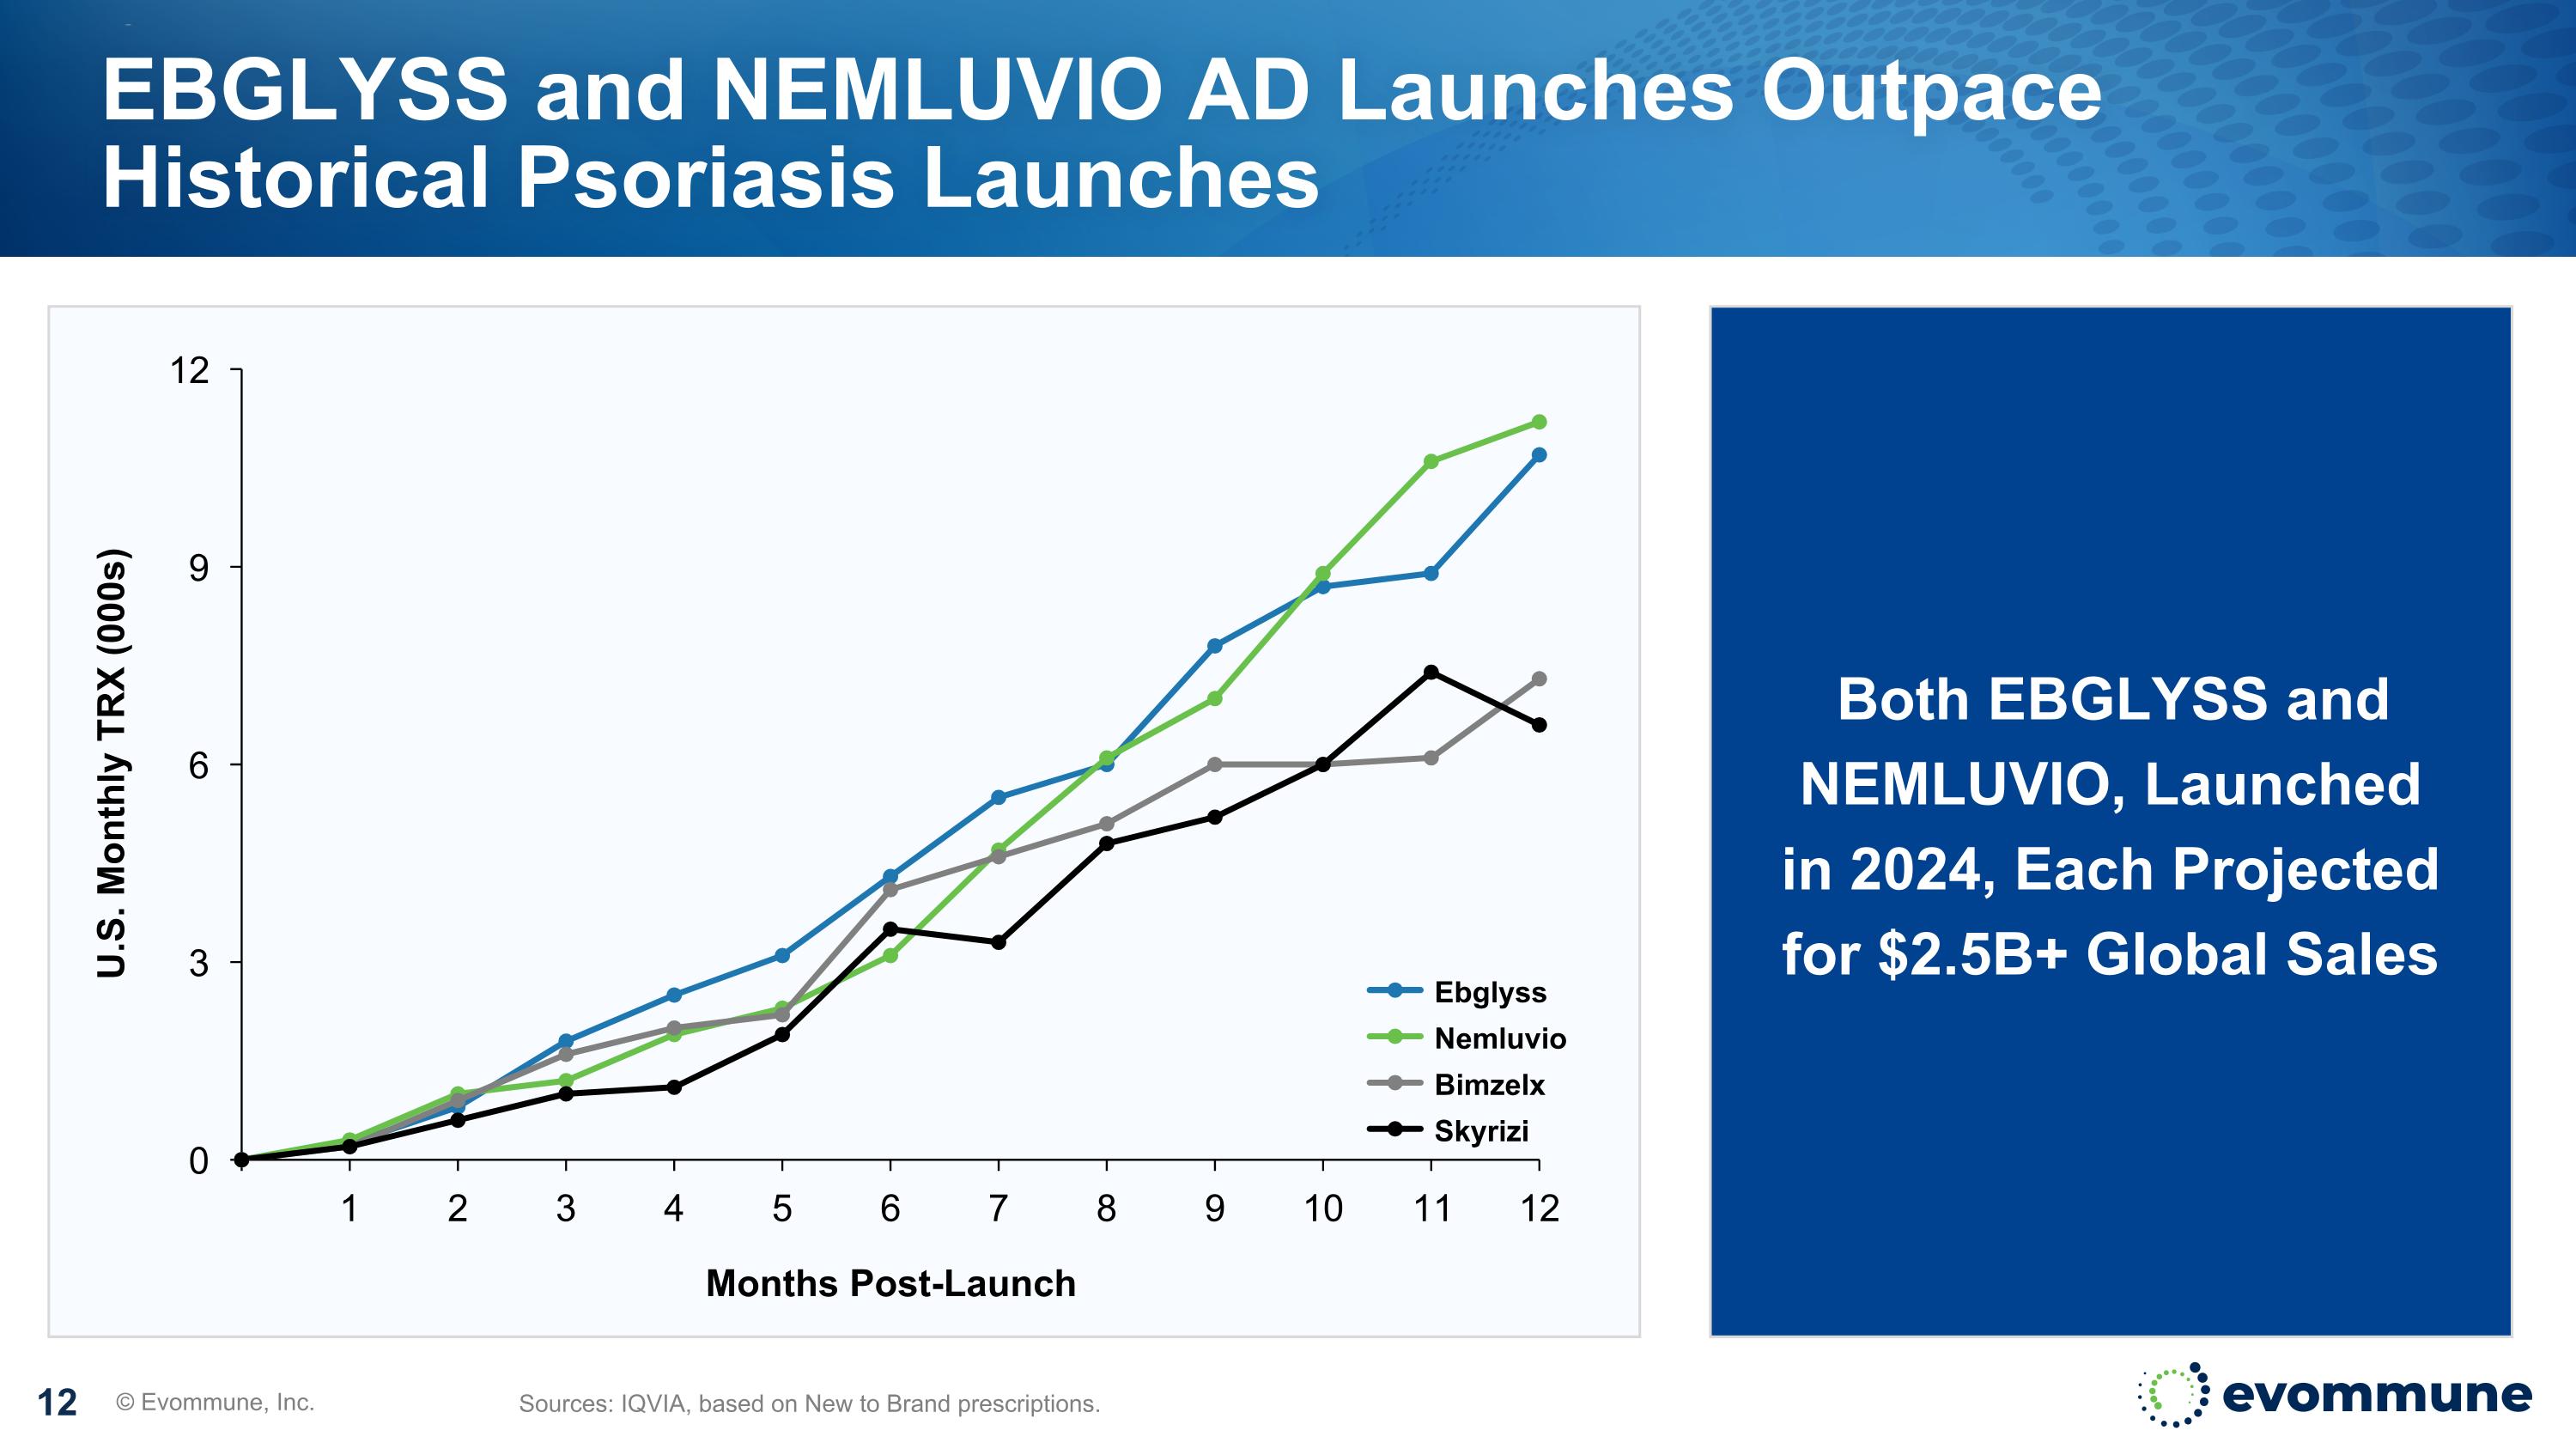
Both EBGLYSS and NEMLUVIO, Launched in 2024, Each Projected for $2.5B+ Global Sales EBGLYSS and NEMLUVIO AD Launches Outpace Historical Psoriasis Launches © Evommune, Inc. Sources: IQVIA, based on New to Brand prescriptions. 1 2 3 4 5 6 7 8 9 10 11 12 Months Post-Launch U.S. Monthly TRX (000s) Ebglyss Nemluvio Bimzelx Skyrizi
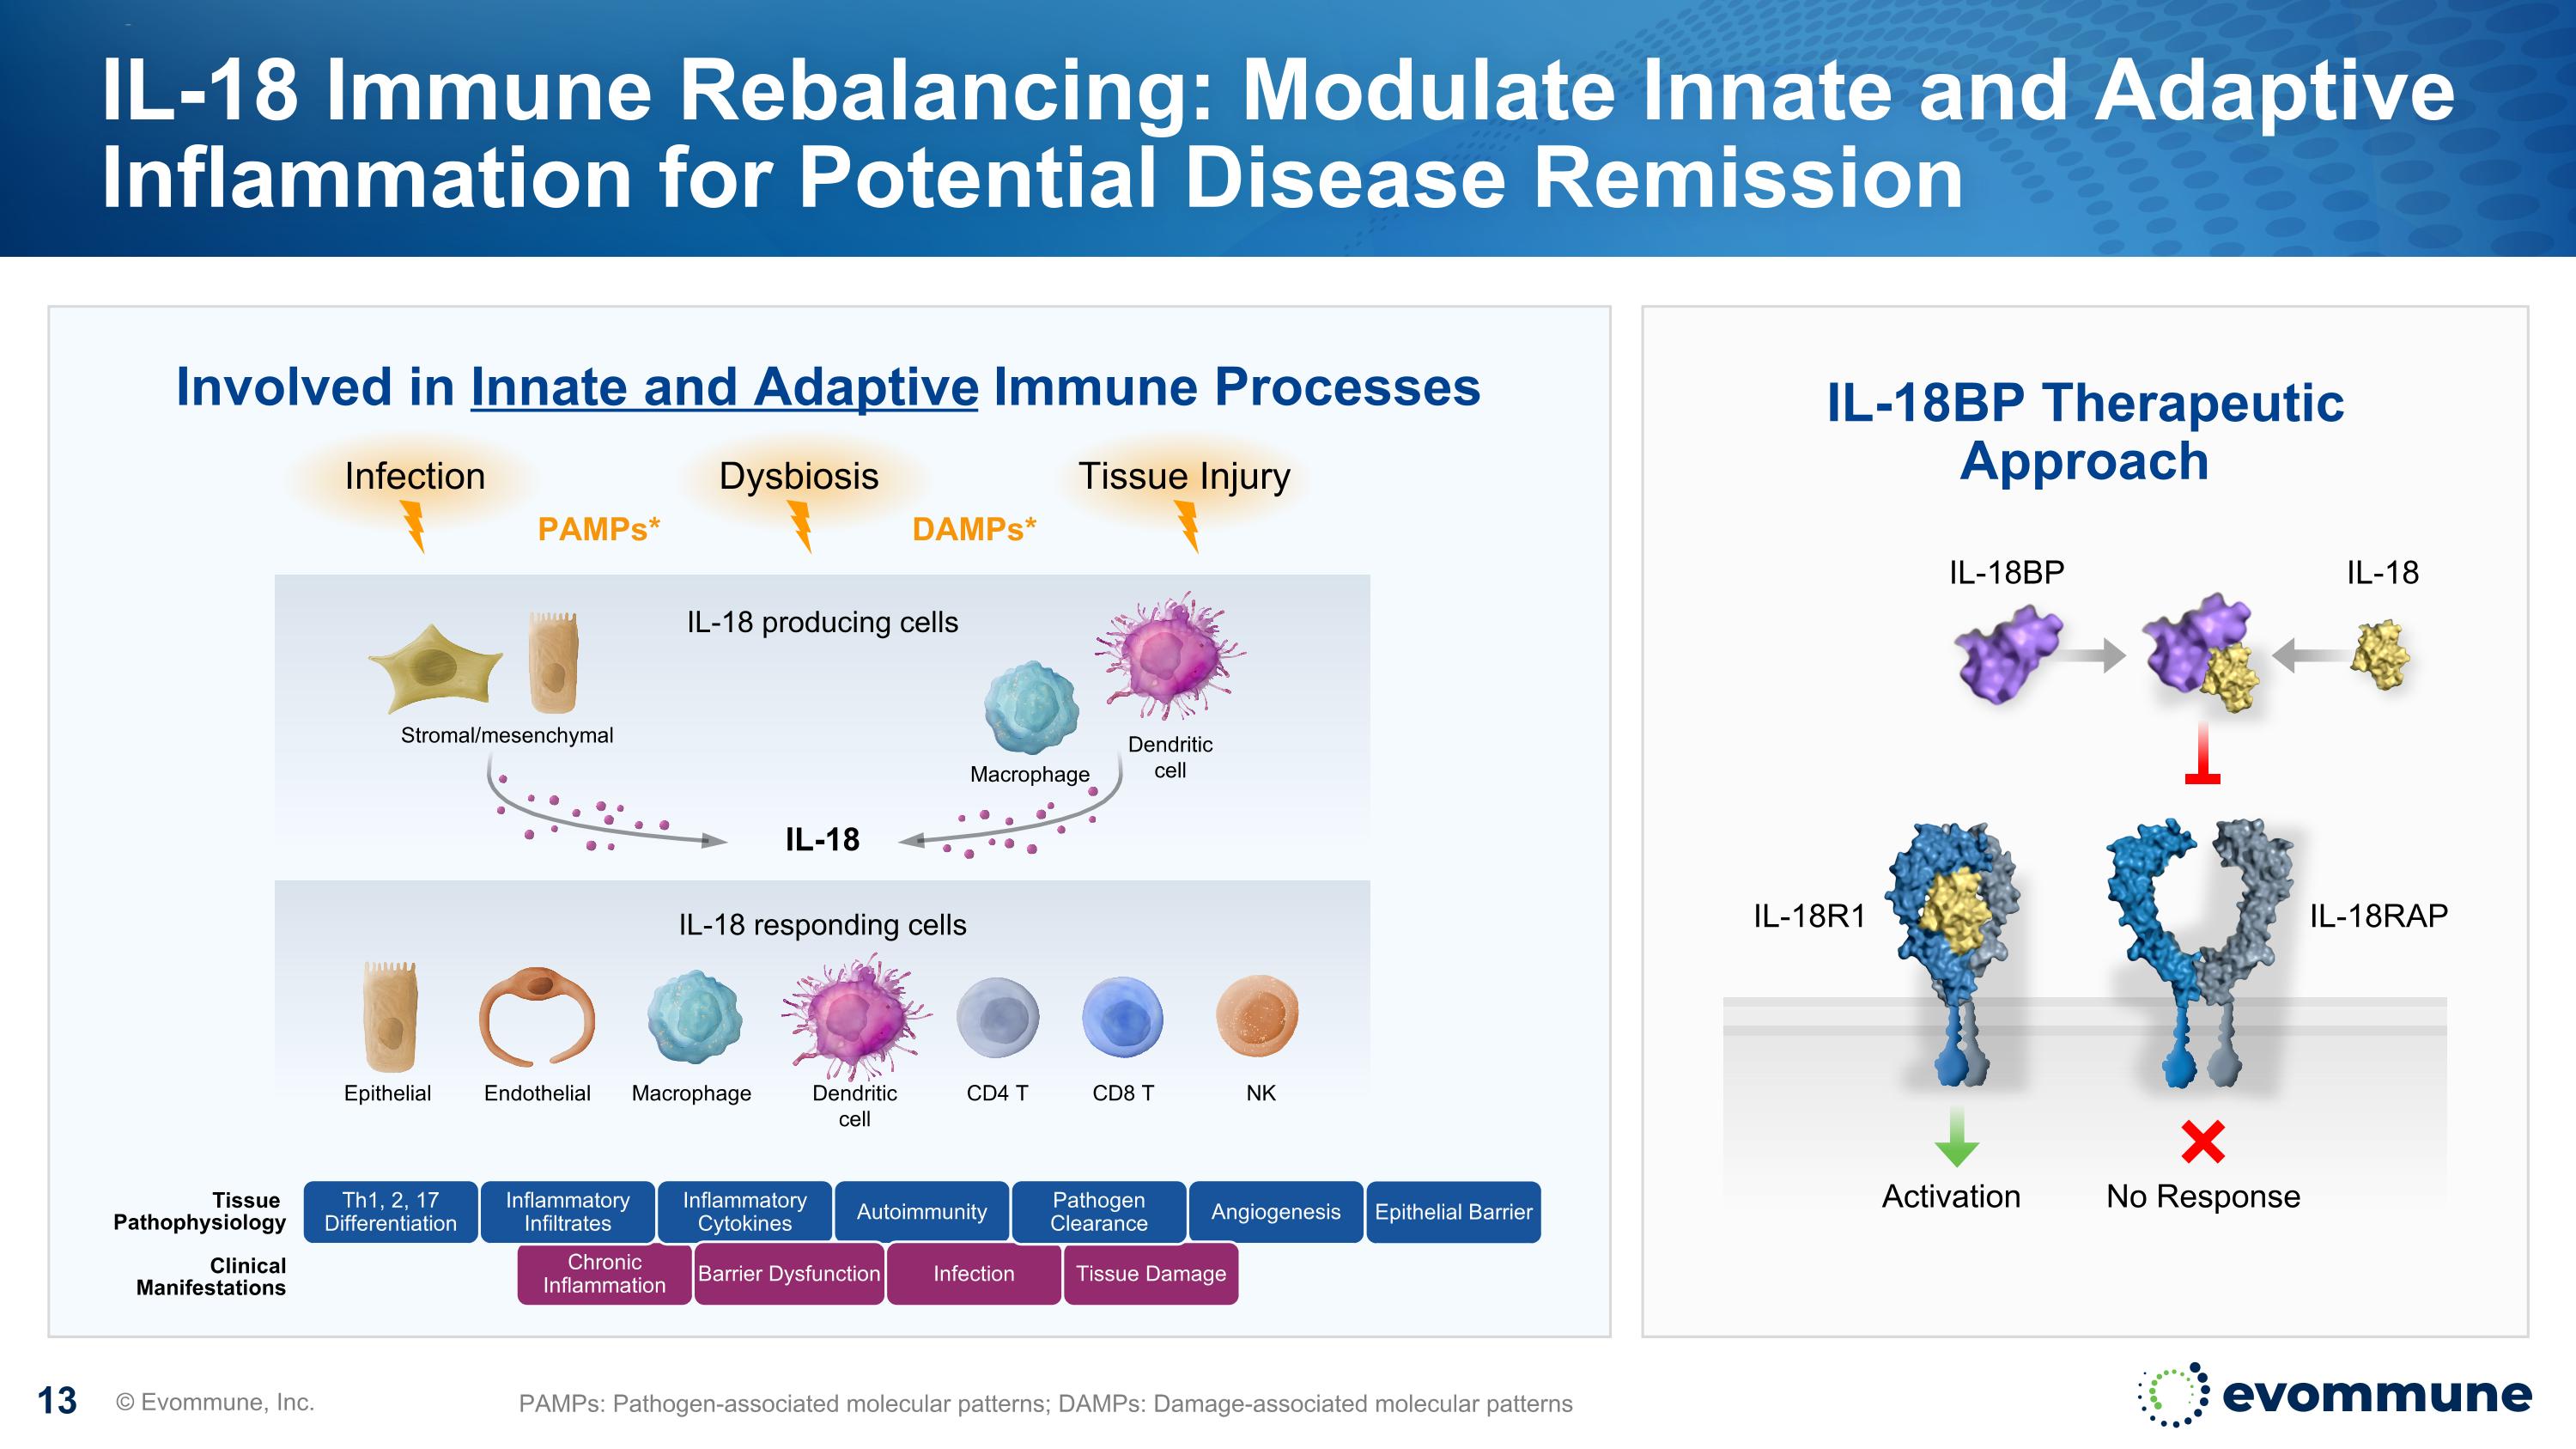
IL-18 Immune Rebalancing: Modulate Innate and Adaptive Inflammation for Potential Disease Remission © Evommune, Inc. PAMPs: Pathogen-associated molecular patterns; DAMPs: Damage-associated molecular patterns Chronic Inflammation Tissue Pathophysiology Clinical Manifestations Inflammatory Infiltrates Inflammatory Cytokines Autoimmunity Angiogenesis Th1, 2, 17 Differentiation Barrier Dysfunction Infection Tissue Damage Pathogen Clearance IL-18BP Therapeutic Approach Involved in Innate and Adaptive Immune Processes IL-18 producing cells IL-18 responding cells Stromal/mesenchymal IL-18 Epithelial Endothelial CD4 T NK CD8 T Macrophage Dendritic cell Dendritic cell Macrophage Dysbiosis Tissue Injury Infection DAMPs* PAMPs* IL-18R1 IL-18RAP No Response Activation IL-18 IL-18BP Epithelial Barrier
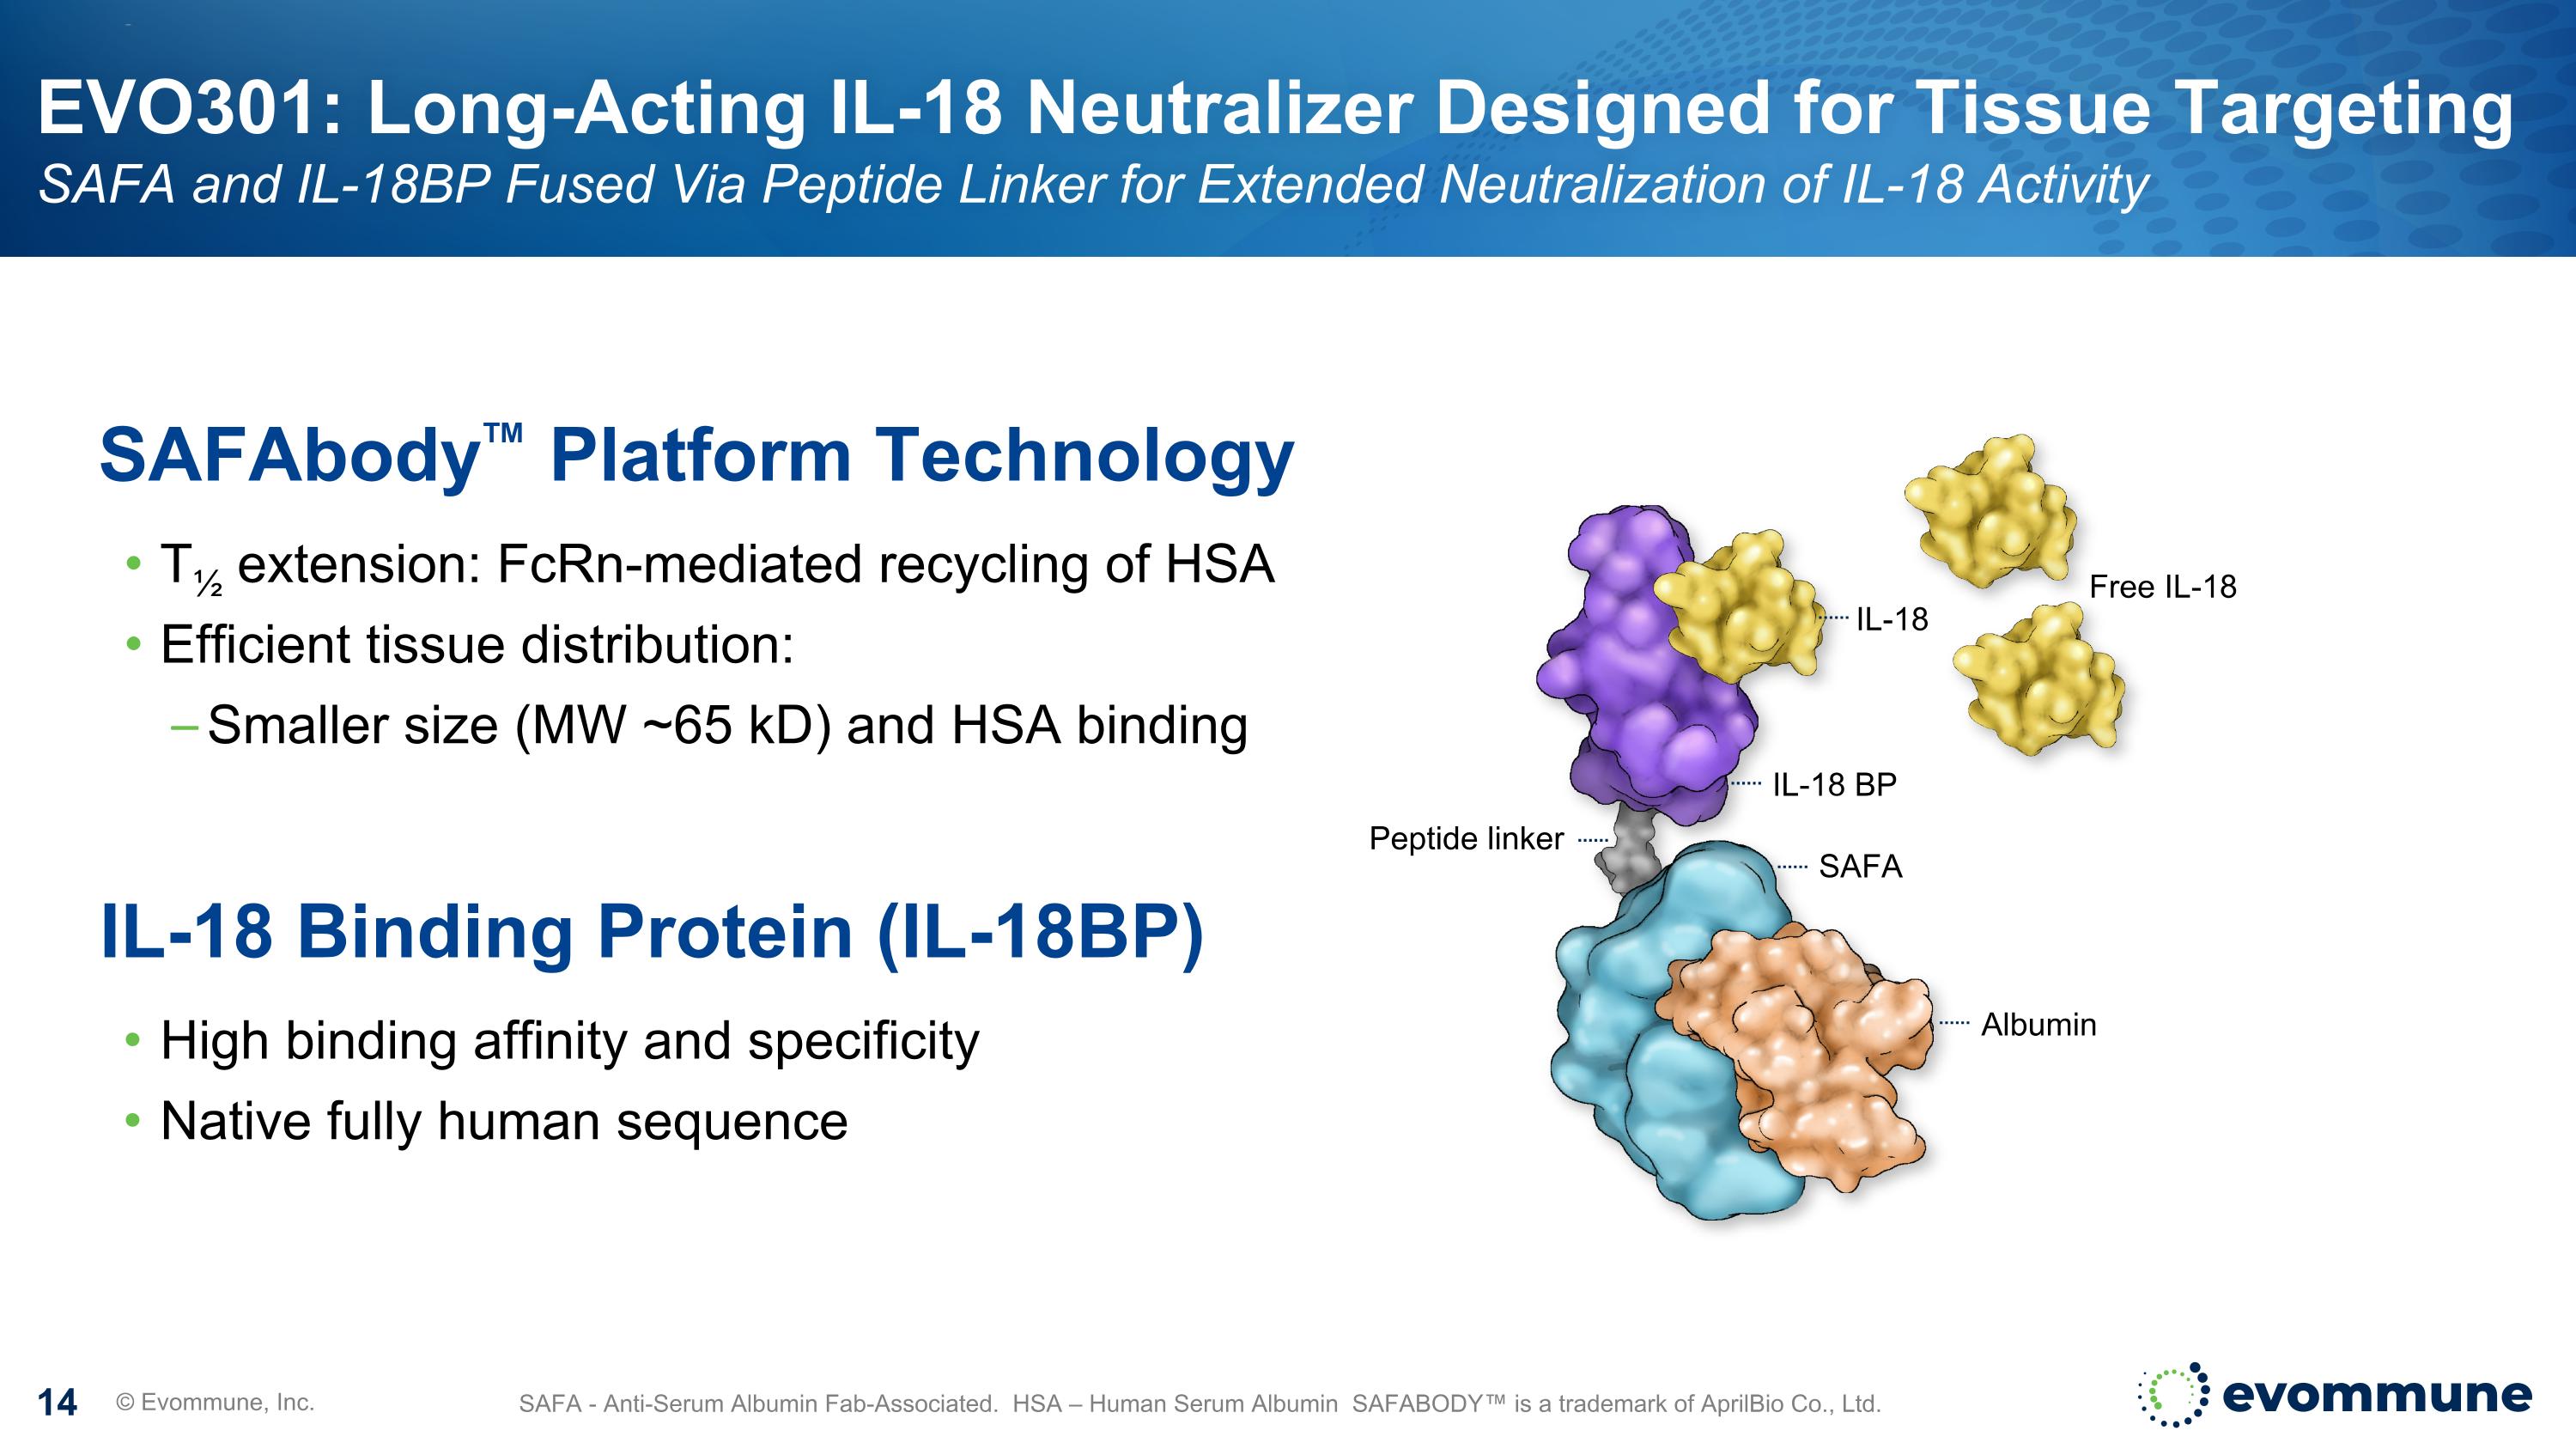
EVO301: Long-Acting IL-18 Neutralizer Designed for Tissue Targeting SAFA and IL-18BP Fused Via Peptide Linker for Extended Neutralization of IL-18 Activity © Evommune, Inc. SAFA - Anti-Serum Albumin Fab-Associated. HSA – Human Serum Albumin SAFABODY™ is a trademark of AprilBio Co., Ltd. Free IL-18 IL-18 IL-18 BP SAFA Peptide linker Albumin SAFAbody™ Platform Technology T½ extension: FcRn-mediated recycling of HSA Efficient tissue distribution: Smaller size (MW ~65 kD) and HSA binding IL-18 Binding Protein (IL-18BP) High binding affinity and specificity Native fully human sequence
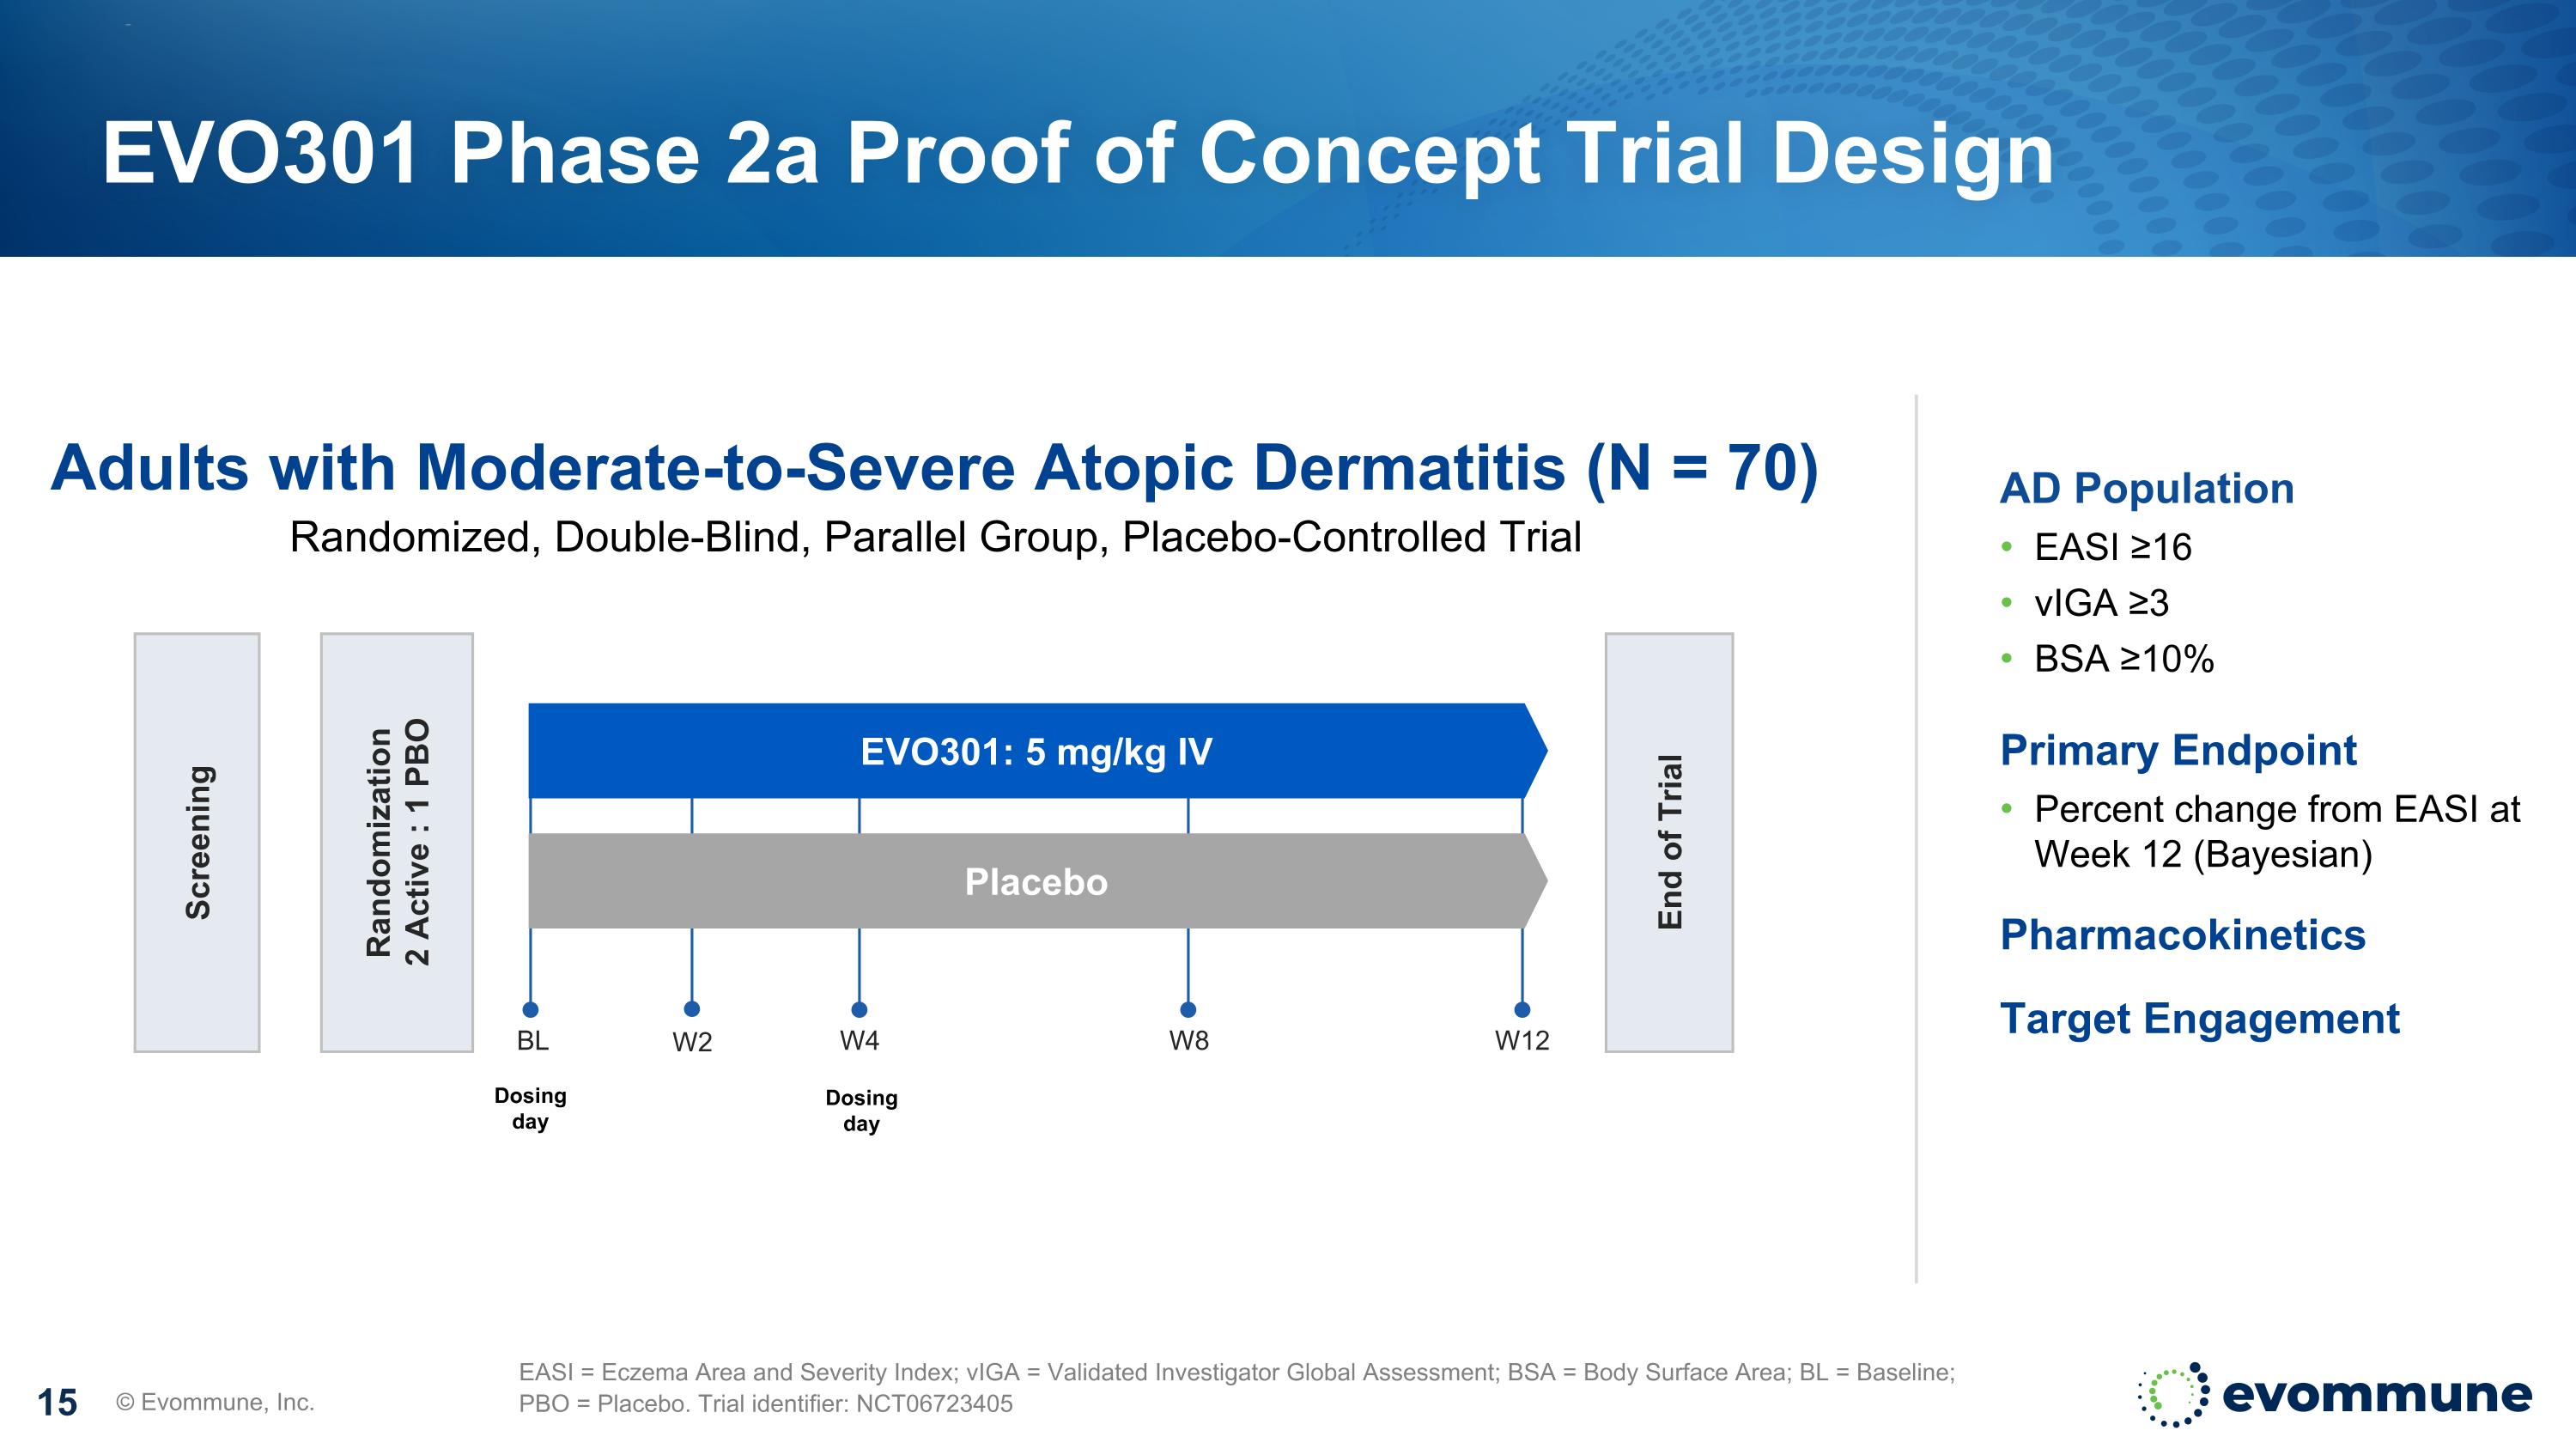
EVO301 Phase 2a Proof of Concept Trial Design © Evommune, Inc. EASI = Eczema Area and Severity Index; vIGA = Validated Investigator Global Assessment; BSA = Body Surface Area; BL = Baseline; PBO = Placebo. Trial identifier: NCT06723405 Adults with Moderate-to-Severe Atopic Dermatitis (N = 70) Randomized, Double-Blind, Parallel Group, Placebo-Controlled Trial AD Population EASI ≥16 vIGA ≥3 BSA ≥10% Primary Endpoint Percent change from EASI at Week 12 (Bayesian) Pharmacokinetics Target Engagement Screening Randomization 2 Active : 1 PBO End of Trial BL W12 W4 W8 EVO301: 5 mg/kg IV Placebo Dosing day Dosing day W2
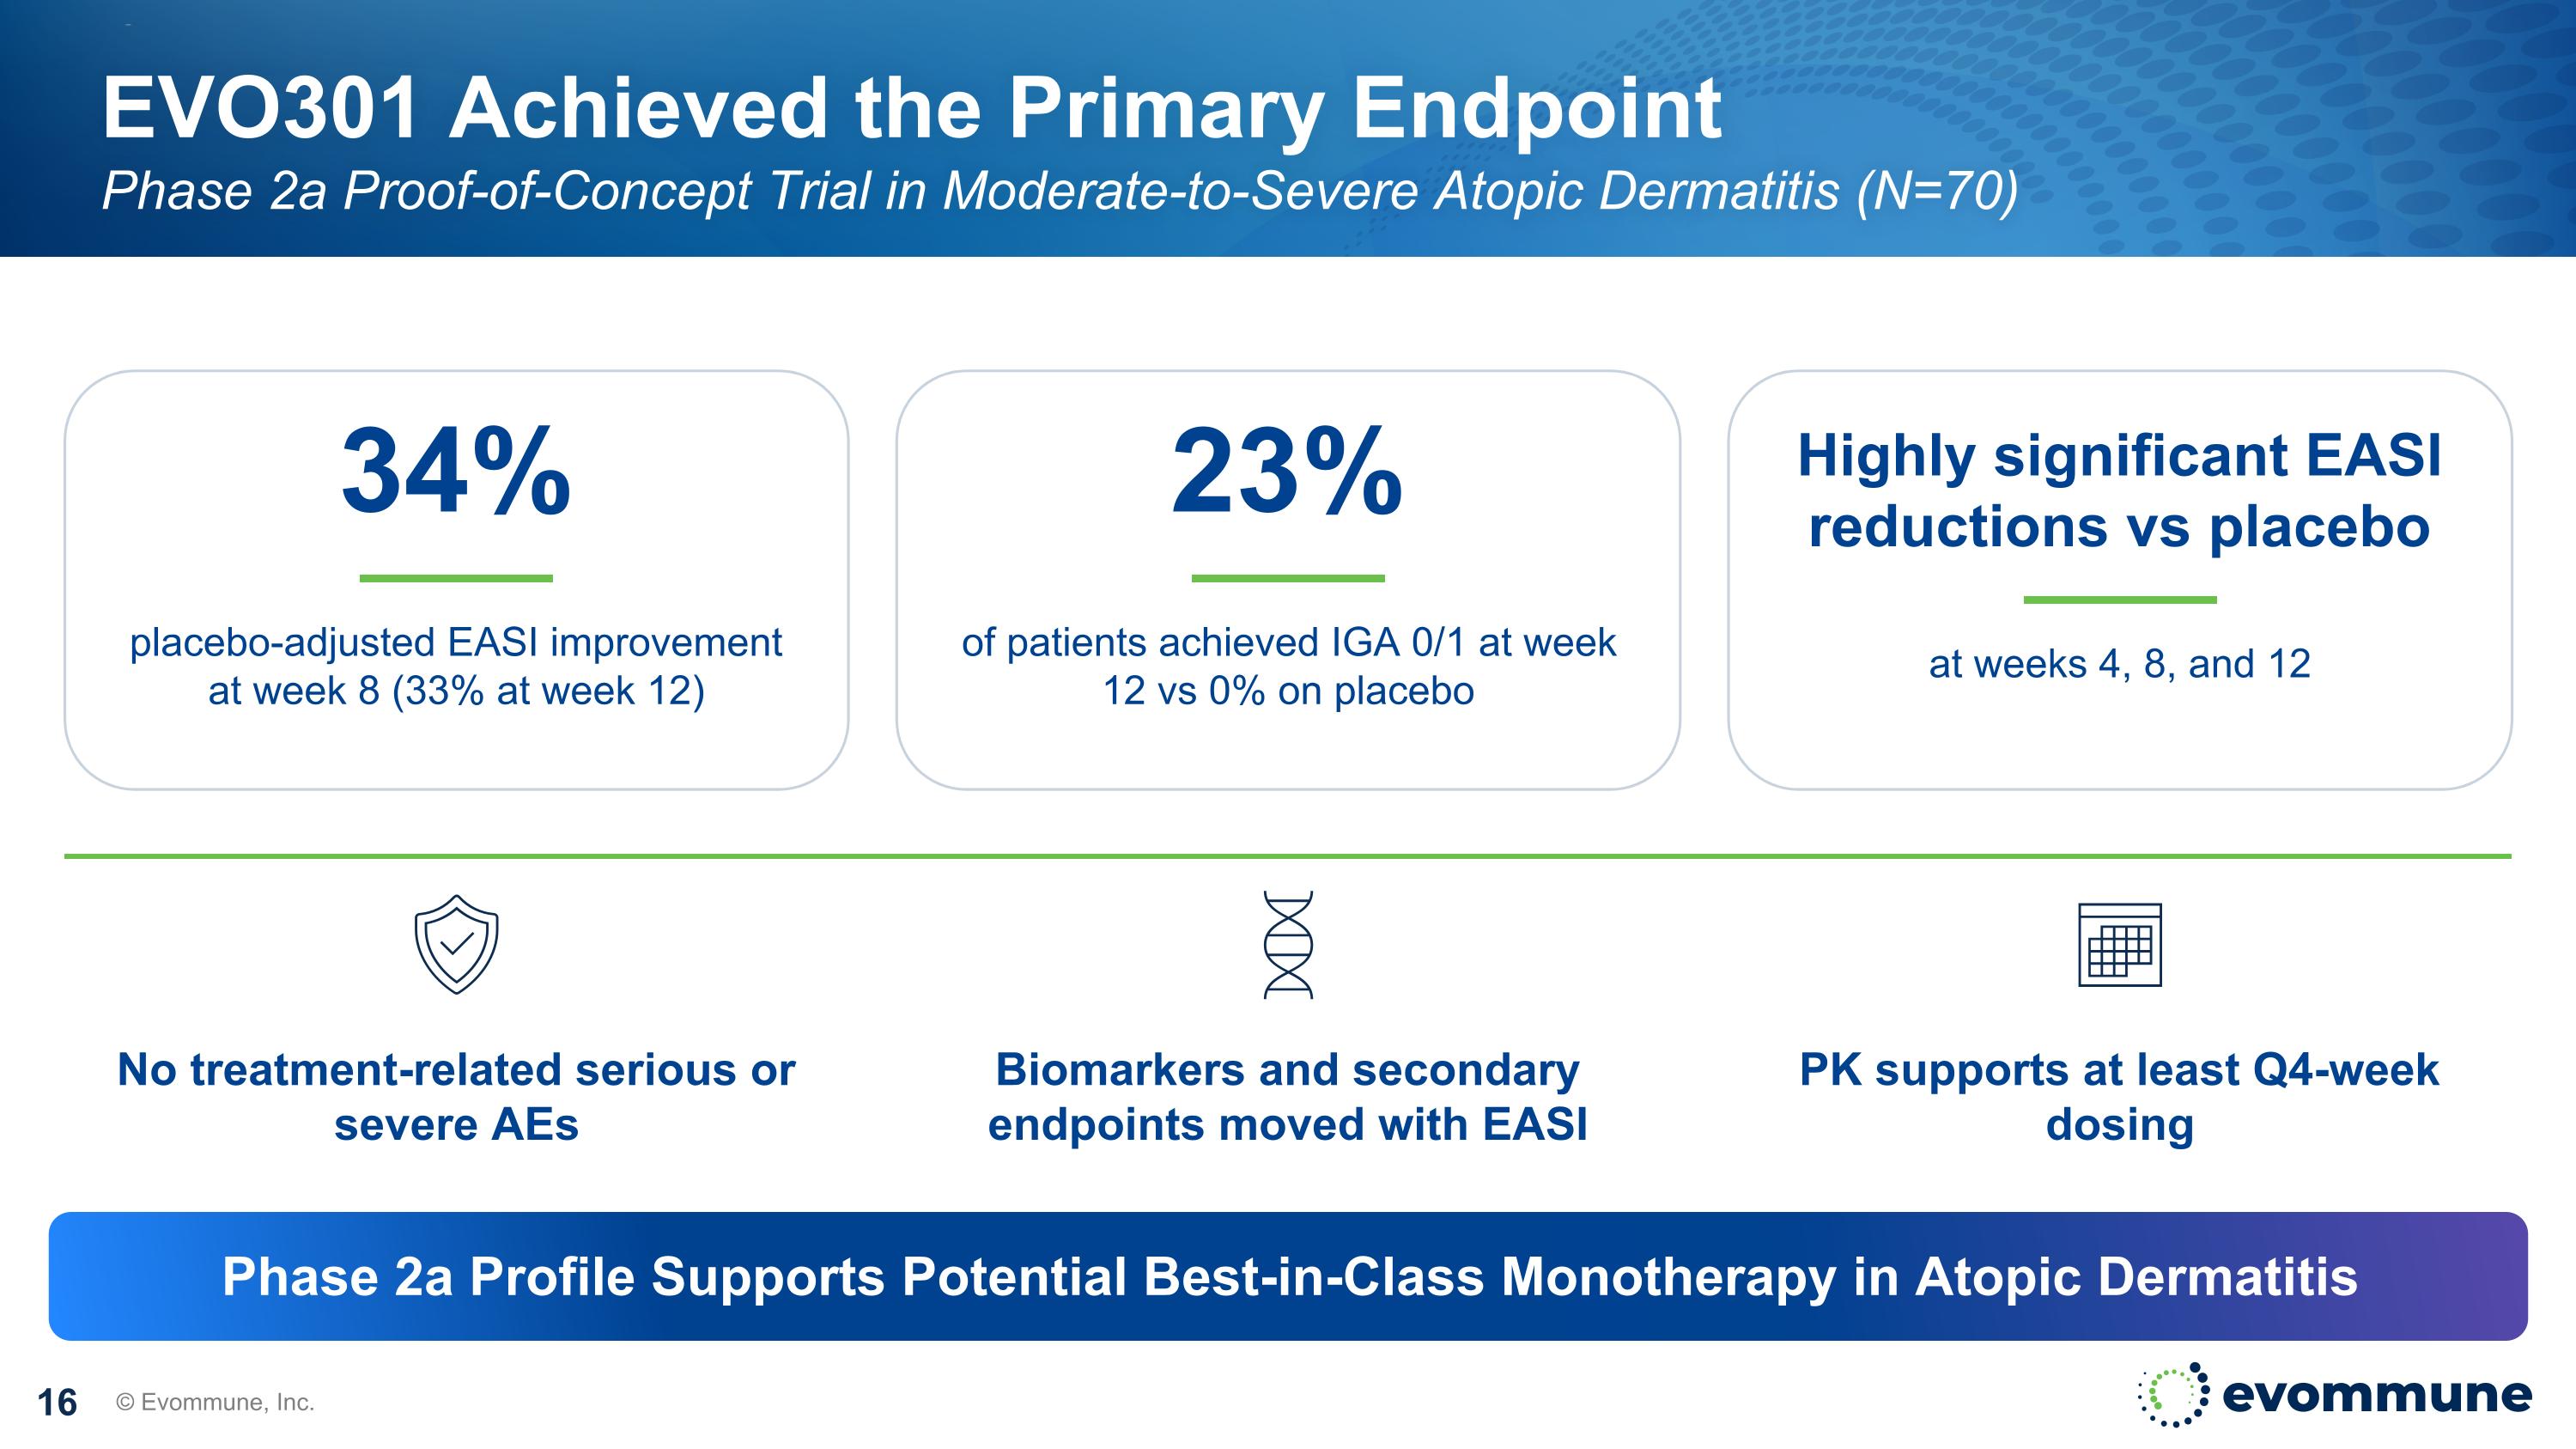
EVO301 Achieved the Primary Endpoint Phase 2a Proof-of-Concept Trial in Moderate-to-Severe Atopic Dermatitis (N=70) © Evommune, Inc. 34% placebo-adjusted EASI improvement at week 8 (33% at week 12) 23% of patients achieved IGA 0/1 at week 12 vs 0% on placebo Highly significant EASI reductions vs placebo at weeks 4, 8, and 12 No treatment-related serious or severe AEs Biomarkers and secondary endpoints moved with EASI PK supports at least Q4-week dosing Phase 2a Profile Supports Potential Best-in-Class Monotherapy in Atopic Dermatitis
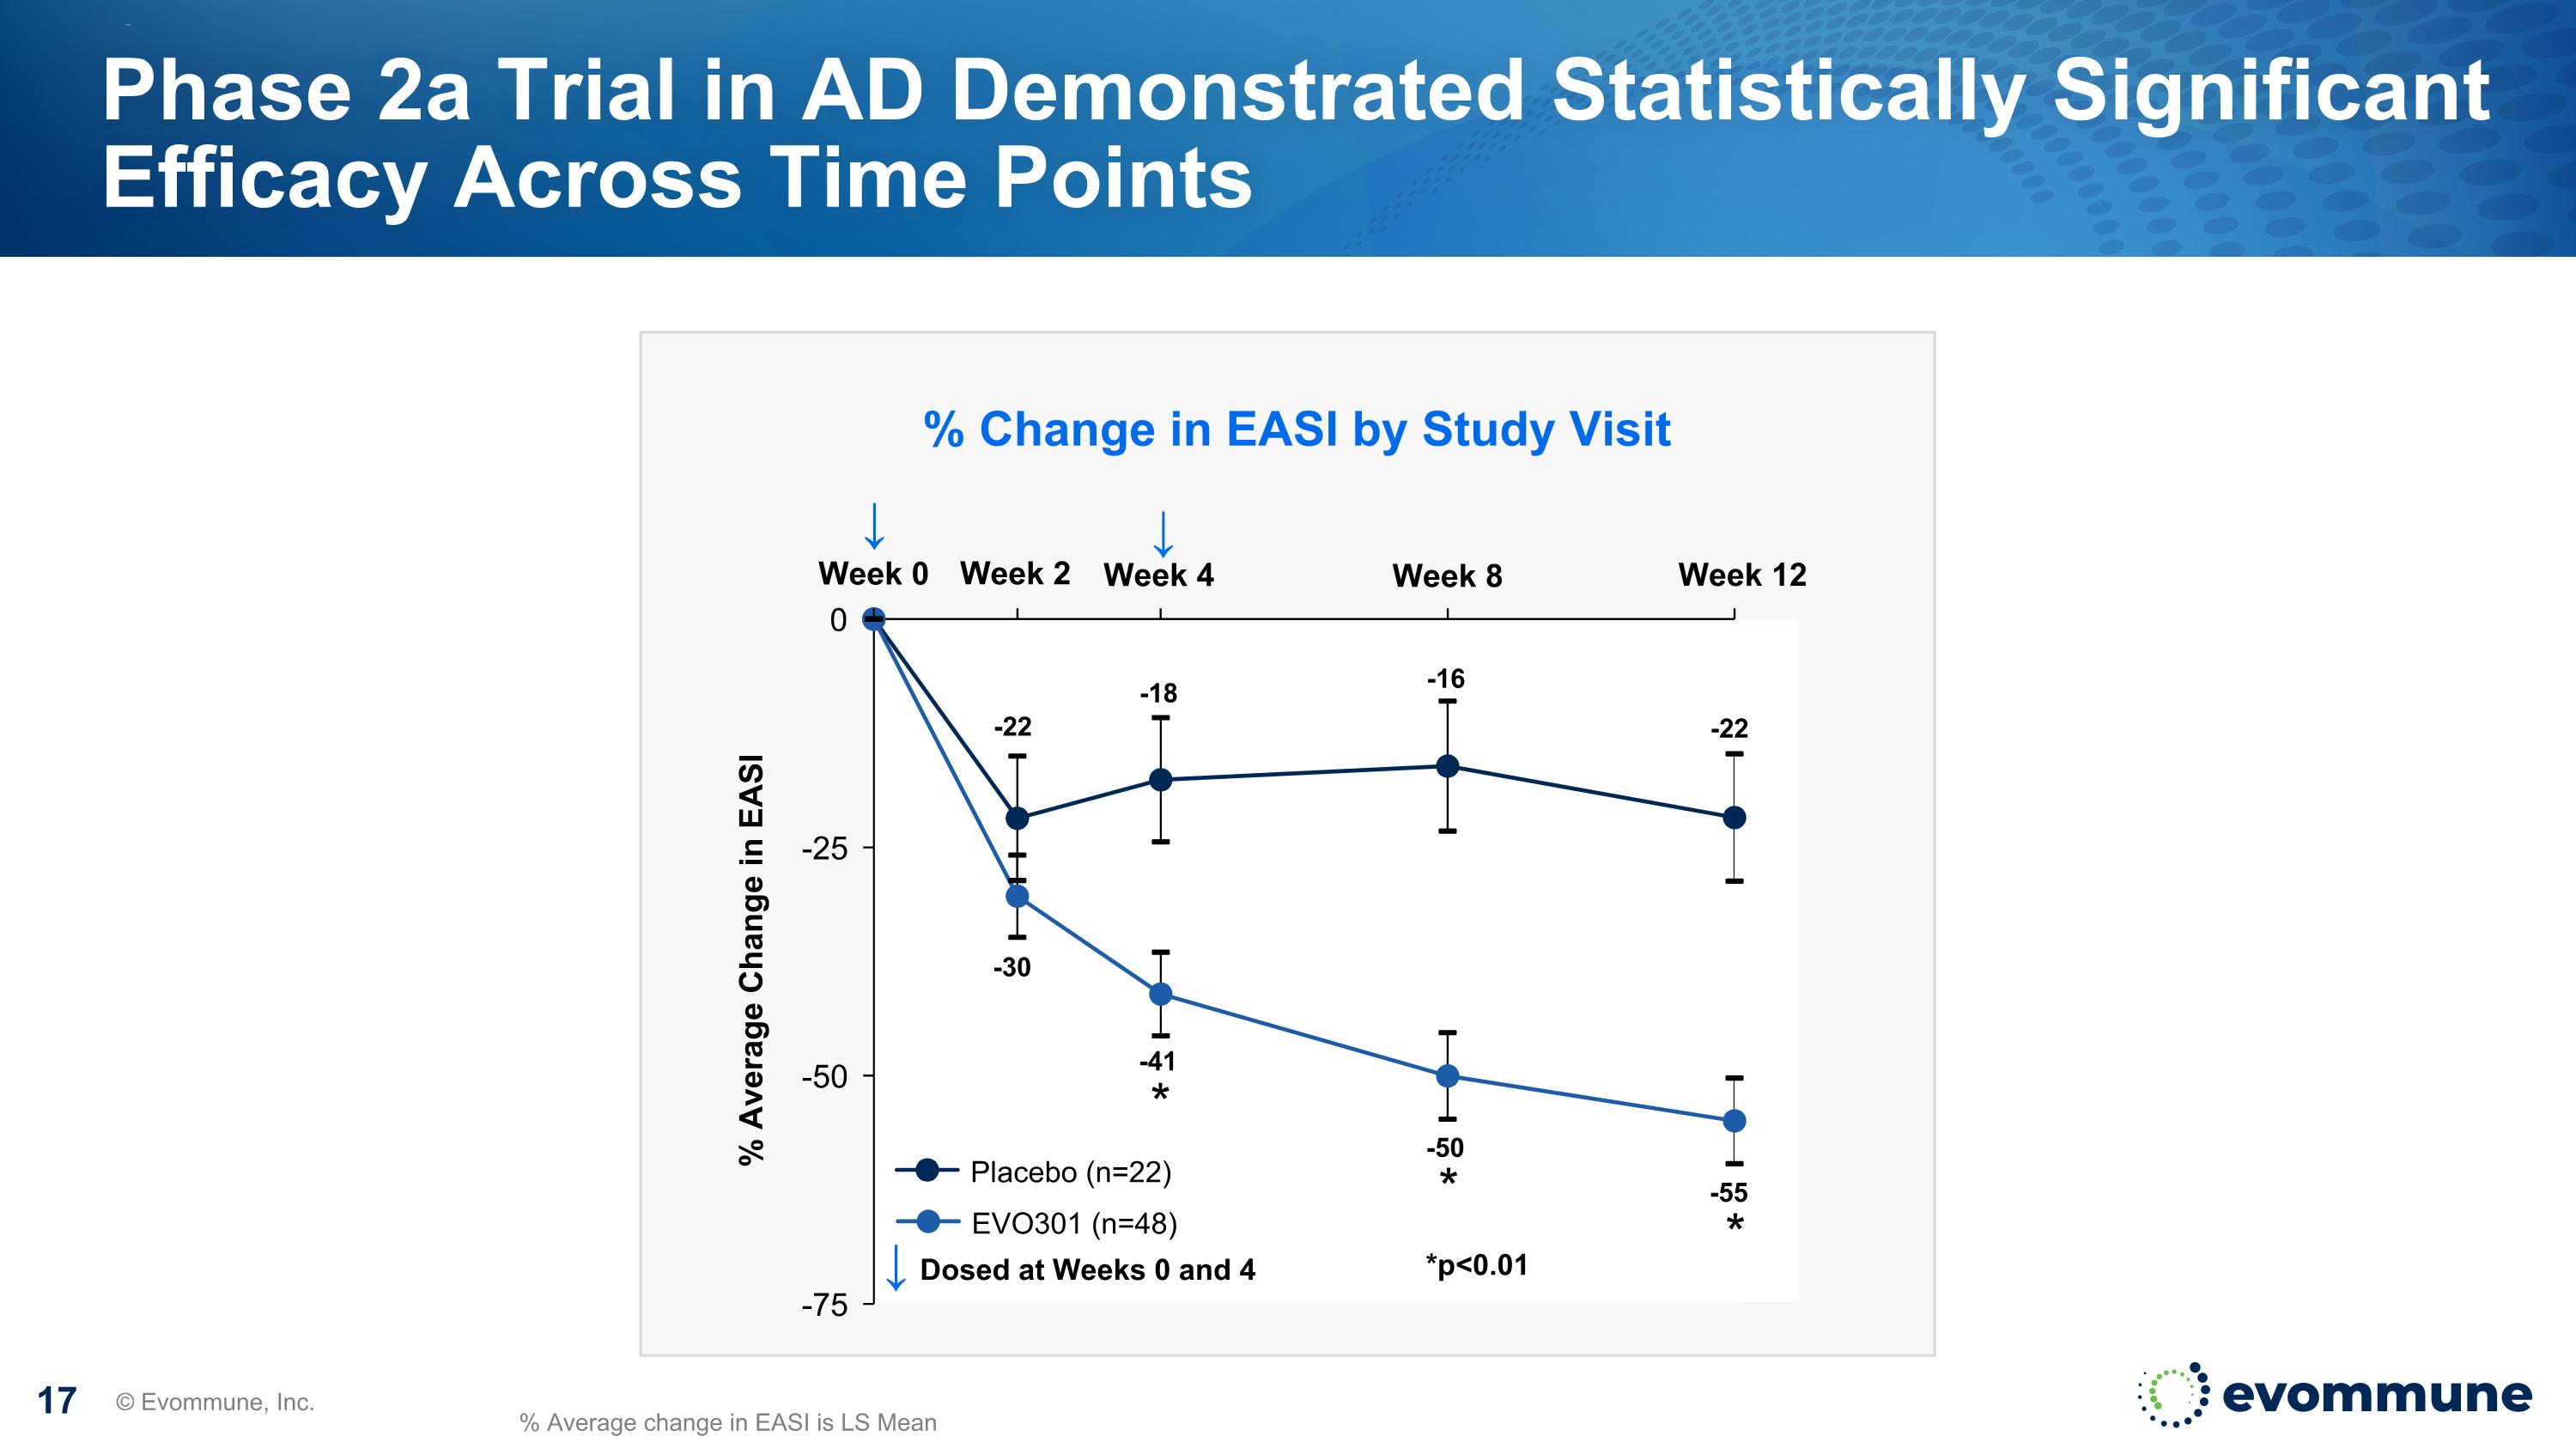
Week 2 Phase 2a Trial in AD Demonstrated Statistically Significant Efficacy Across Time Points © Evommune, Inc. Week 0 Week 4 Week 8 Week 12 % Average Change in EASI ↓ Dosed at Weeks 0 and 4 Placebo (n=22) EVO301 (n=48) * * % Change in EASI by Study Visit *p<0.01 ↓ % Average change in EASI is LS Mean -22 -18 -16 -22 -30 -41 -50 -55 ↓ *
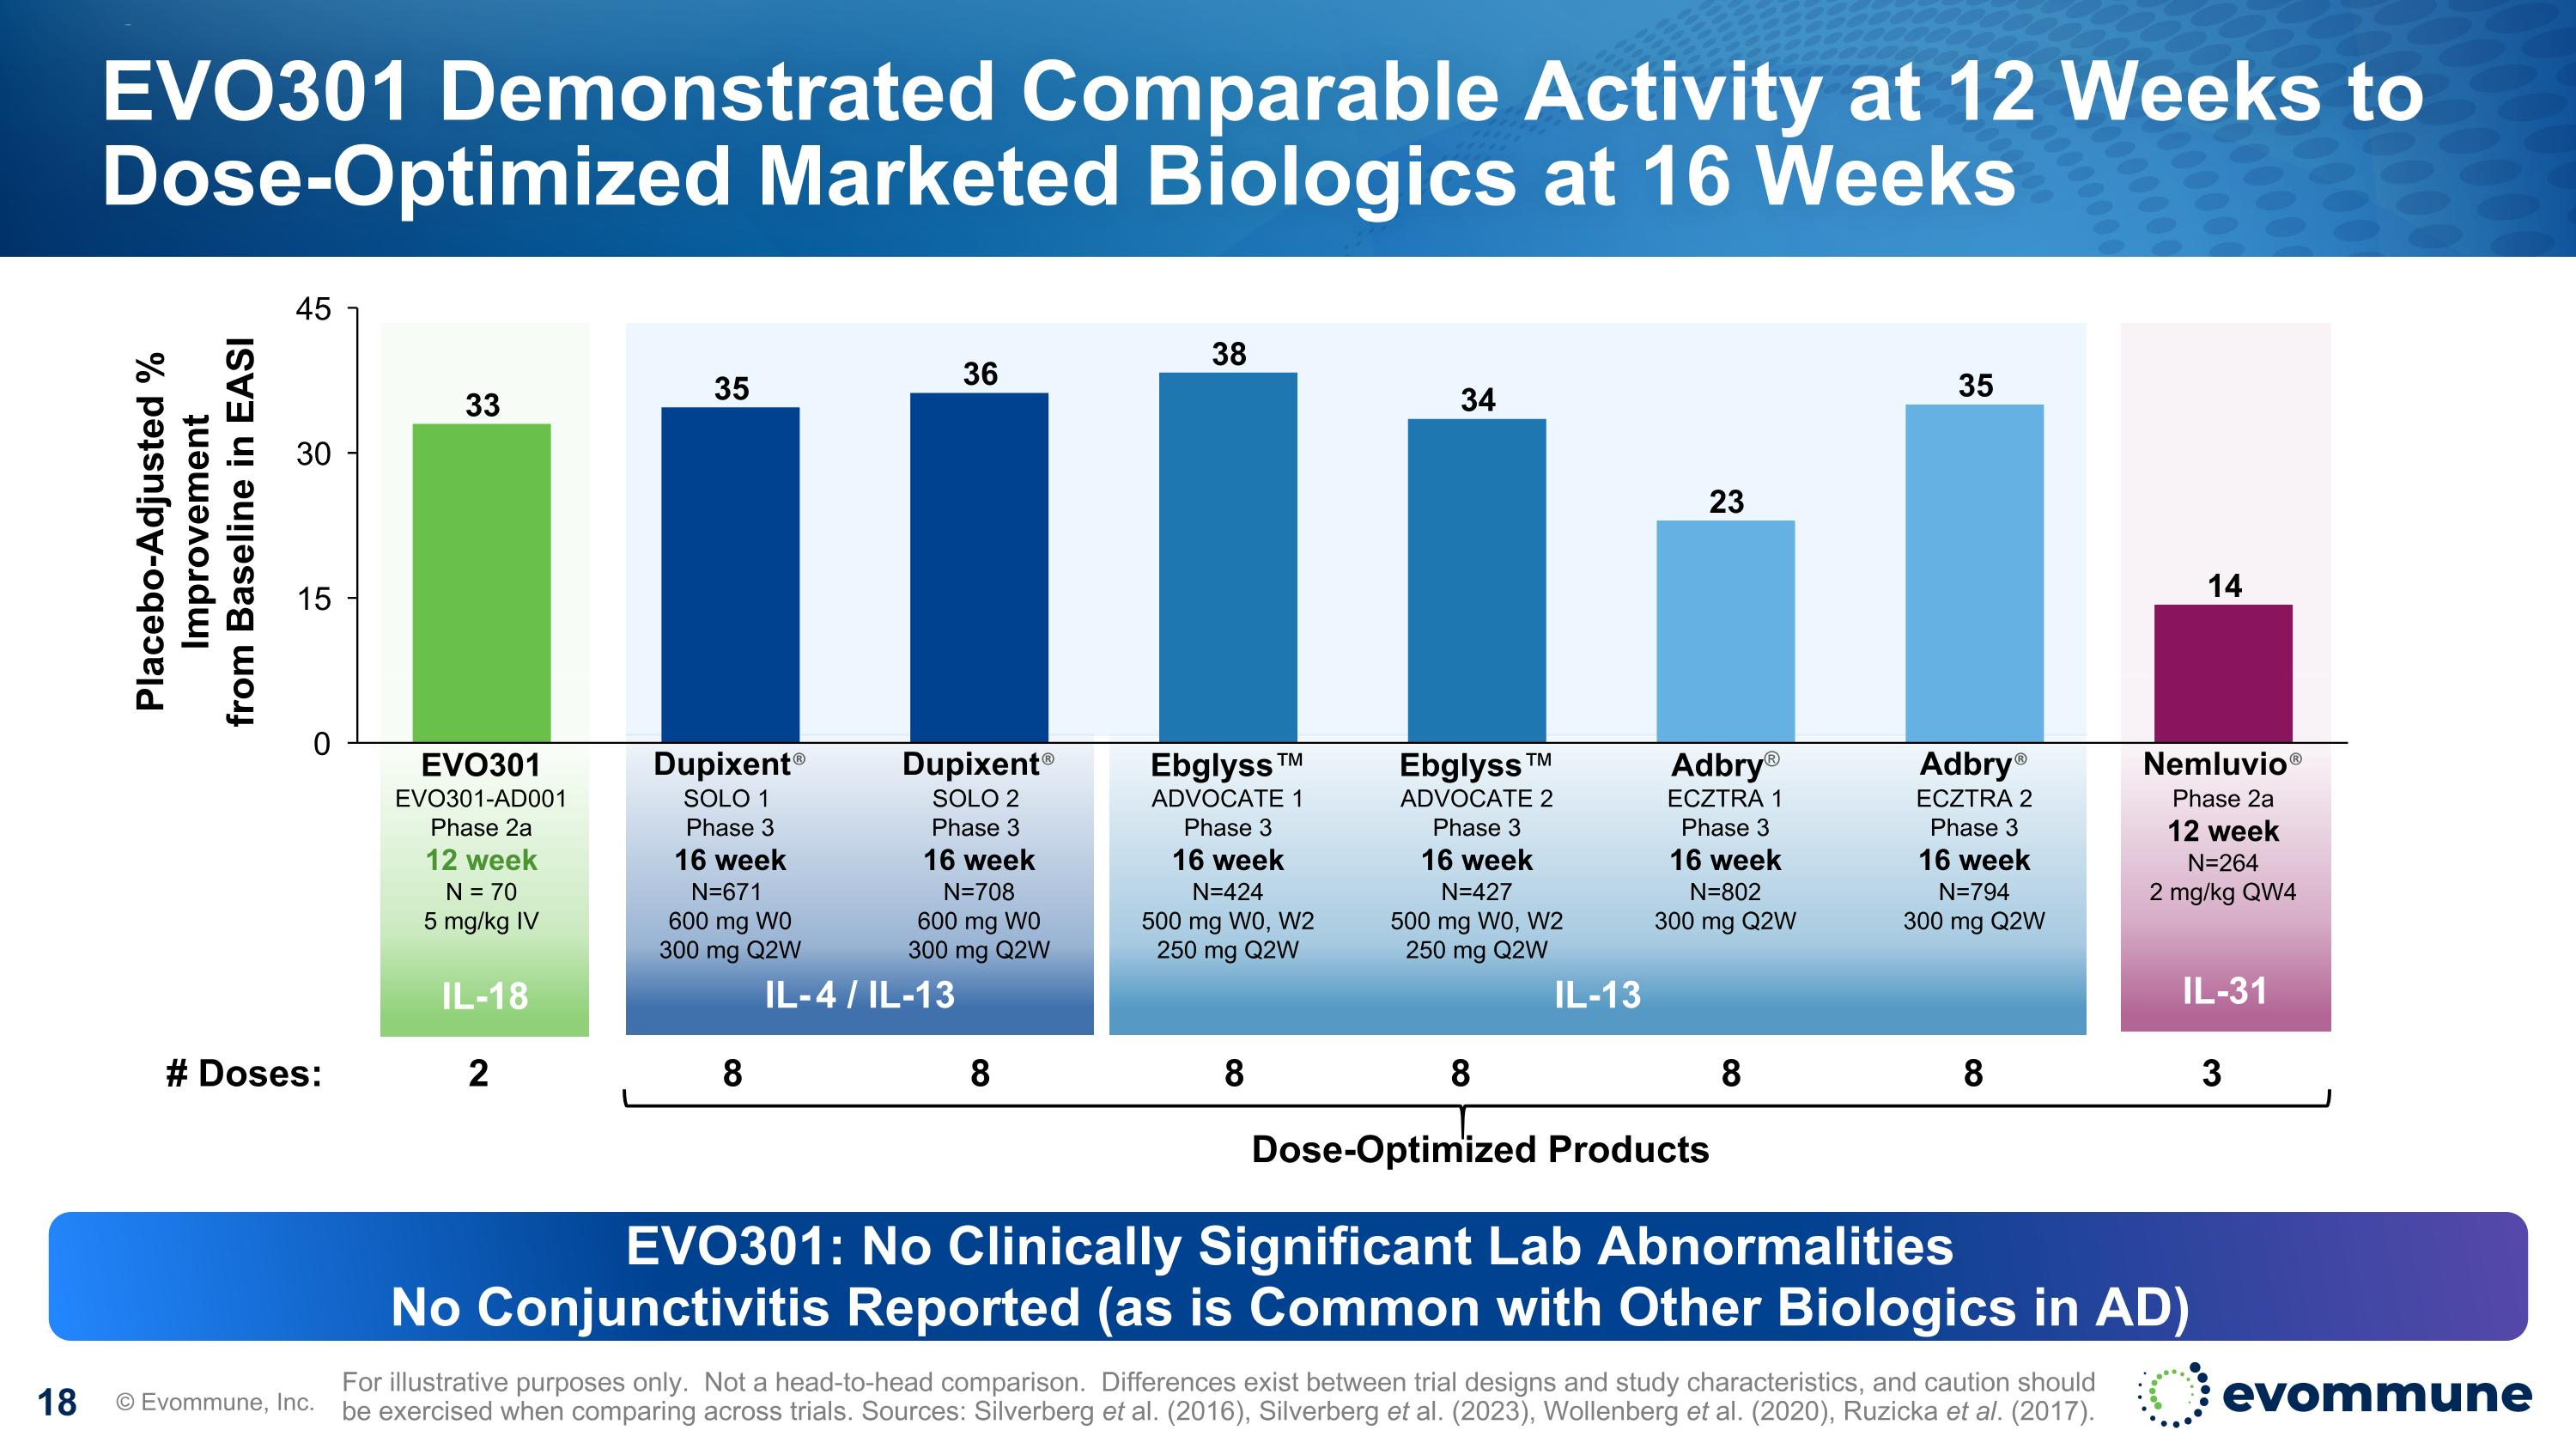
IL-18 IL-31 IL-13 IL-4 / IL-13 EVO301 Demonstrated Comparable Activity at 12 Weeks to Dose-Optimized Marketed Biologics at 16 Weeks © Evommune, Inc. For illustrative purposes only. Not a head-to-head comparison. Differences exist between trial designs and study characteristics, and caution should be exercised when comparing across trials. Sources: Silverberg et al. (2016), Silverberg et al. (2023), Wollenberg et al. (2020), Ruzicka et al. (2017). Placebo-Adjusted % Improvement from Baseline in EASI Dose-Optimized Products # Doses: 2 8 8 8 8 8 8 3 EVO301 EVO301-AD001 Phase 2a 12 week N = 70 5 mg/kg IV Dupixent® SOLO 1 Phase 3 16 week N=671 600 mg W0 300 mg Q2W Dupixent® SOLO 2 Phase 3 16 week N=708 600 mg W0 300 mg Q2W Ebglyss™ ADVOCATE 1 Phase 3 16 week N=424 500 mg W0, W2 250 mg Q2W Ebglyss™ ADVOCATE 2 Phase 3 16 week N=427 500 mg W0, W2 250 mg Q2W Adbry® ECZTRA 1 Phase 3 16 week N=802 300 mg Q2W Adbry® ECZTRA 2 Phase 3 16 week N=794 300 mg Q2W Nemluvio® Phase 2a 12 week N=264 2 mg/kg QW4 EVO301: No Clinically Significant Lab Abnormalities No Conjunctivitis Reported (as is Common with Other Biologics in AD)
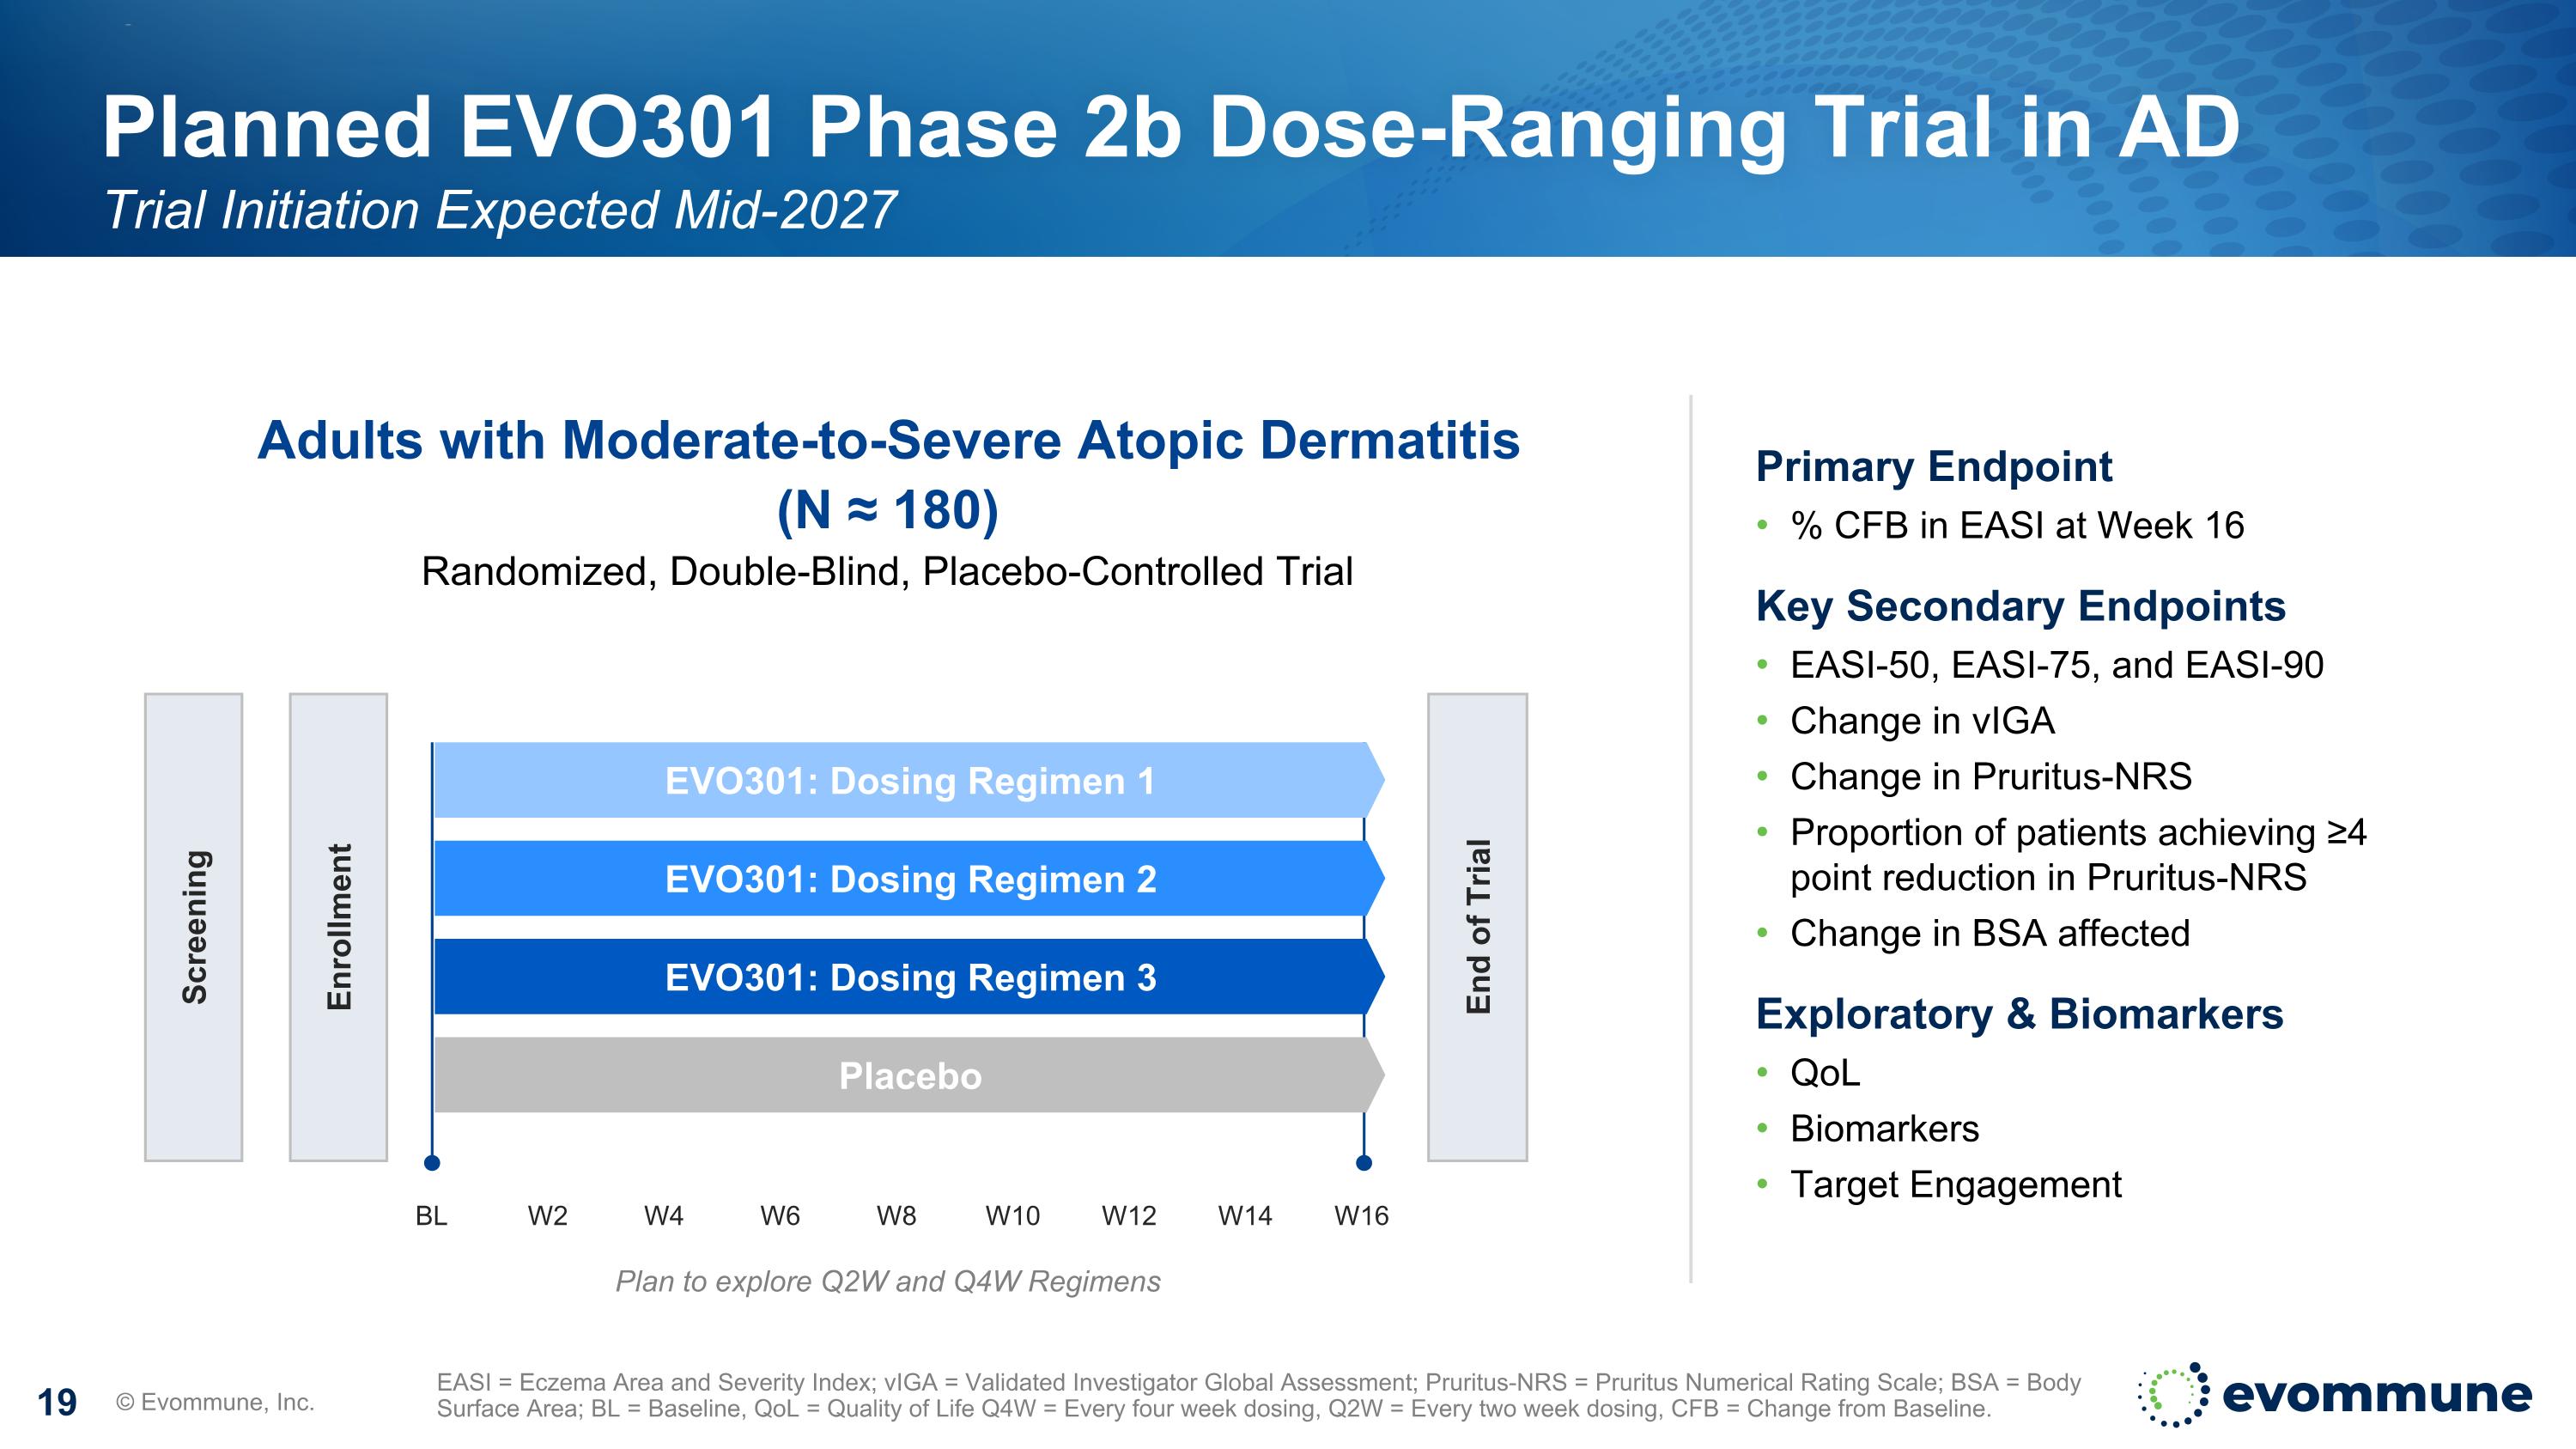
Planned EVO301 Phase 2b Dose-Ranging Trial in AD Trial Initiation Expected Mid-2027 © Evommune, Inc. EASI = Eczema Area and Severity Index; vIGA = Validated Investigator Global Assessment; Pruritus-NRS = Pruritus Numerical Rating Scale; BSA = Body Surface Area; BL = Baseline, QoL = Quality of Life Q4W = Every four week dosing, Q2W = Every two week dosing, CFB = Change from Baseline. Primary Endpoint % CFB in EASI at Week 16 Key Secondary Endpoints EASI-50, EASI-75, and EASI-90 Change in vIGA Change in Pruritus-NRS Proportion of patients achieving ≥4 point reduction in Pruritus-NRS Change in BSA affected Exploratory & Biomarkers QoL Biomarkers Target Engagement BL W16 Adults with Moderate-to-Severe Atopic Dermatitis (N ≈ 180) Randomized, Double-Blind, Placebo-Controlled Trial Screening Enrollment End of Trial W10 EVO301: Dosing Regimen 1 EVO301: Dosing Regimen 2 EVO301: Dosing Regimen 3 Placebo W2 W6 W4 W8 W12 W14 Plan to explore Q2W and Q4W Regimens

EVO756: Oral MRGPRX2 Antagonist Potential First- and Best-in-Class Dual Mechanism Modulates Both Peripheral Sensory Neurons and Mast Cells © Evommune, Inc.
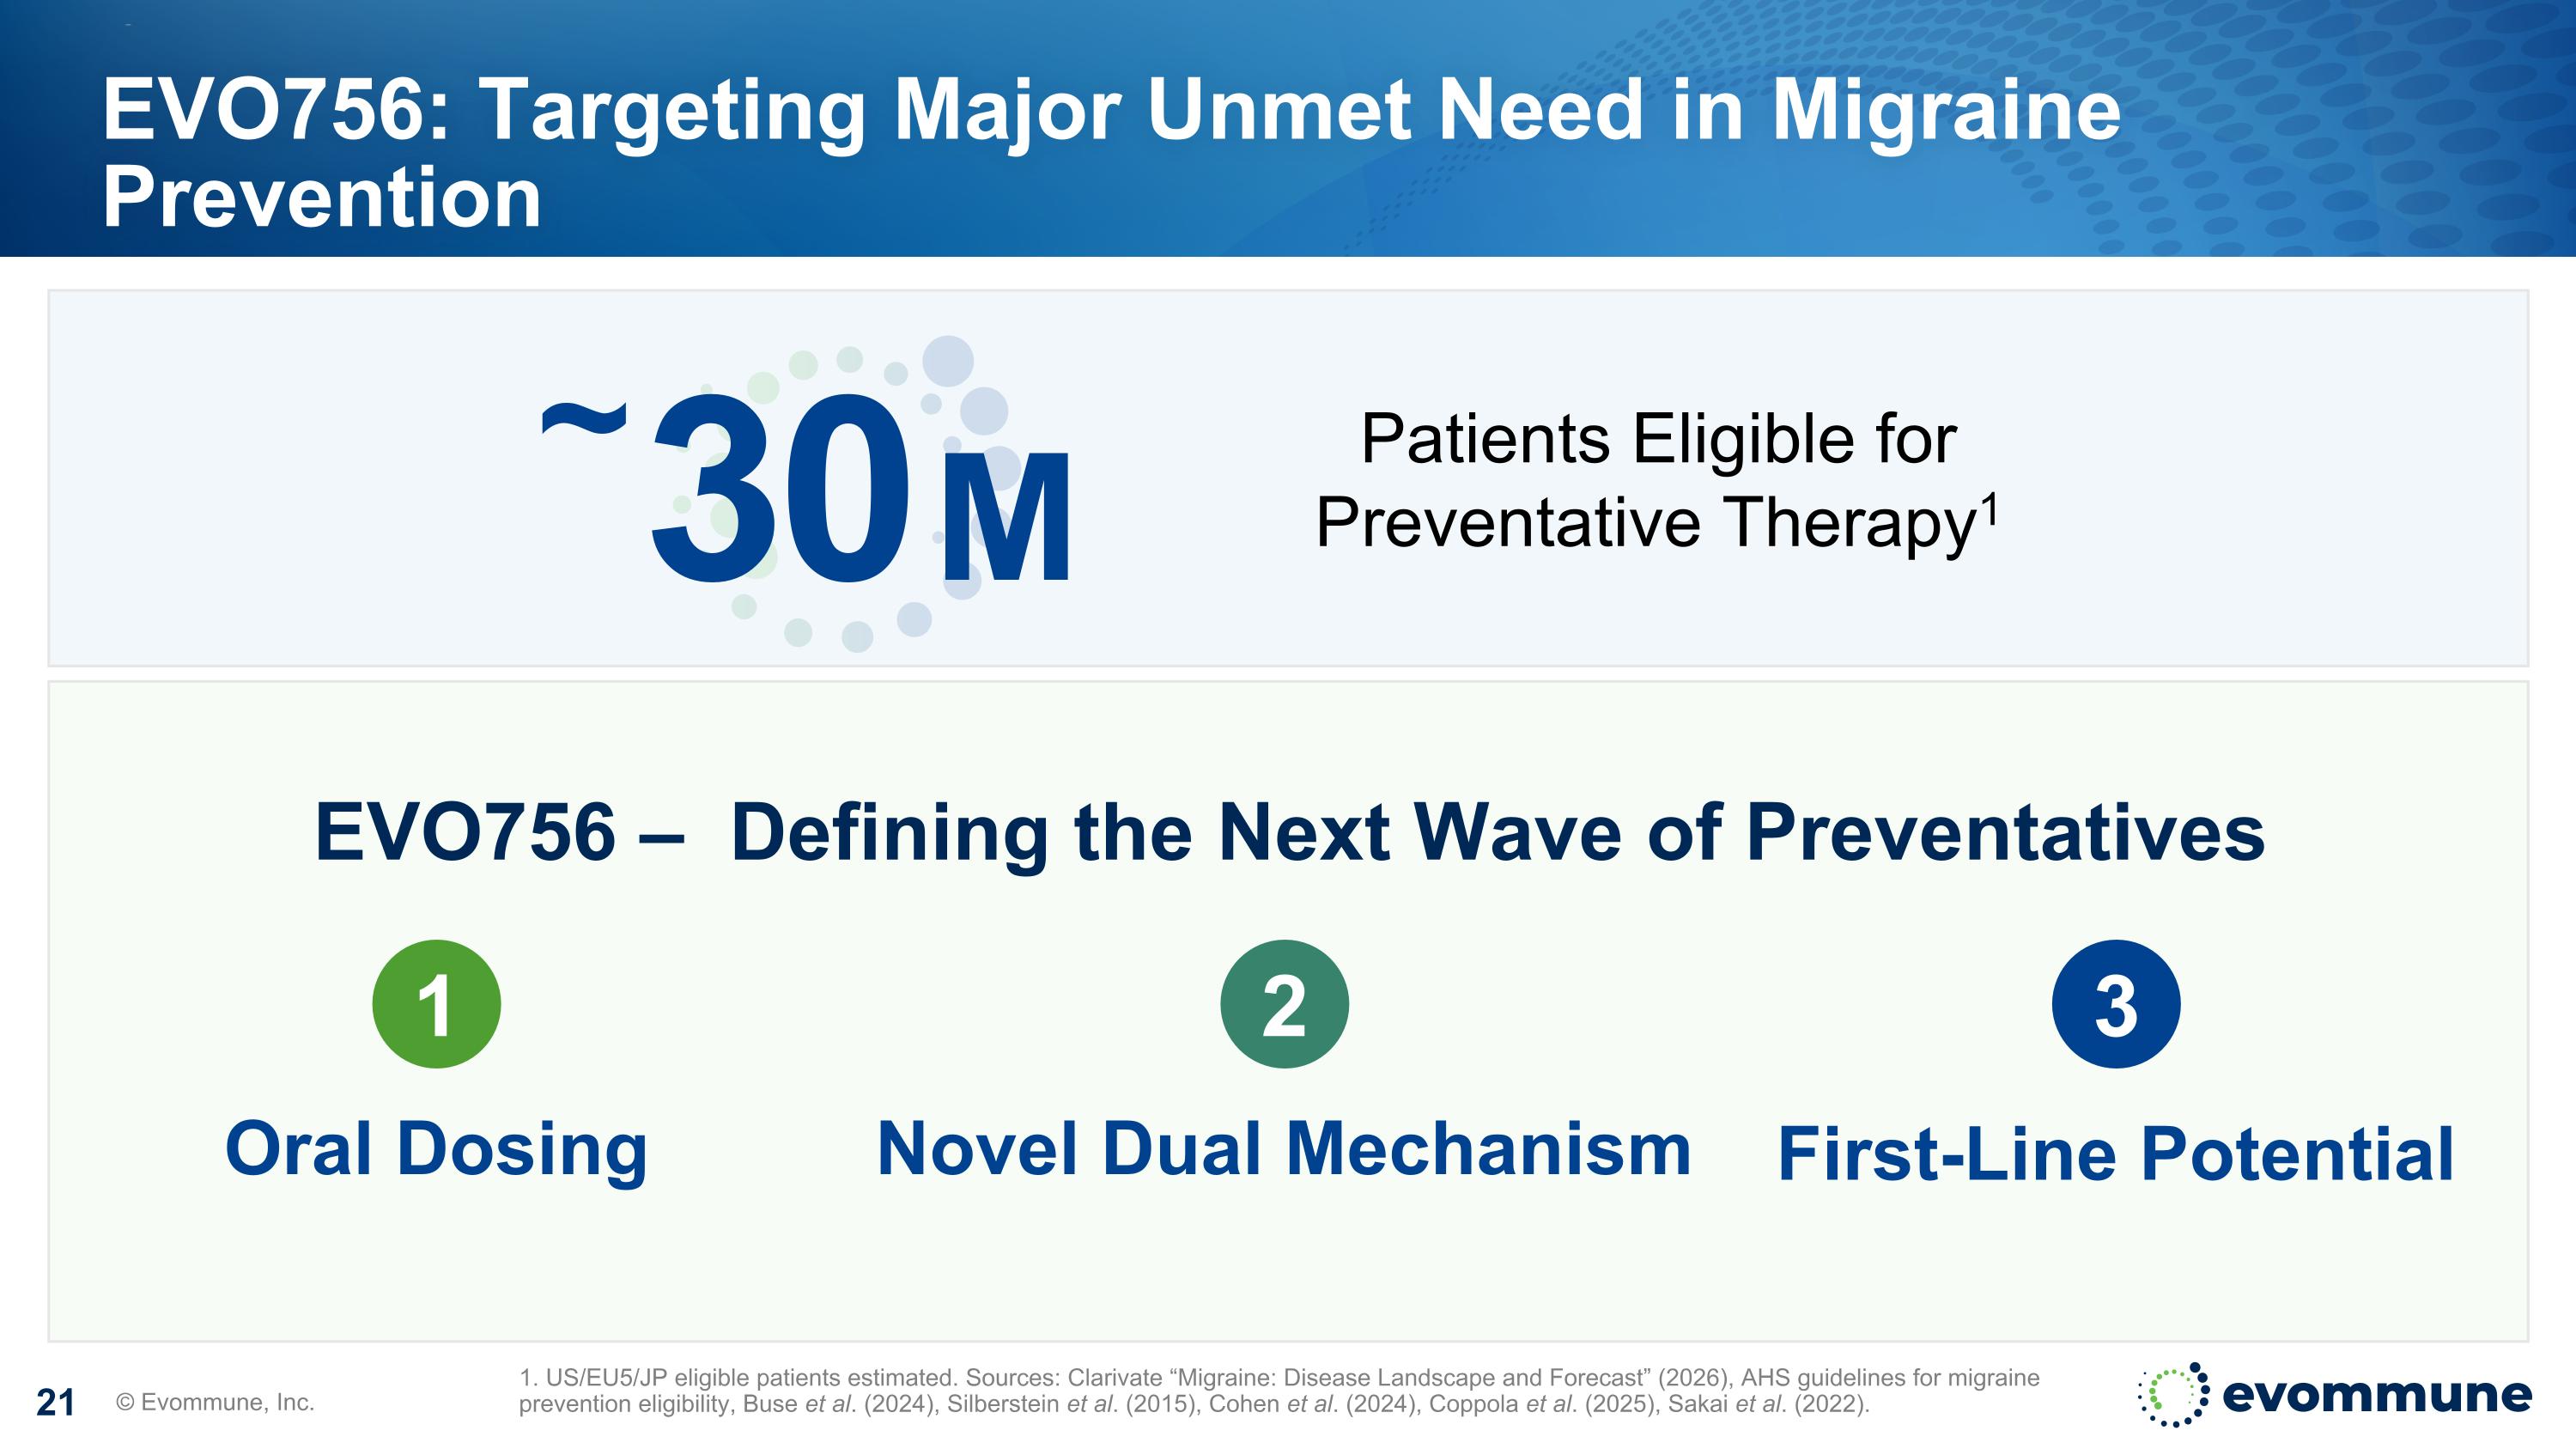
EVO756: Targeting Major Unmet Need in Migraine Prevention © Evommune, Inc. 1. US/EU5/JP eligible patients estimated. Sources: Clarivate “Migraine: Disease Landscape and Forecast” (2026), AHS guidelines for migraine prevention eligibility, Buse et al. (2024), Silberstein et al. (2015), Cohen et al. (2024), Coppola et al. (2025), Sakai et al. (2022). Patients Eligible for Preventative Therapy1 EVO756 – Defining the Next Wave of Preventatives Oral Dosing 1 Novel Dual Mechanism 2 First-Line Potential 3 30 M ~
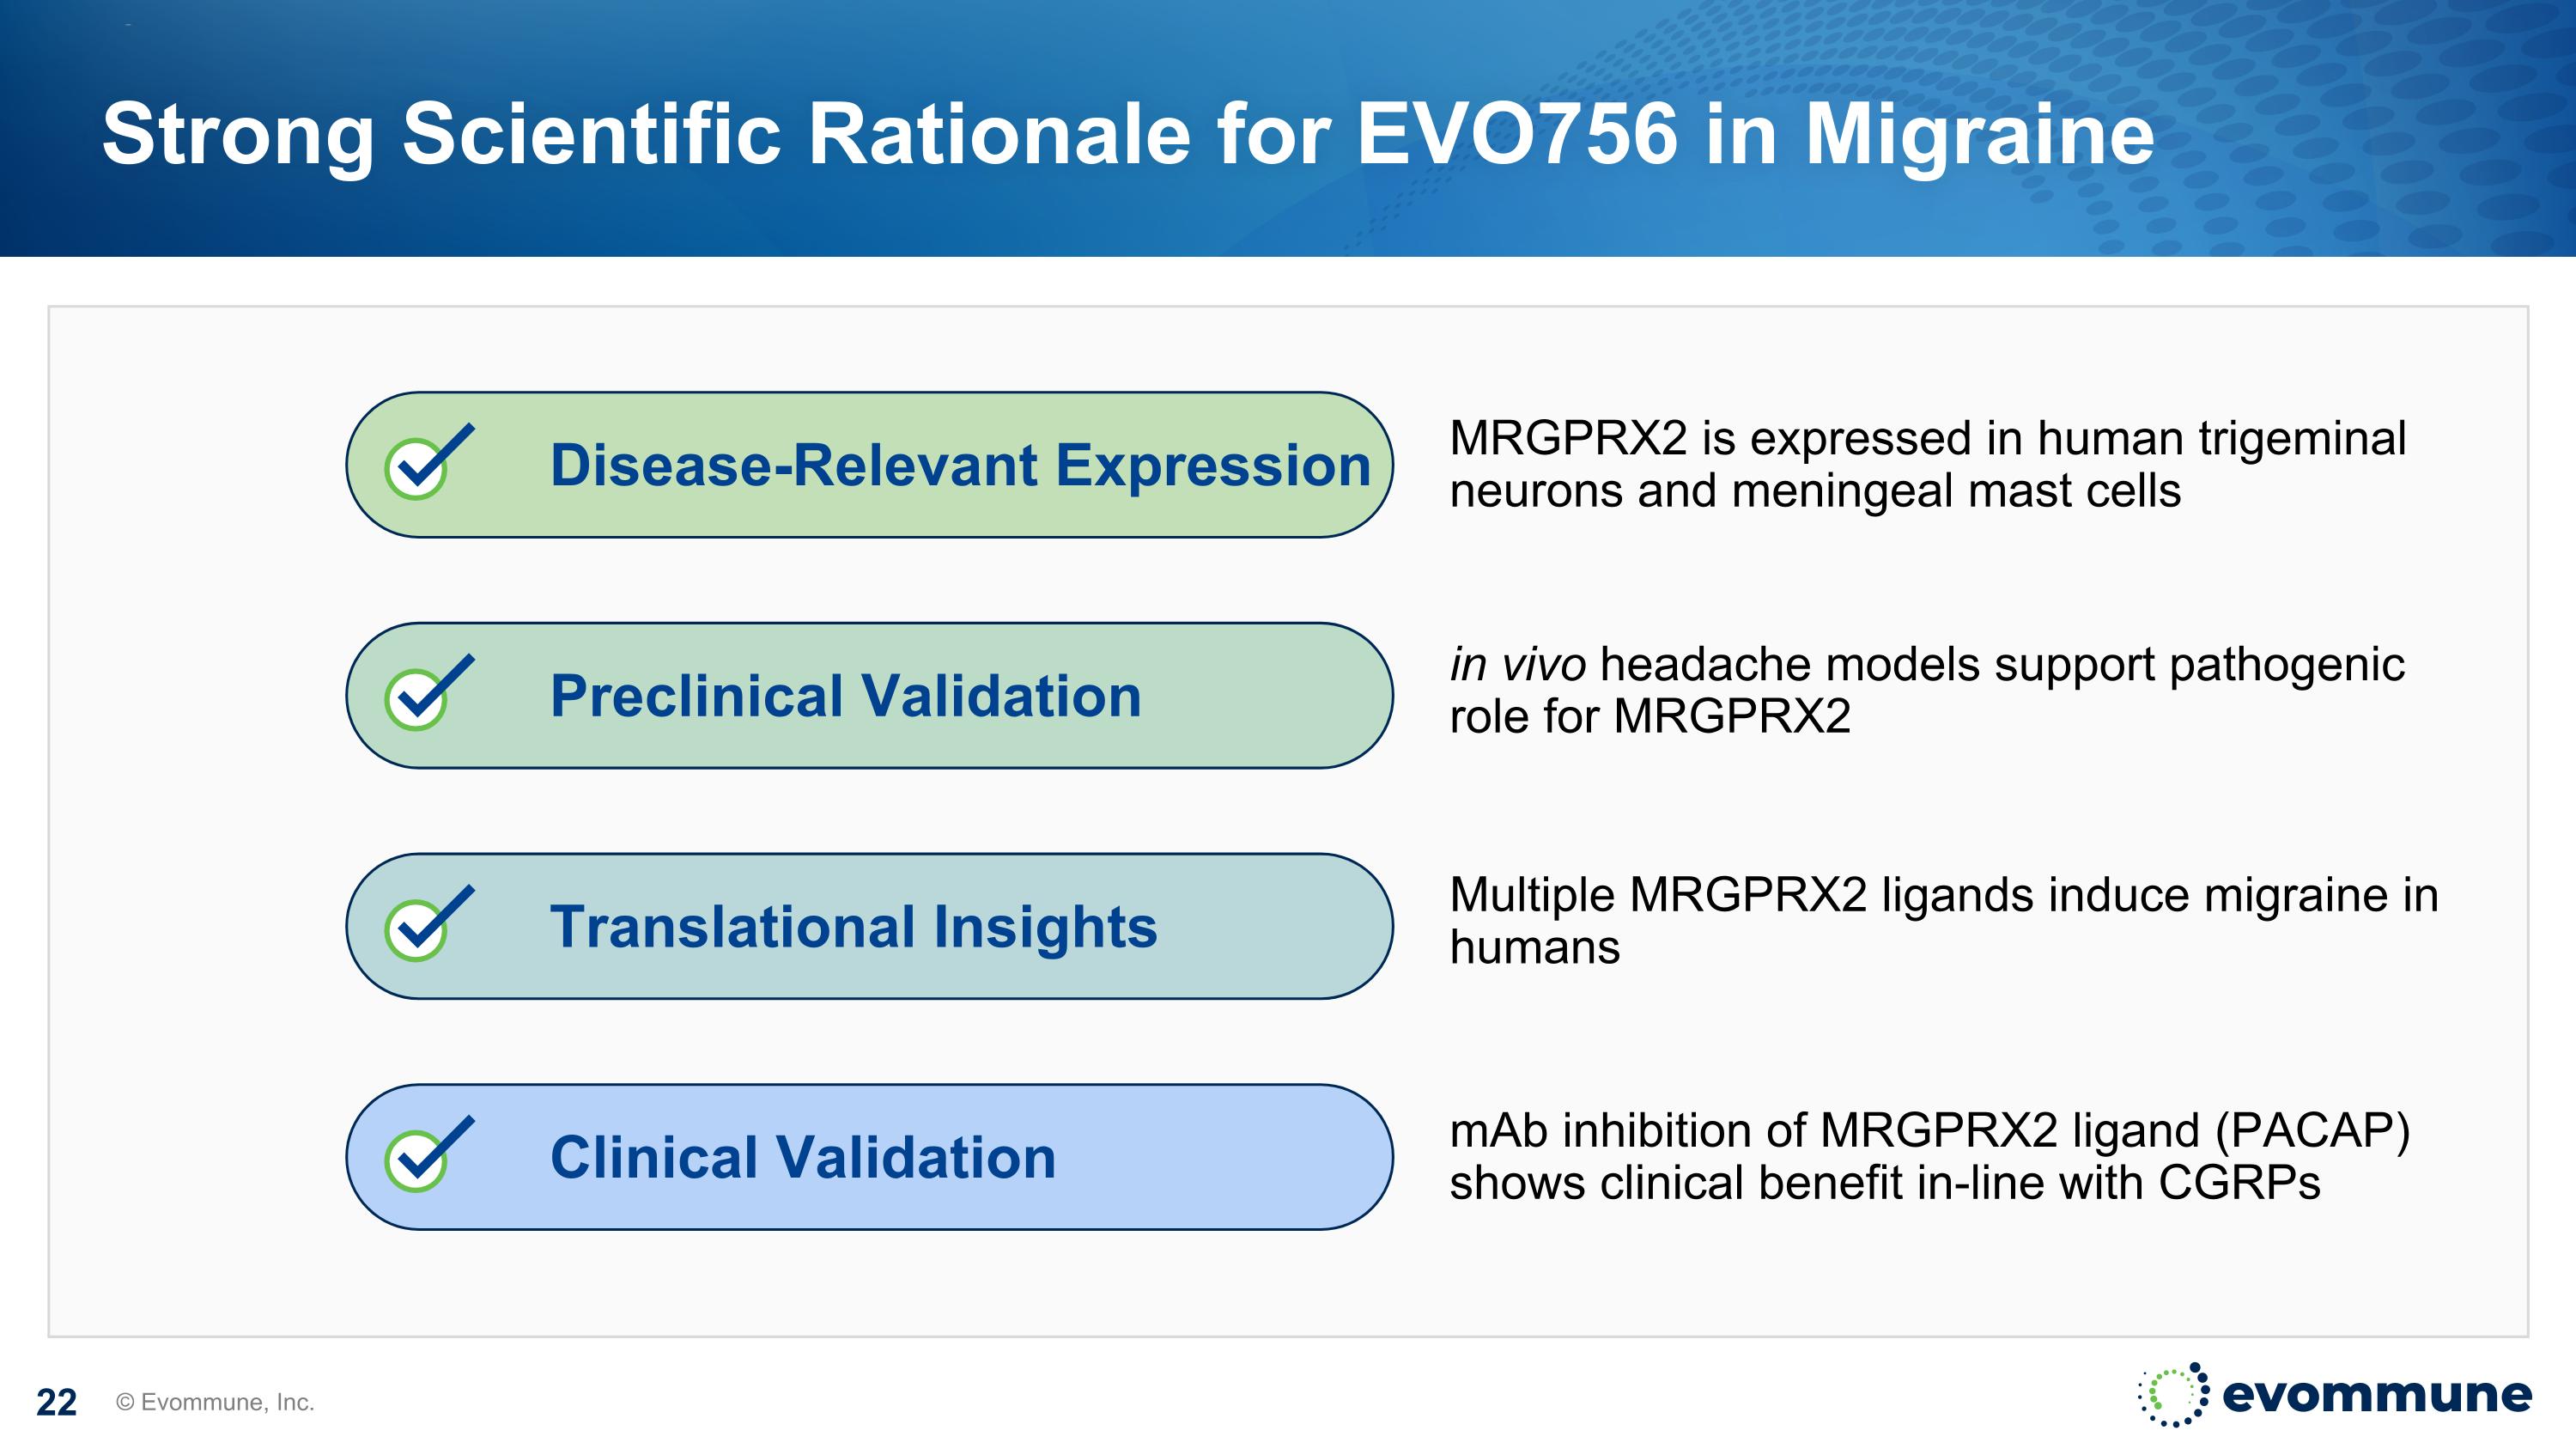
Strong Scientific Rationale for EVO756 in Migraine © Evommune, Inc. MRGPRX2 is expressed in human trigeminal neurons and meningeal mast cells Disease-Relevant Expression in vivo headache models support pathogenic role for MRGPRX2 Preclinical Validation Translational Insights Multiple MRGPRX2 ligands induce migraine in humans mAb inhibition of MRGPRX2 ligand (PACAP) shows clinical benefit in-line with CGRPs Clinical Validation
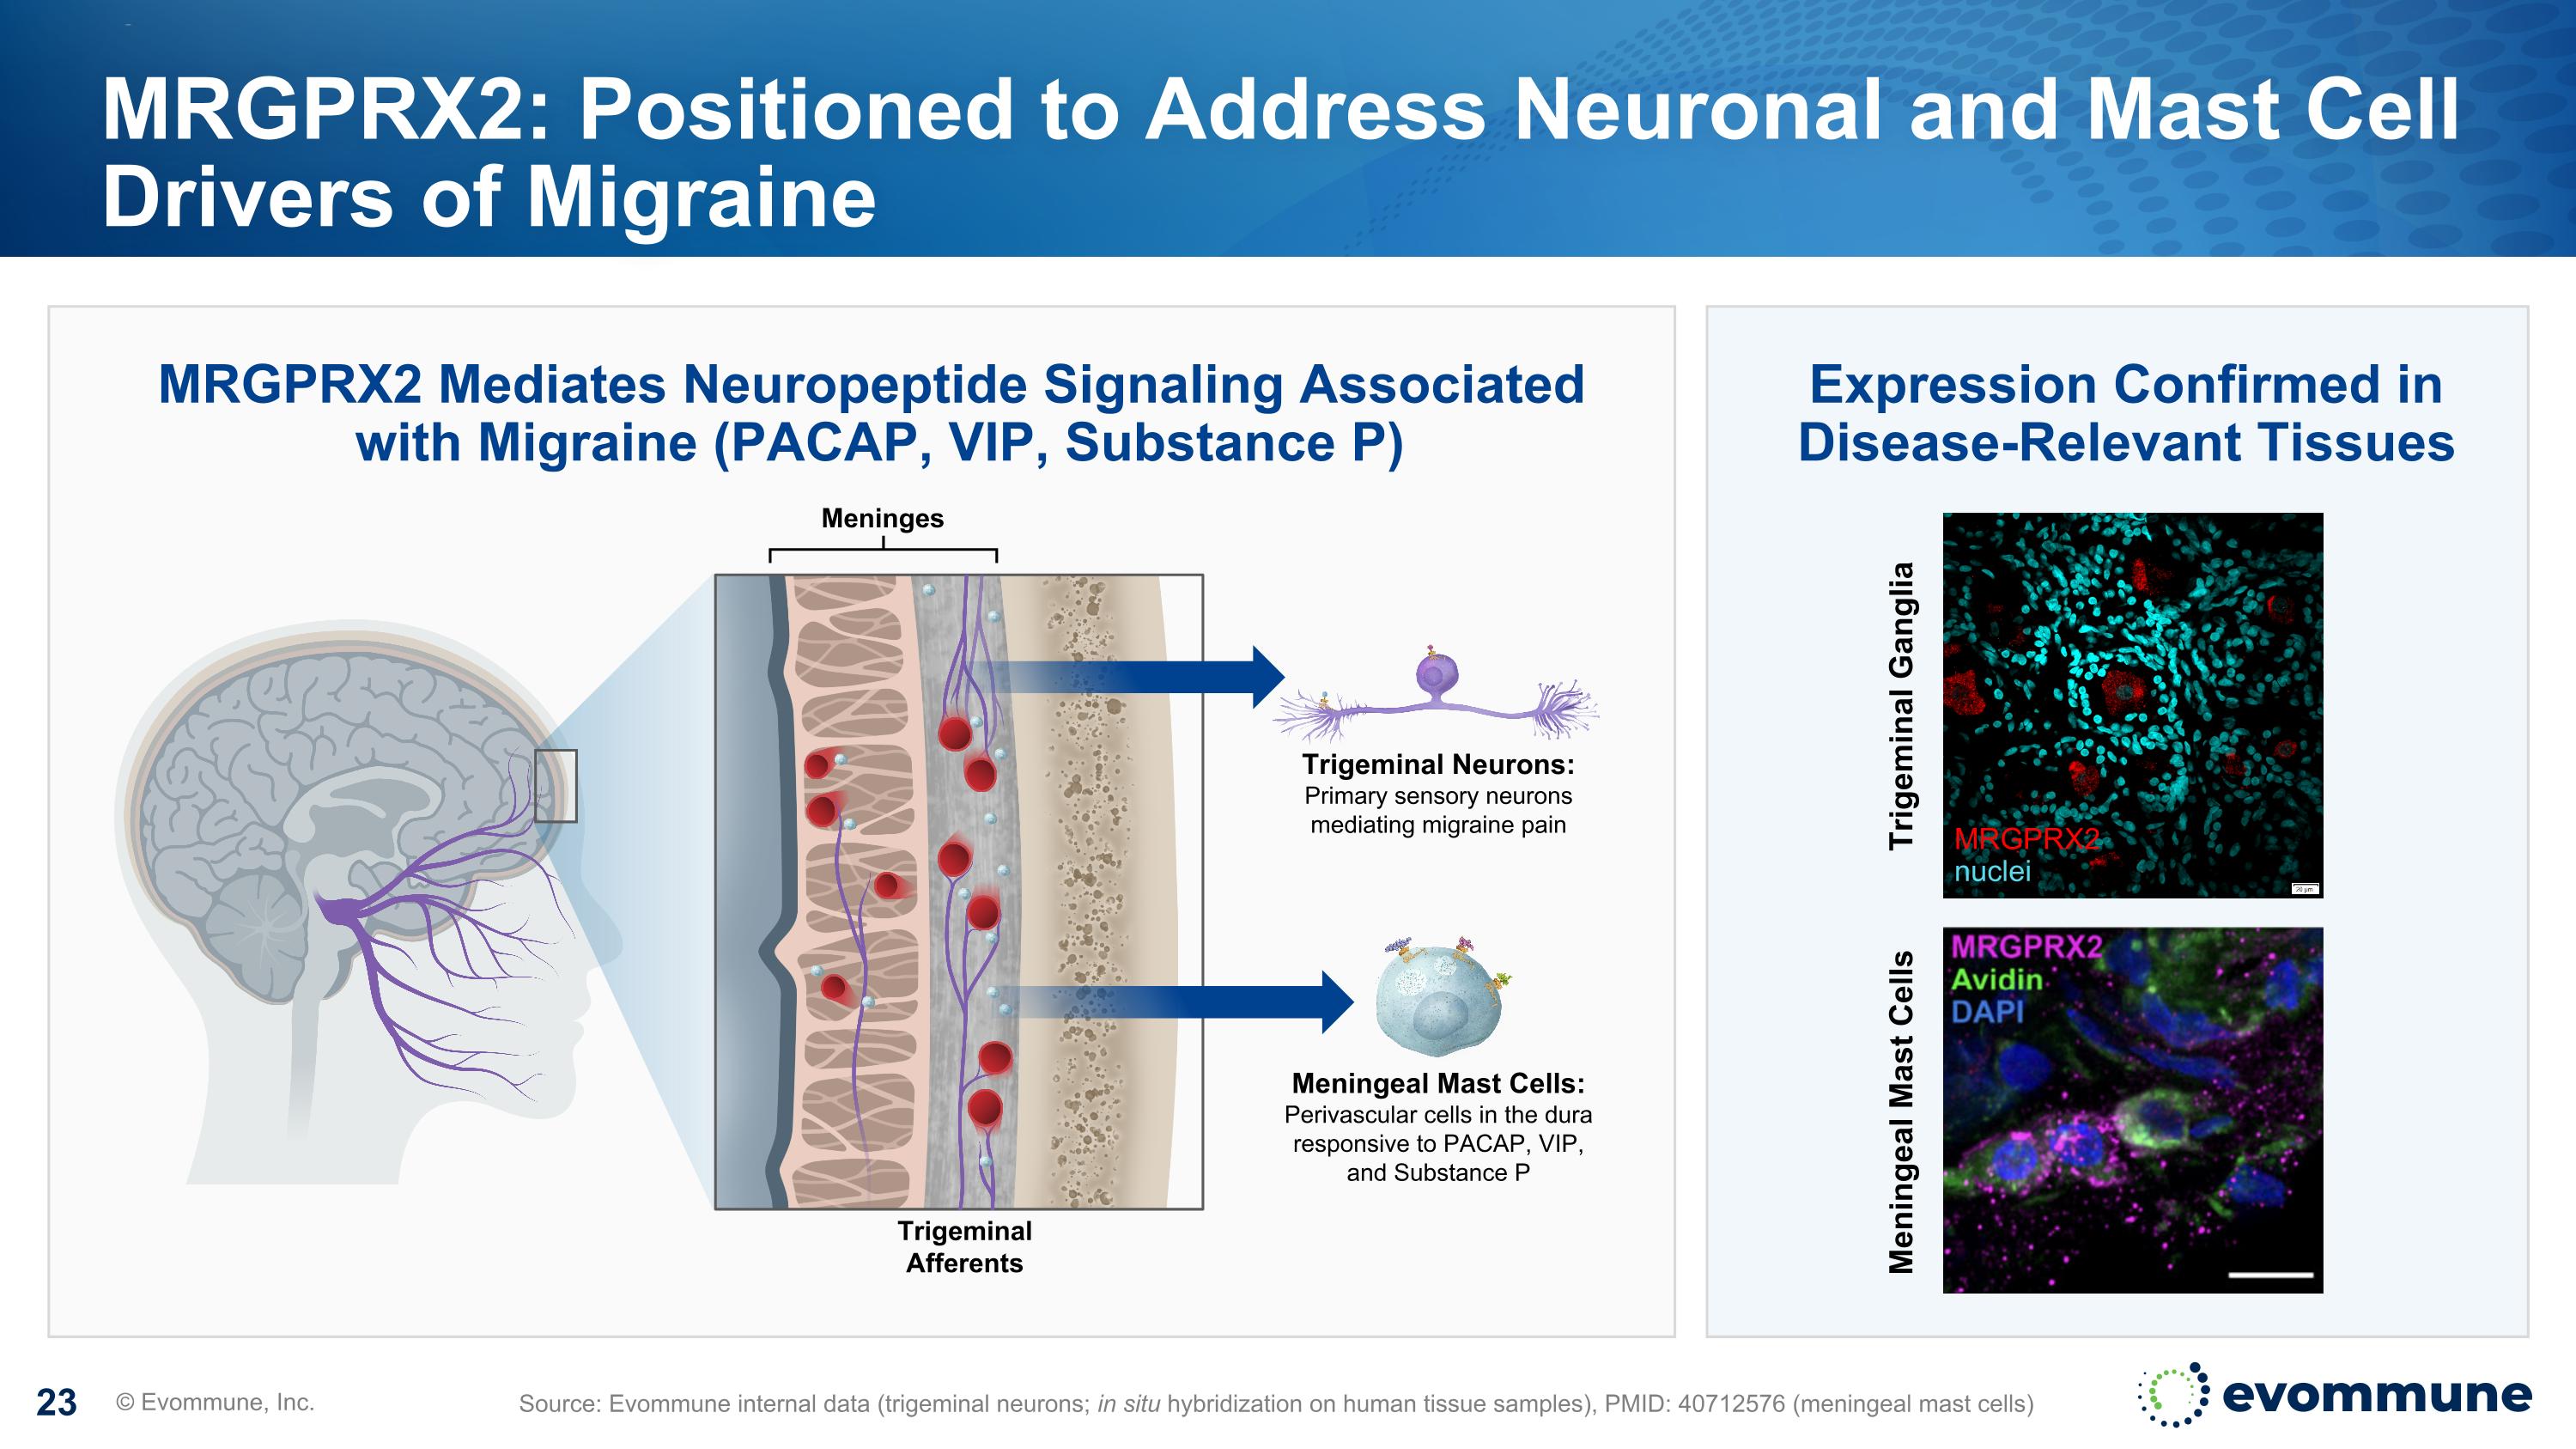
MRGPRX2: Positioned to Address Neuronal and Mast Cell Drivers of Migraine © Evommune, Inc. Source: Evommune internal data (trigeminal neurons; in situ hybridization on human tissue samples), PMID: 40712576 (meningeal mast cells) Expression Confirmed in Disease-Relevant Tissues MRGPRX2 nuclei Trigeminal Ganglia Meningeal Mast Cells MRGPRX2 Mediates Neuropeptide Signaling Associated with Migraine (PACAP, VIP, Substance P) Meningeal Mast Cells: Perivascular cells in the dura responsive to PACAP, VIP, and Substance P Trigeminal Neurons: Primary sensory neurons mediating migraine pain Meninges Trigeminal Afferents
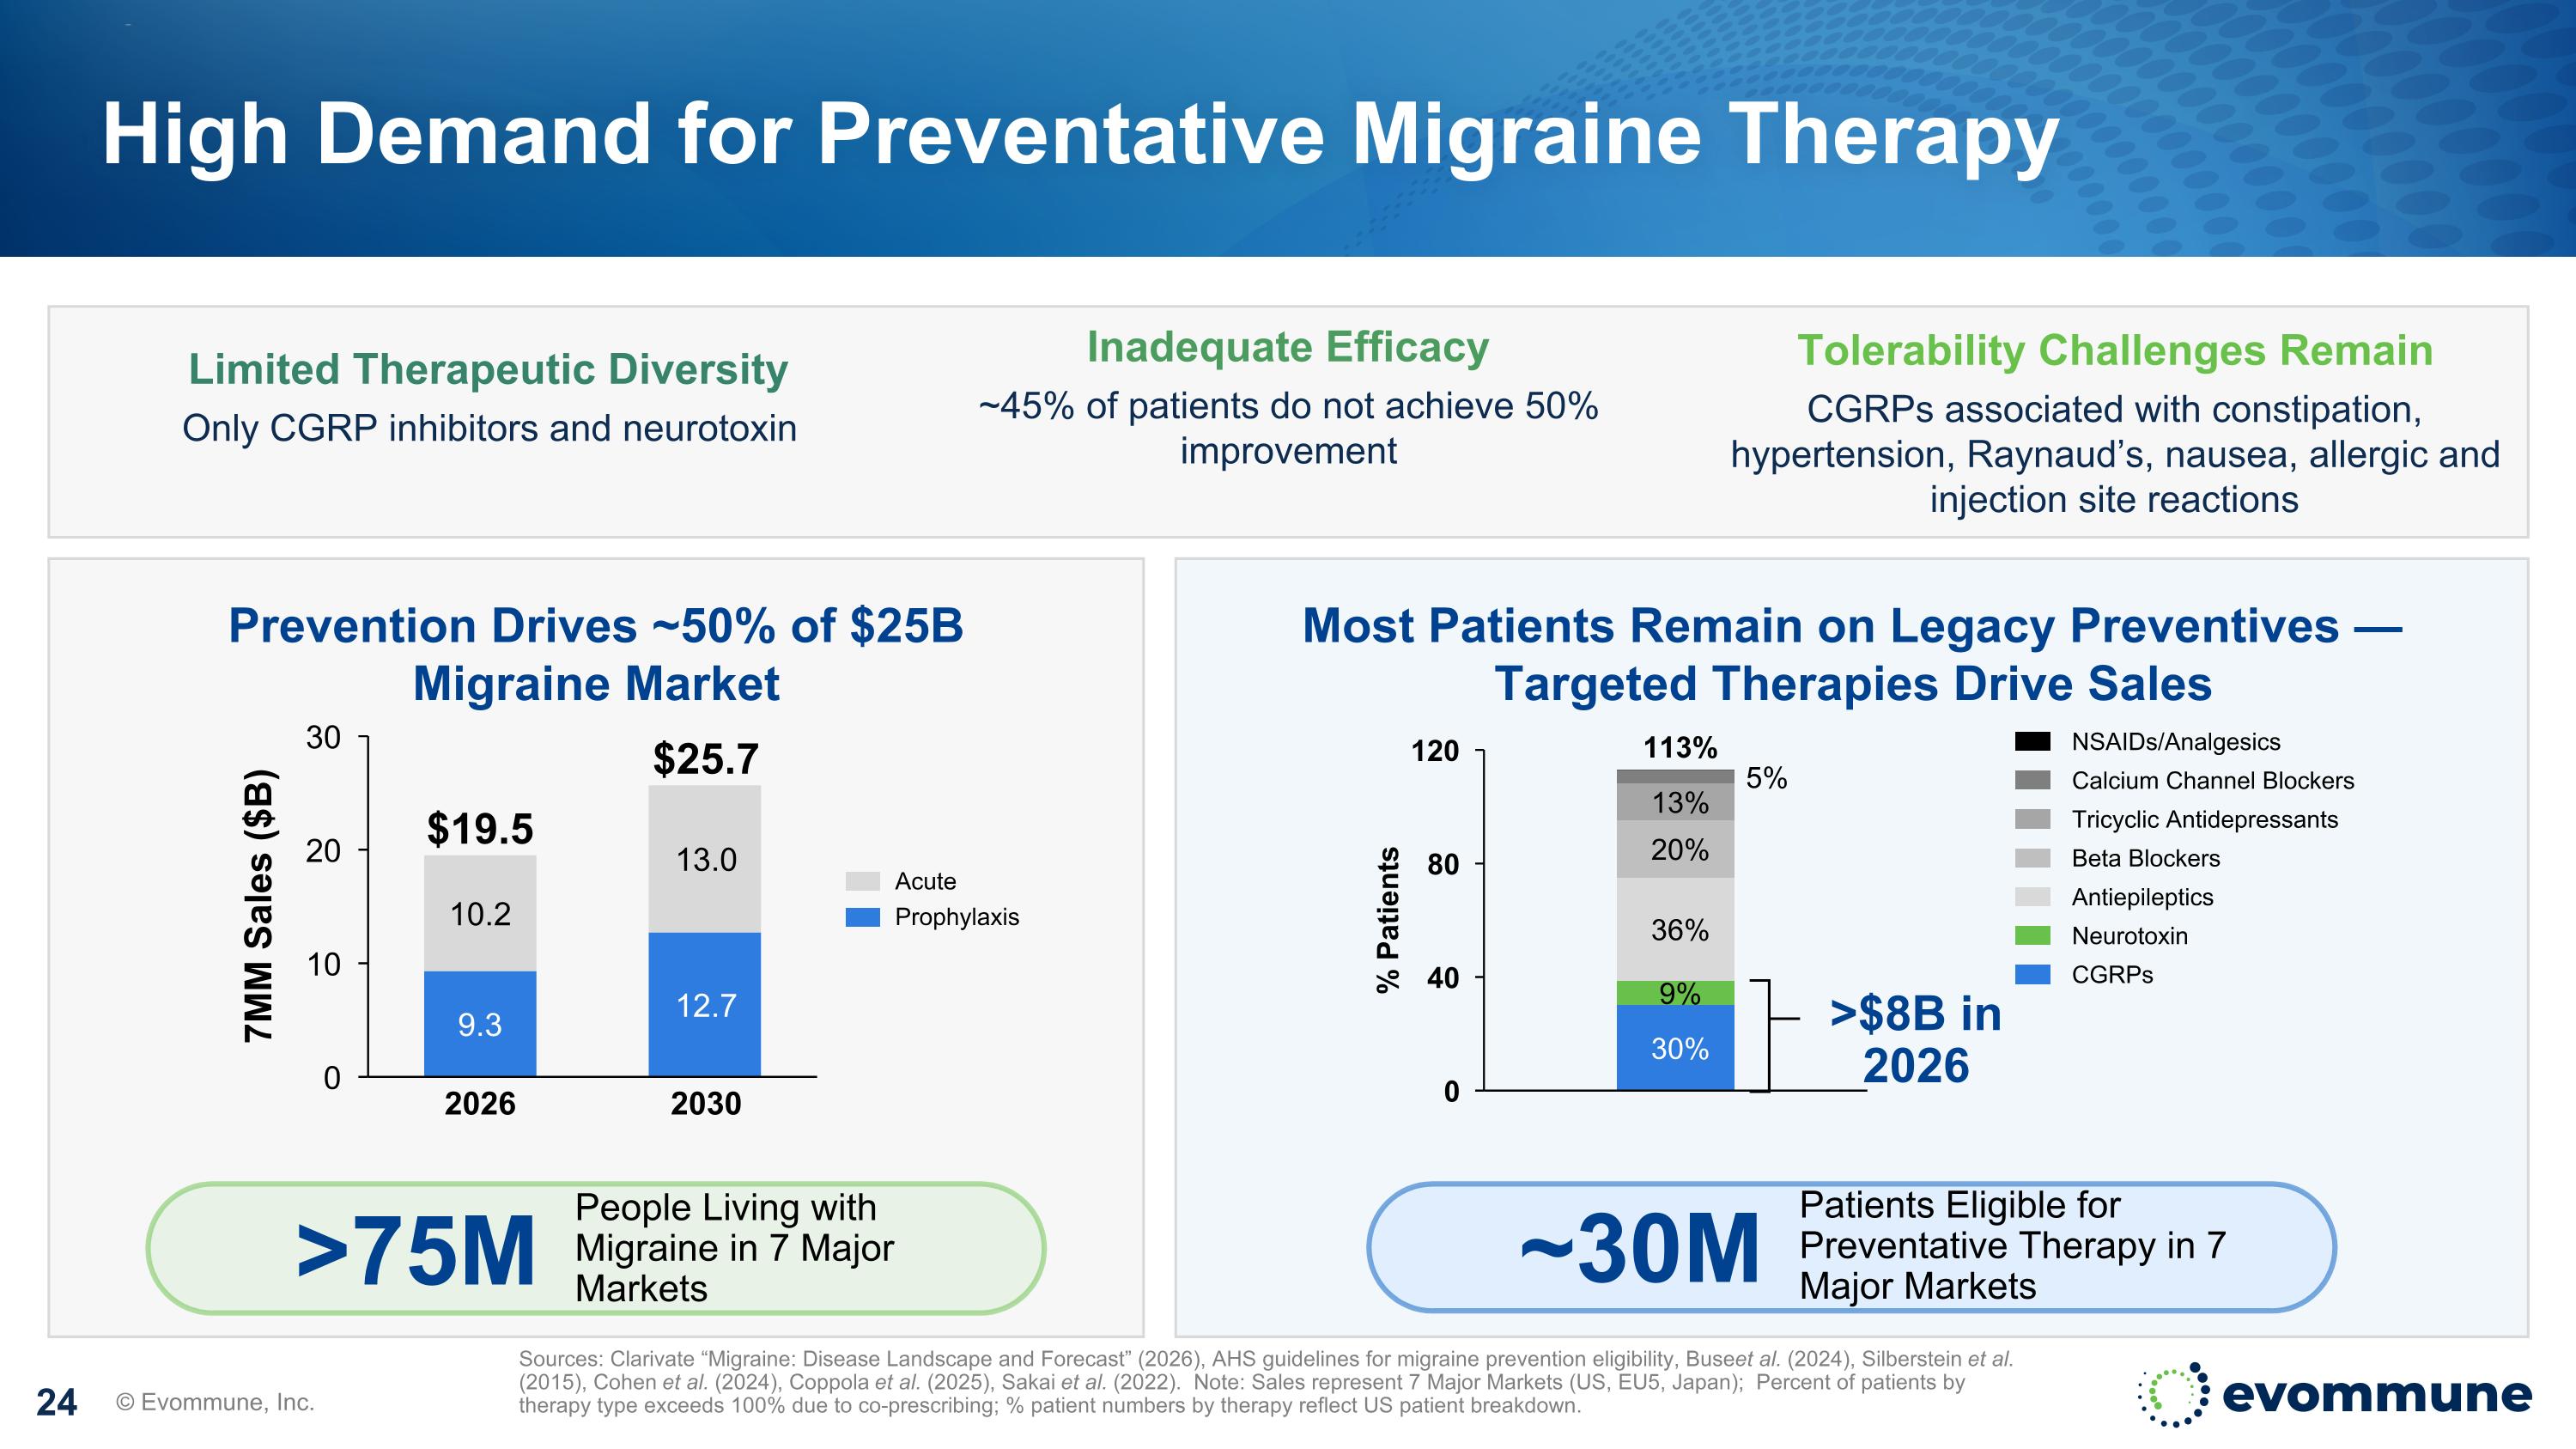
High Demand for Preventative Migraine Therapy © Evommune, Inc. Sources: Clarivate “Migraine: Disease Landscape and Forecast” (2026), AHS guidelines for migraine prevention eligibility, Buse et al. (2024), Silberstein et al. (2015), Cohen et al. (2024), Coppola et al. (2025), Sakai et al. (2022). Note: Sales represent 7 Major Markets (US, EU5, Japan); Percent of patients by therapy type exceeds 100% due to co-prescribing; % patient numbers by therapy reflect US patient breakdown. Prevention Drives ~50% of $25B Migraine Market 0 10 20 30 7MM Sales ($B) 10.2 9.3 2026 13.0 12.7 2030 $19.5 $25.7 Acute Prophylaxis >75M People Living with Migraine in 7 Major Markets ~30M Patients Eligible for Preventative Therapy in 7 Major Markets Most Patients Remain on Legacy Preventives — Targeted Therapies Drive Sales % Patients 5% 13% 20% 36% 9% 30% 113% >$8B in 2026 NSAIDs/Analgesics Calcium Channel Blockers Tricyclic Antidepressants Beta Blockers Antiepileptics Neurotoxin CGRPs Limited Therapeutic Diversity Only CGRP inhibitors and neurotoxin Inadequate Efficacy ~45% of patients do not achieve 50% improvement Tolerability Challenges Remain CGRPs associated with constipation, hypertension, Raynaud’s, nausea, allergic and injection site reactions
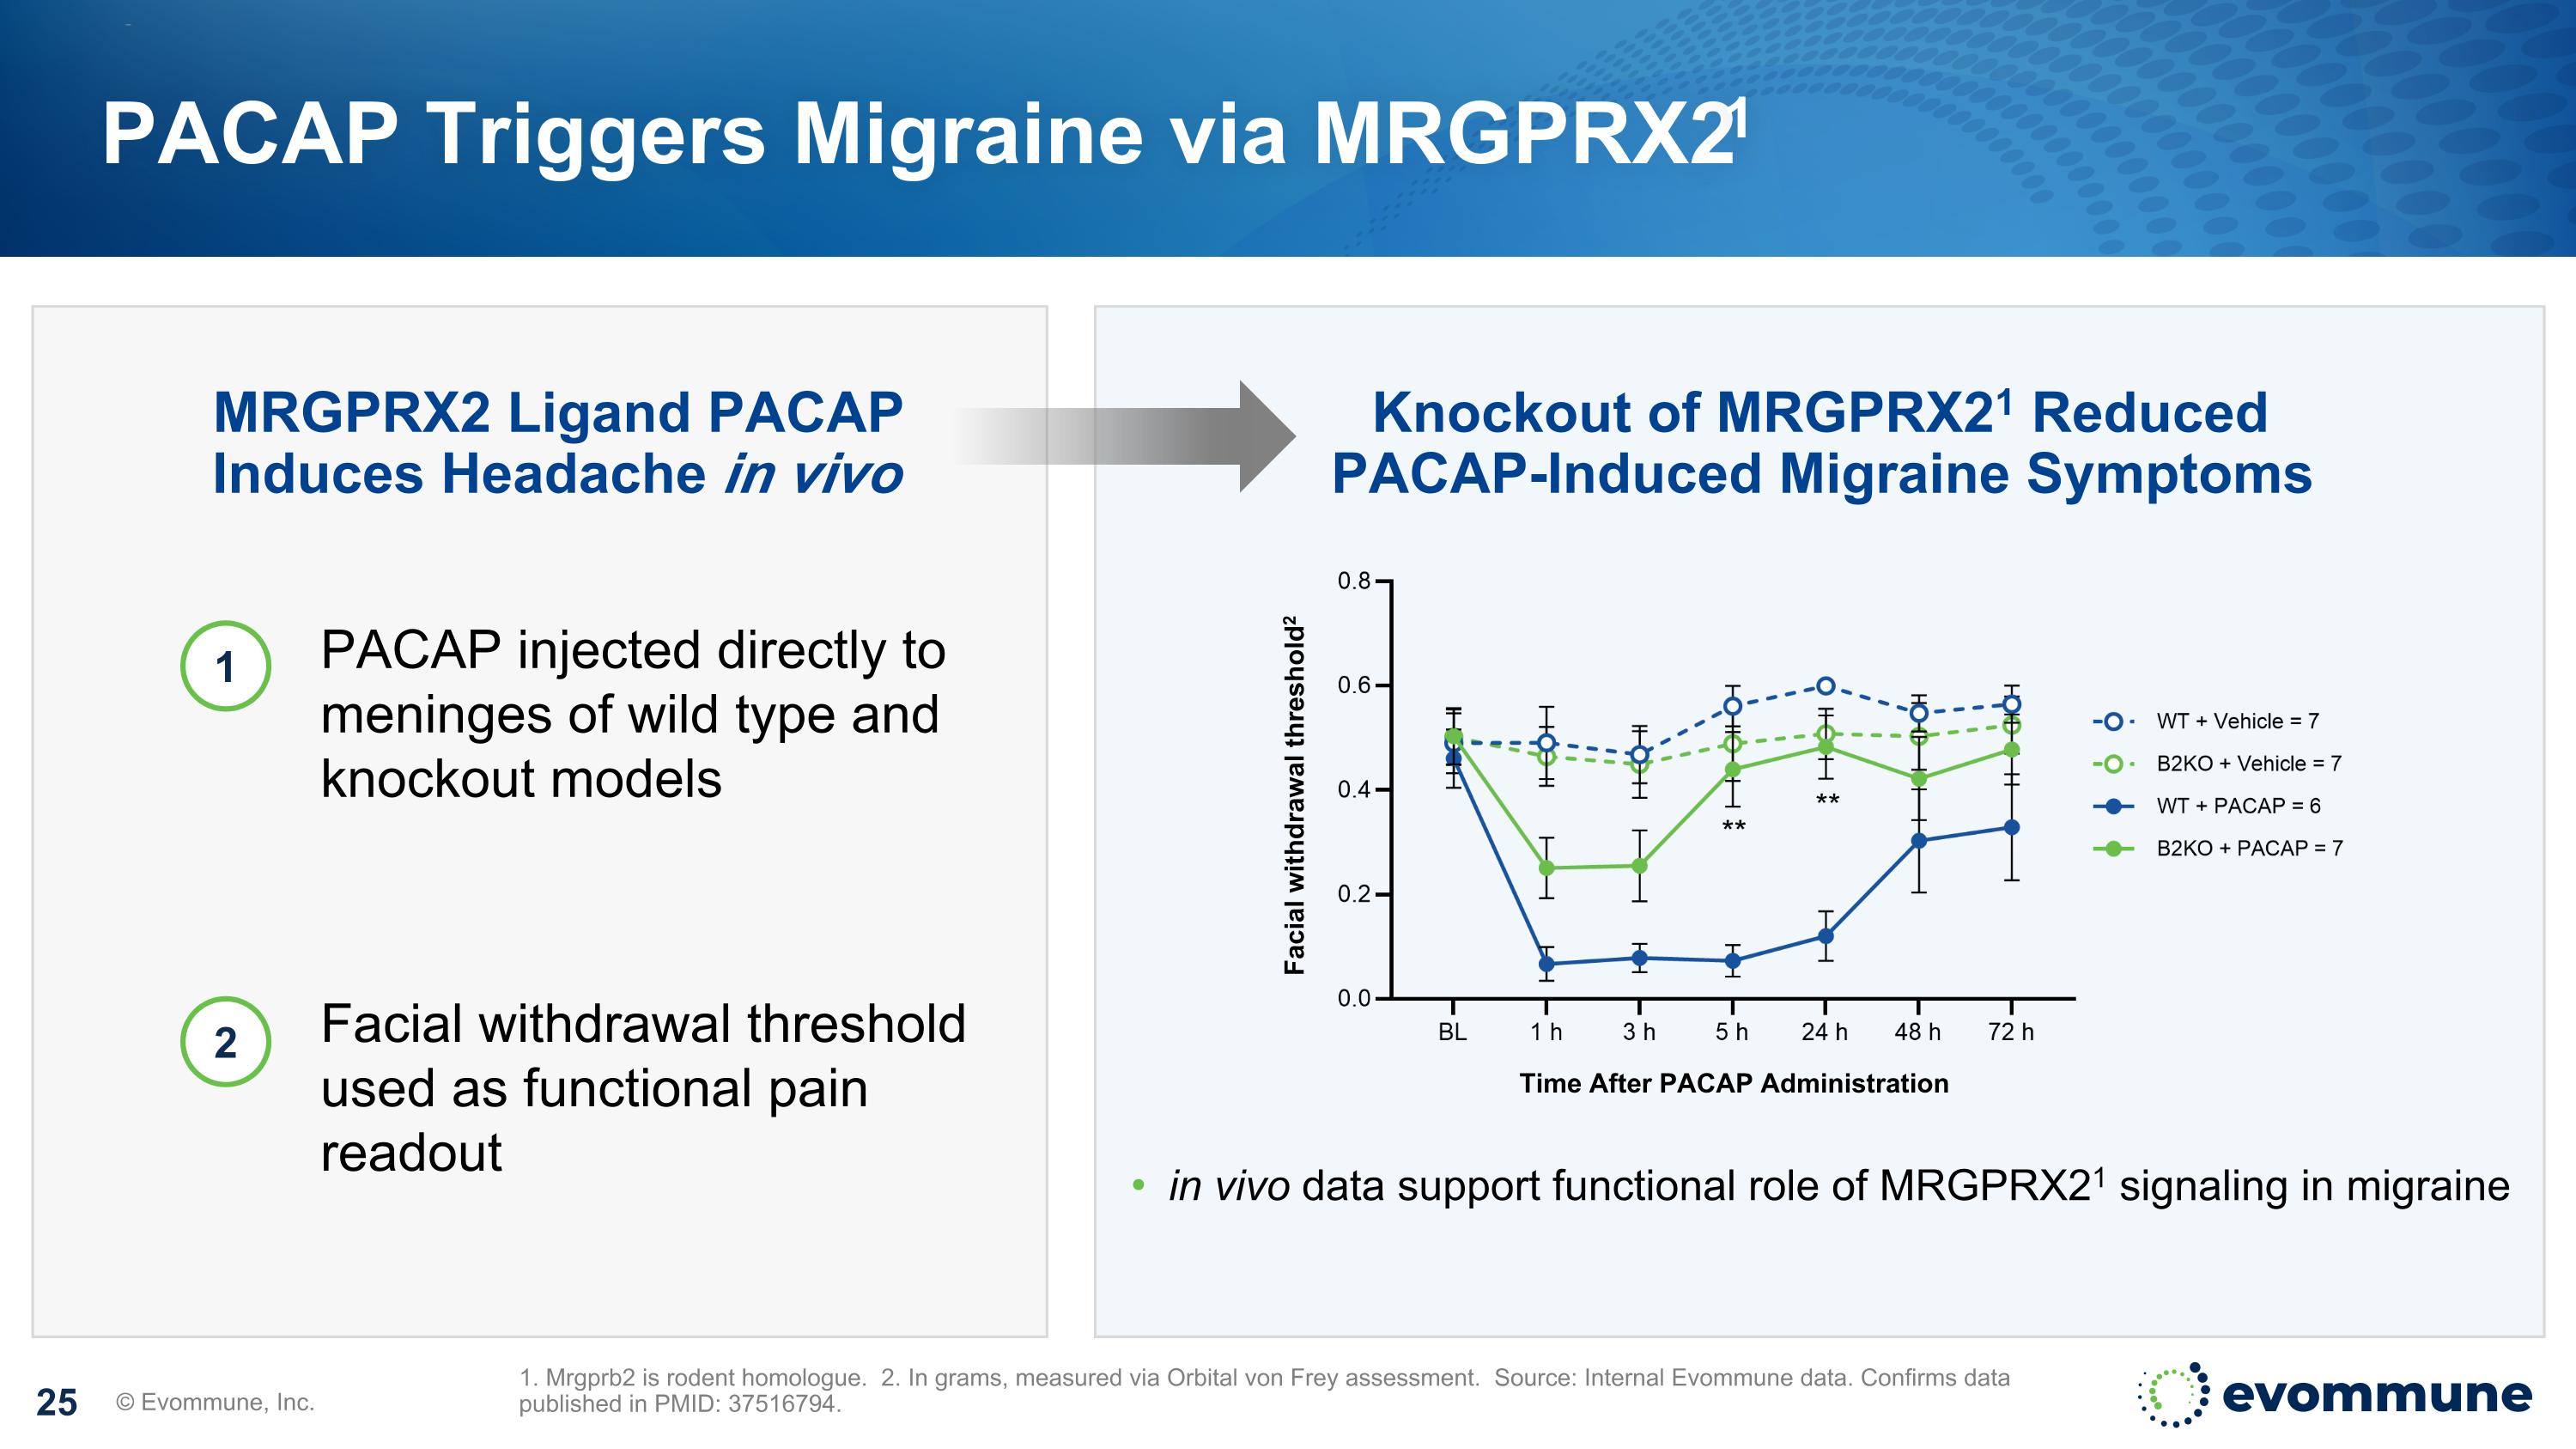
PACAP Triggers Migraine via MRGPRX21 © Evommune, Inc. 1. Mrgprb2 is rodent homologue. 2. In grams, measured via Orbital von Frey assessment. Source: Internal Evommune data. Confirms data published in PMID: 37516794. Facial withdrawal threshold2 in vivo data support functional role of MRGPRX21 signaling in migraine Time After PACAP Administration 1 PACAP injected directly to meninges of wild type and knockout models Facial withdrawal threshold used as functional pain readout Knockout of MRGPRX21 Reduced PACAP-Induced Migraine Symptoms MRGPRX2 Ligand PACAP Induces Headache in vivo 2
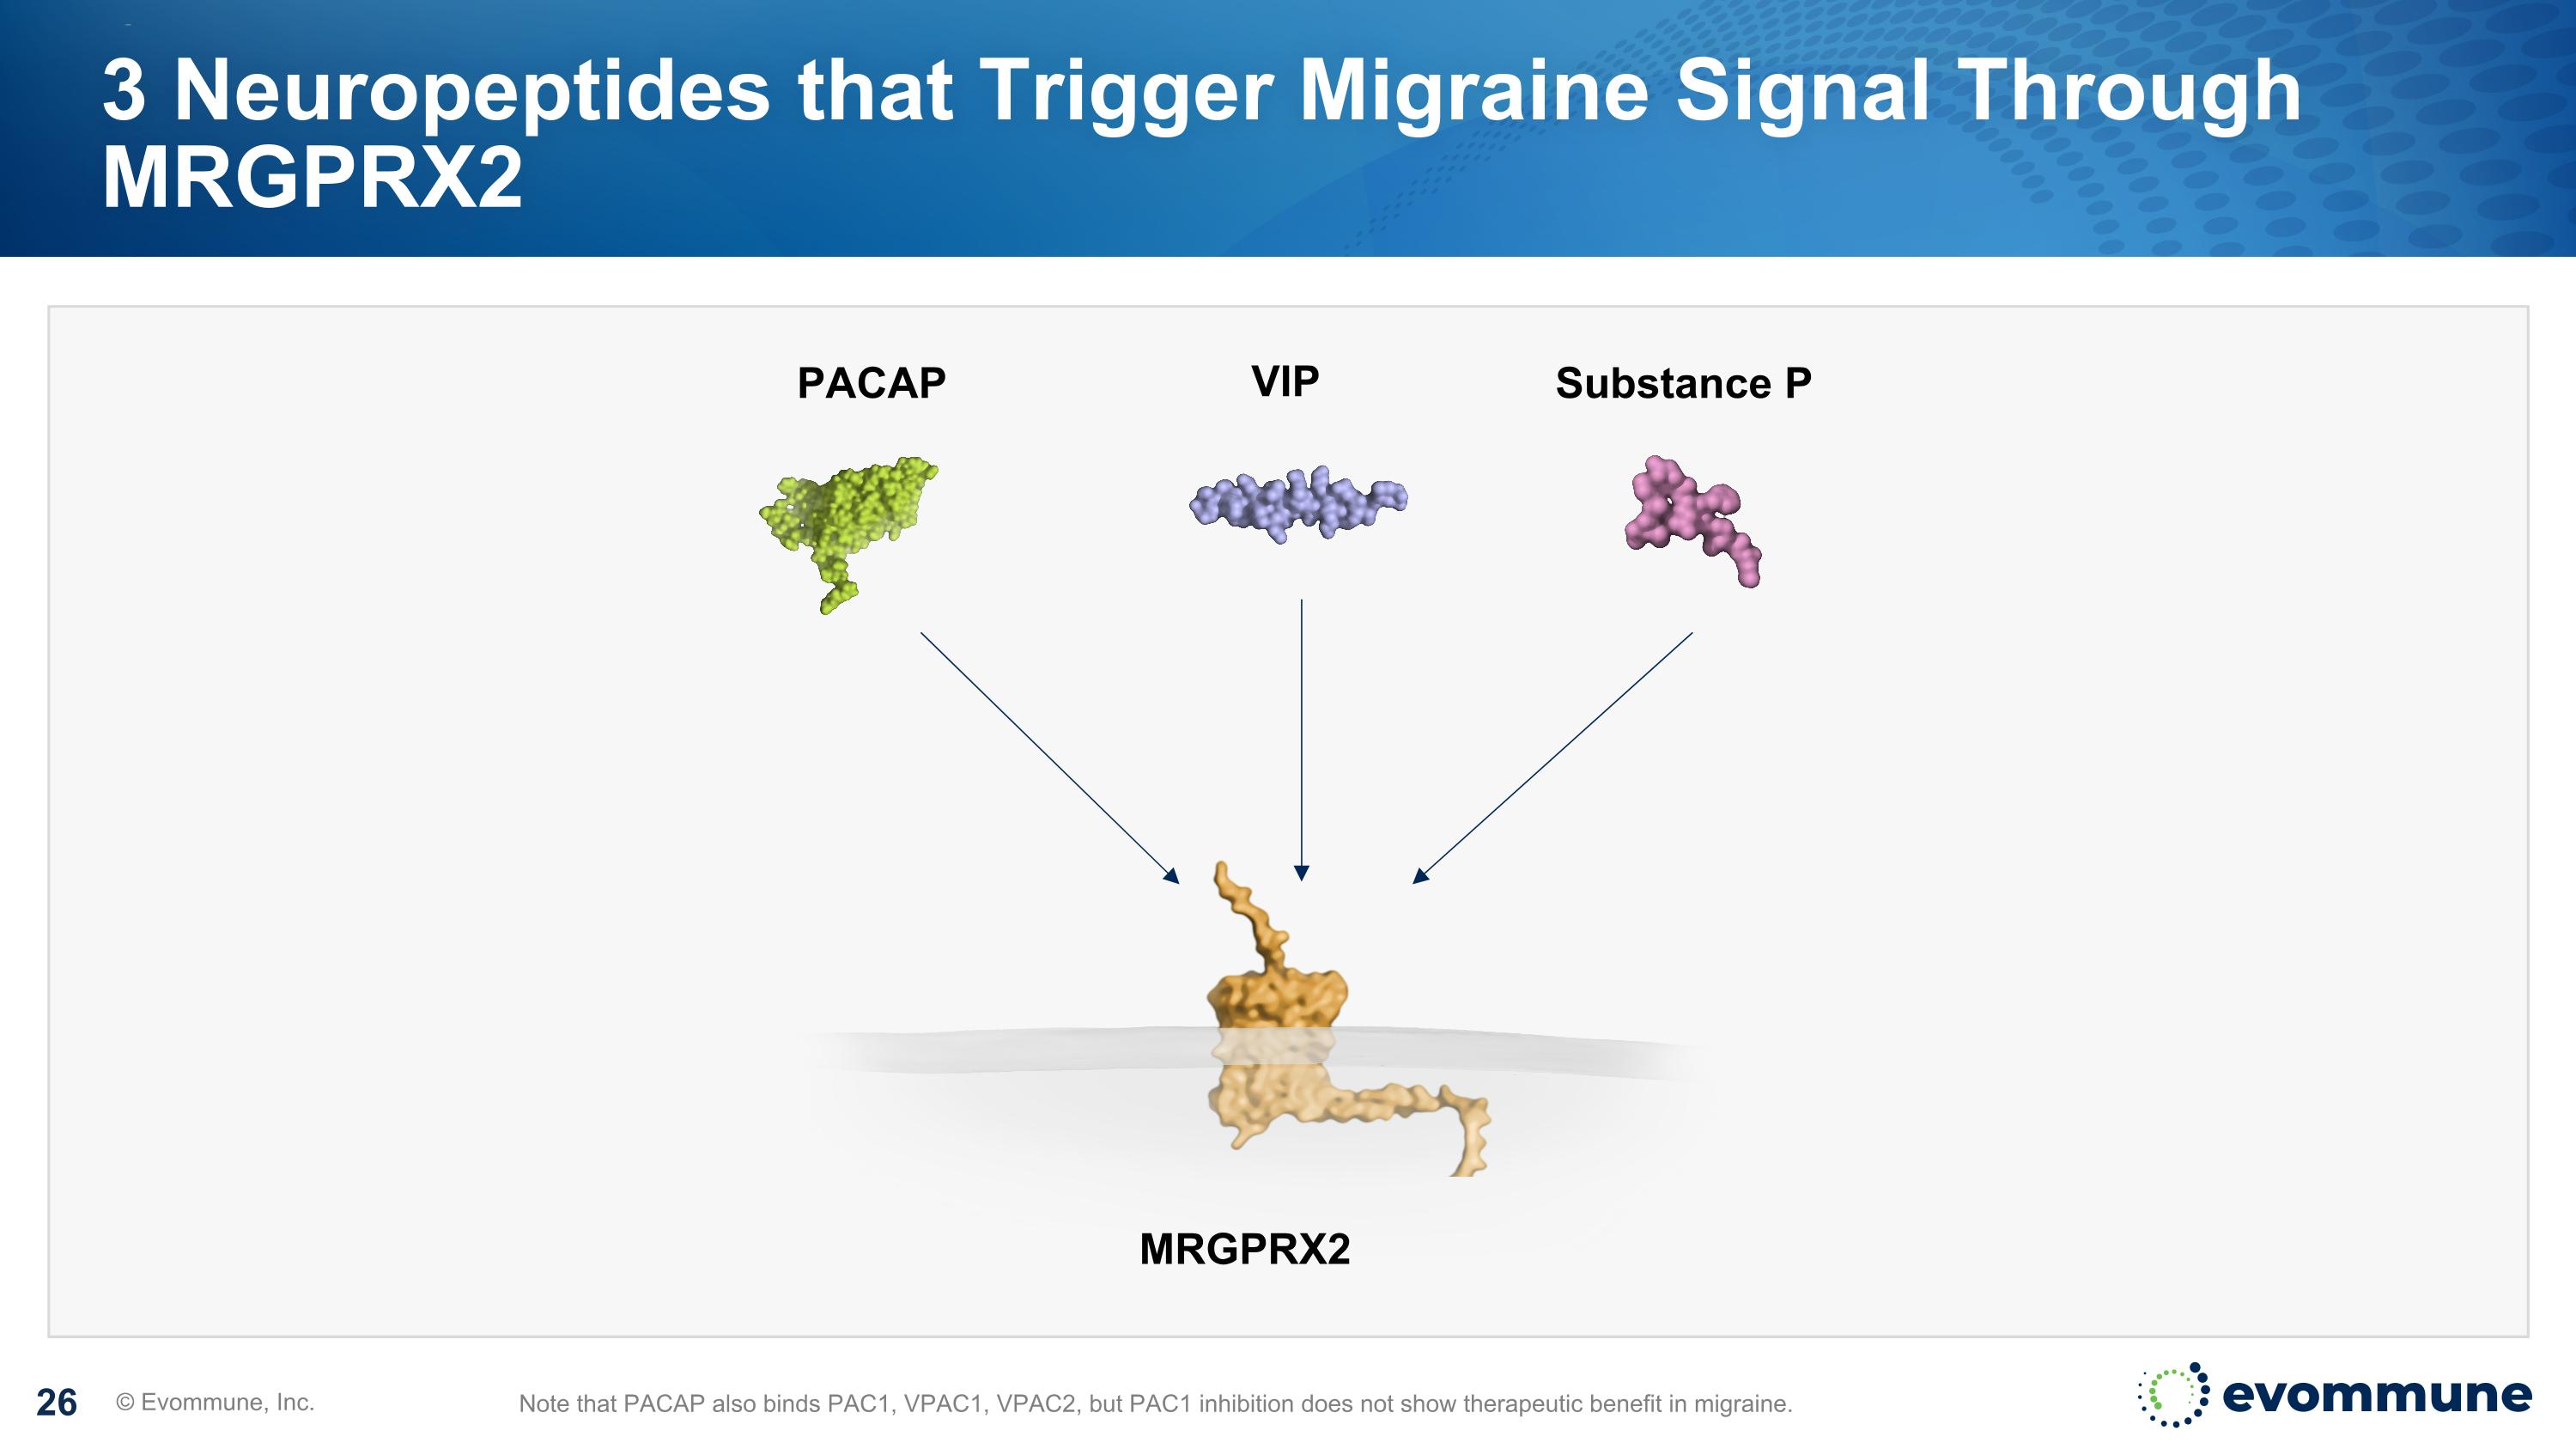
3 Neuropeptides that Trigger Migraine Signal Through MRGPRX2 © Evommune, Inc. Note that PACAP also binds PAC1, VPAC1, VPAC2, but PAC1 inhibition does not show therapeutic benefit in migraine. PACAP VIP Substance P MRGPRX2
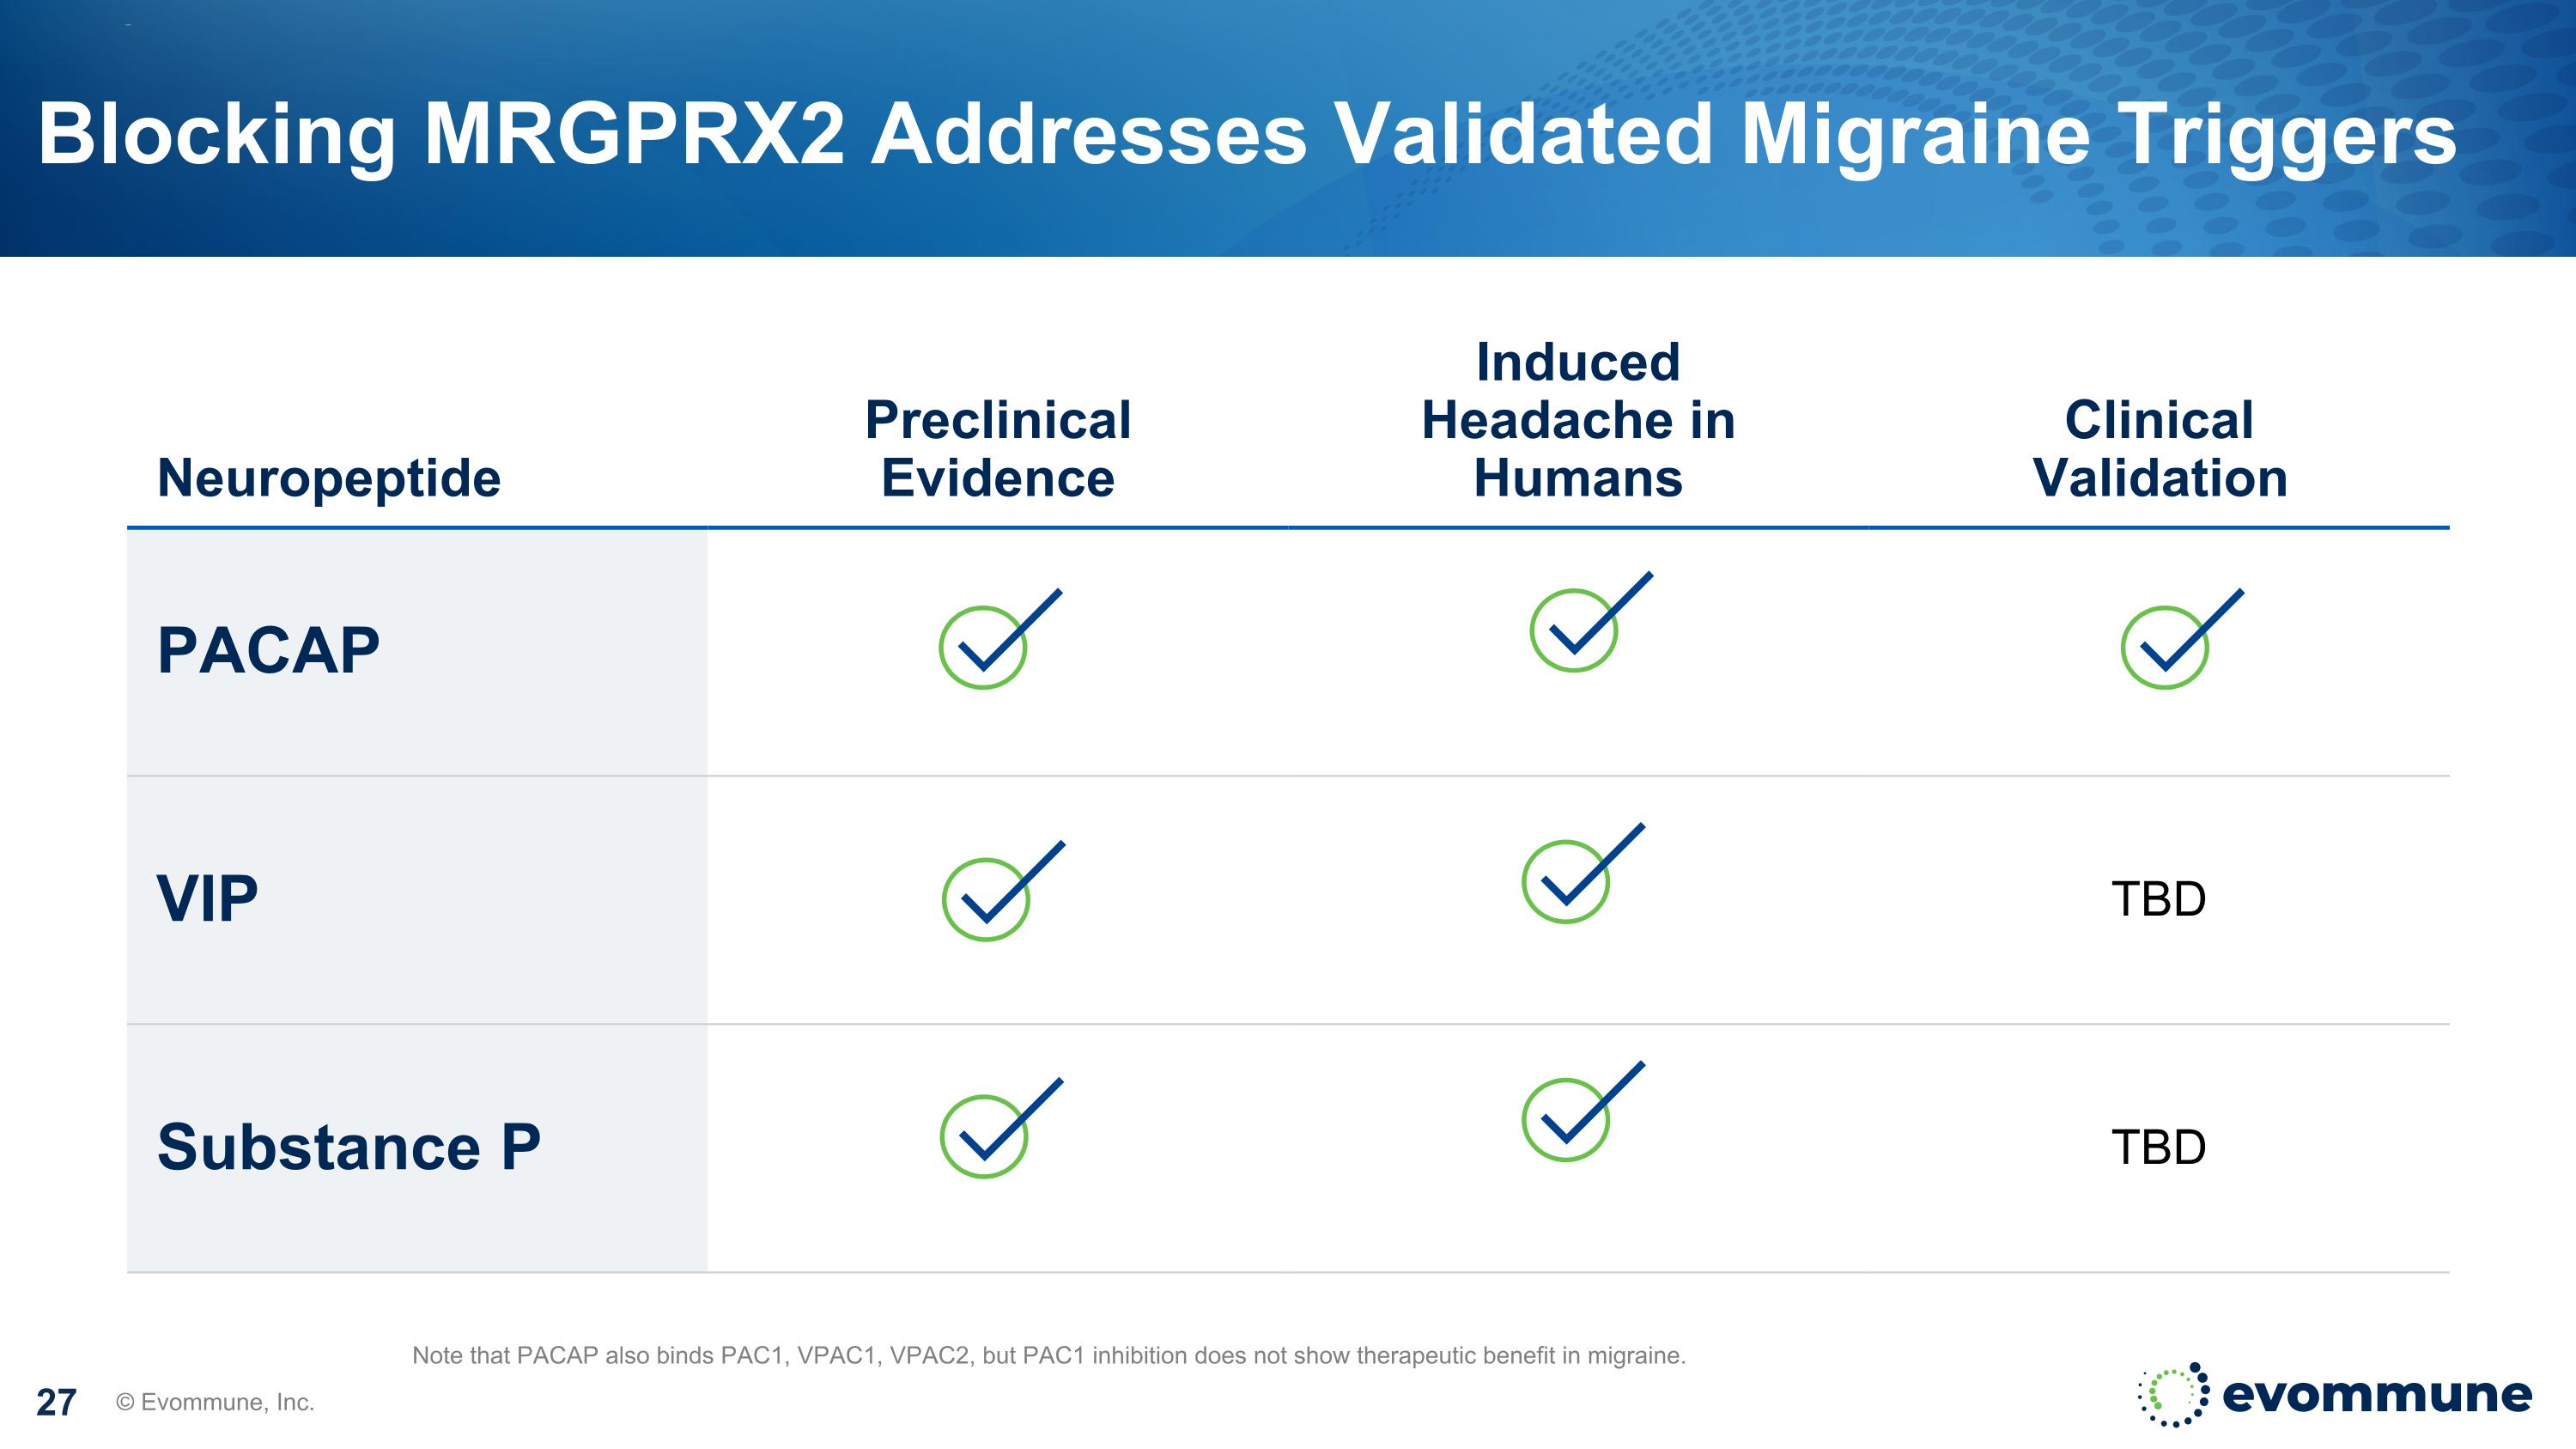
Neuropeptide Preclinical Evidence Induced Headache in Humans Clinical Validation PACAP VIP TBD Substance P TBD Blocking MRGPRX2 Addresses Validated Migraine Triggers © Evommune, Inc. Note that PACAP also binds PAC1, VPAC1, VPAC2, but PAC1 inhibition does not show therapeutic benefit in migraine.
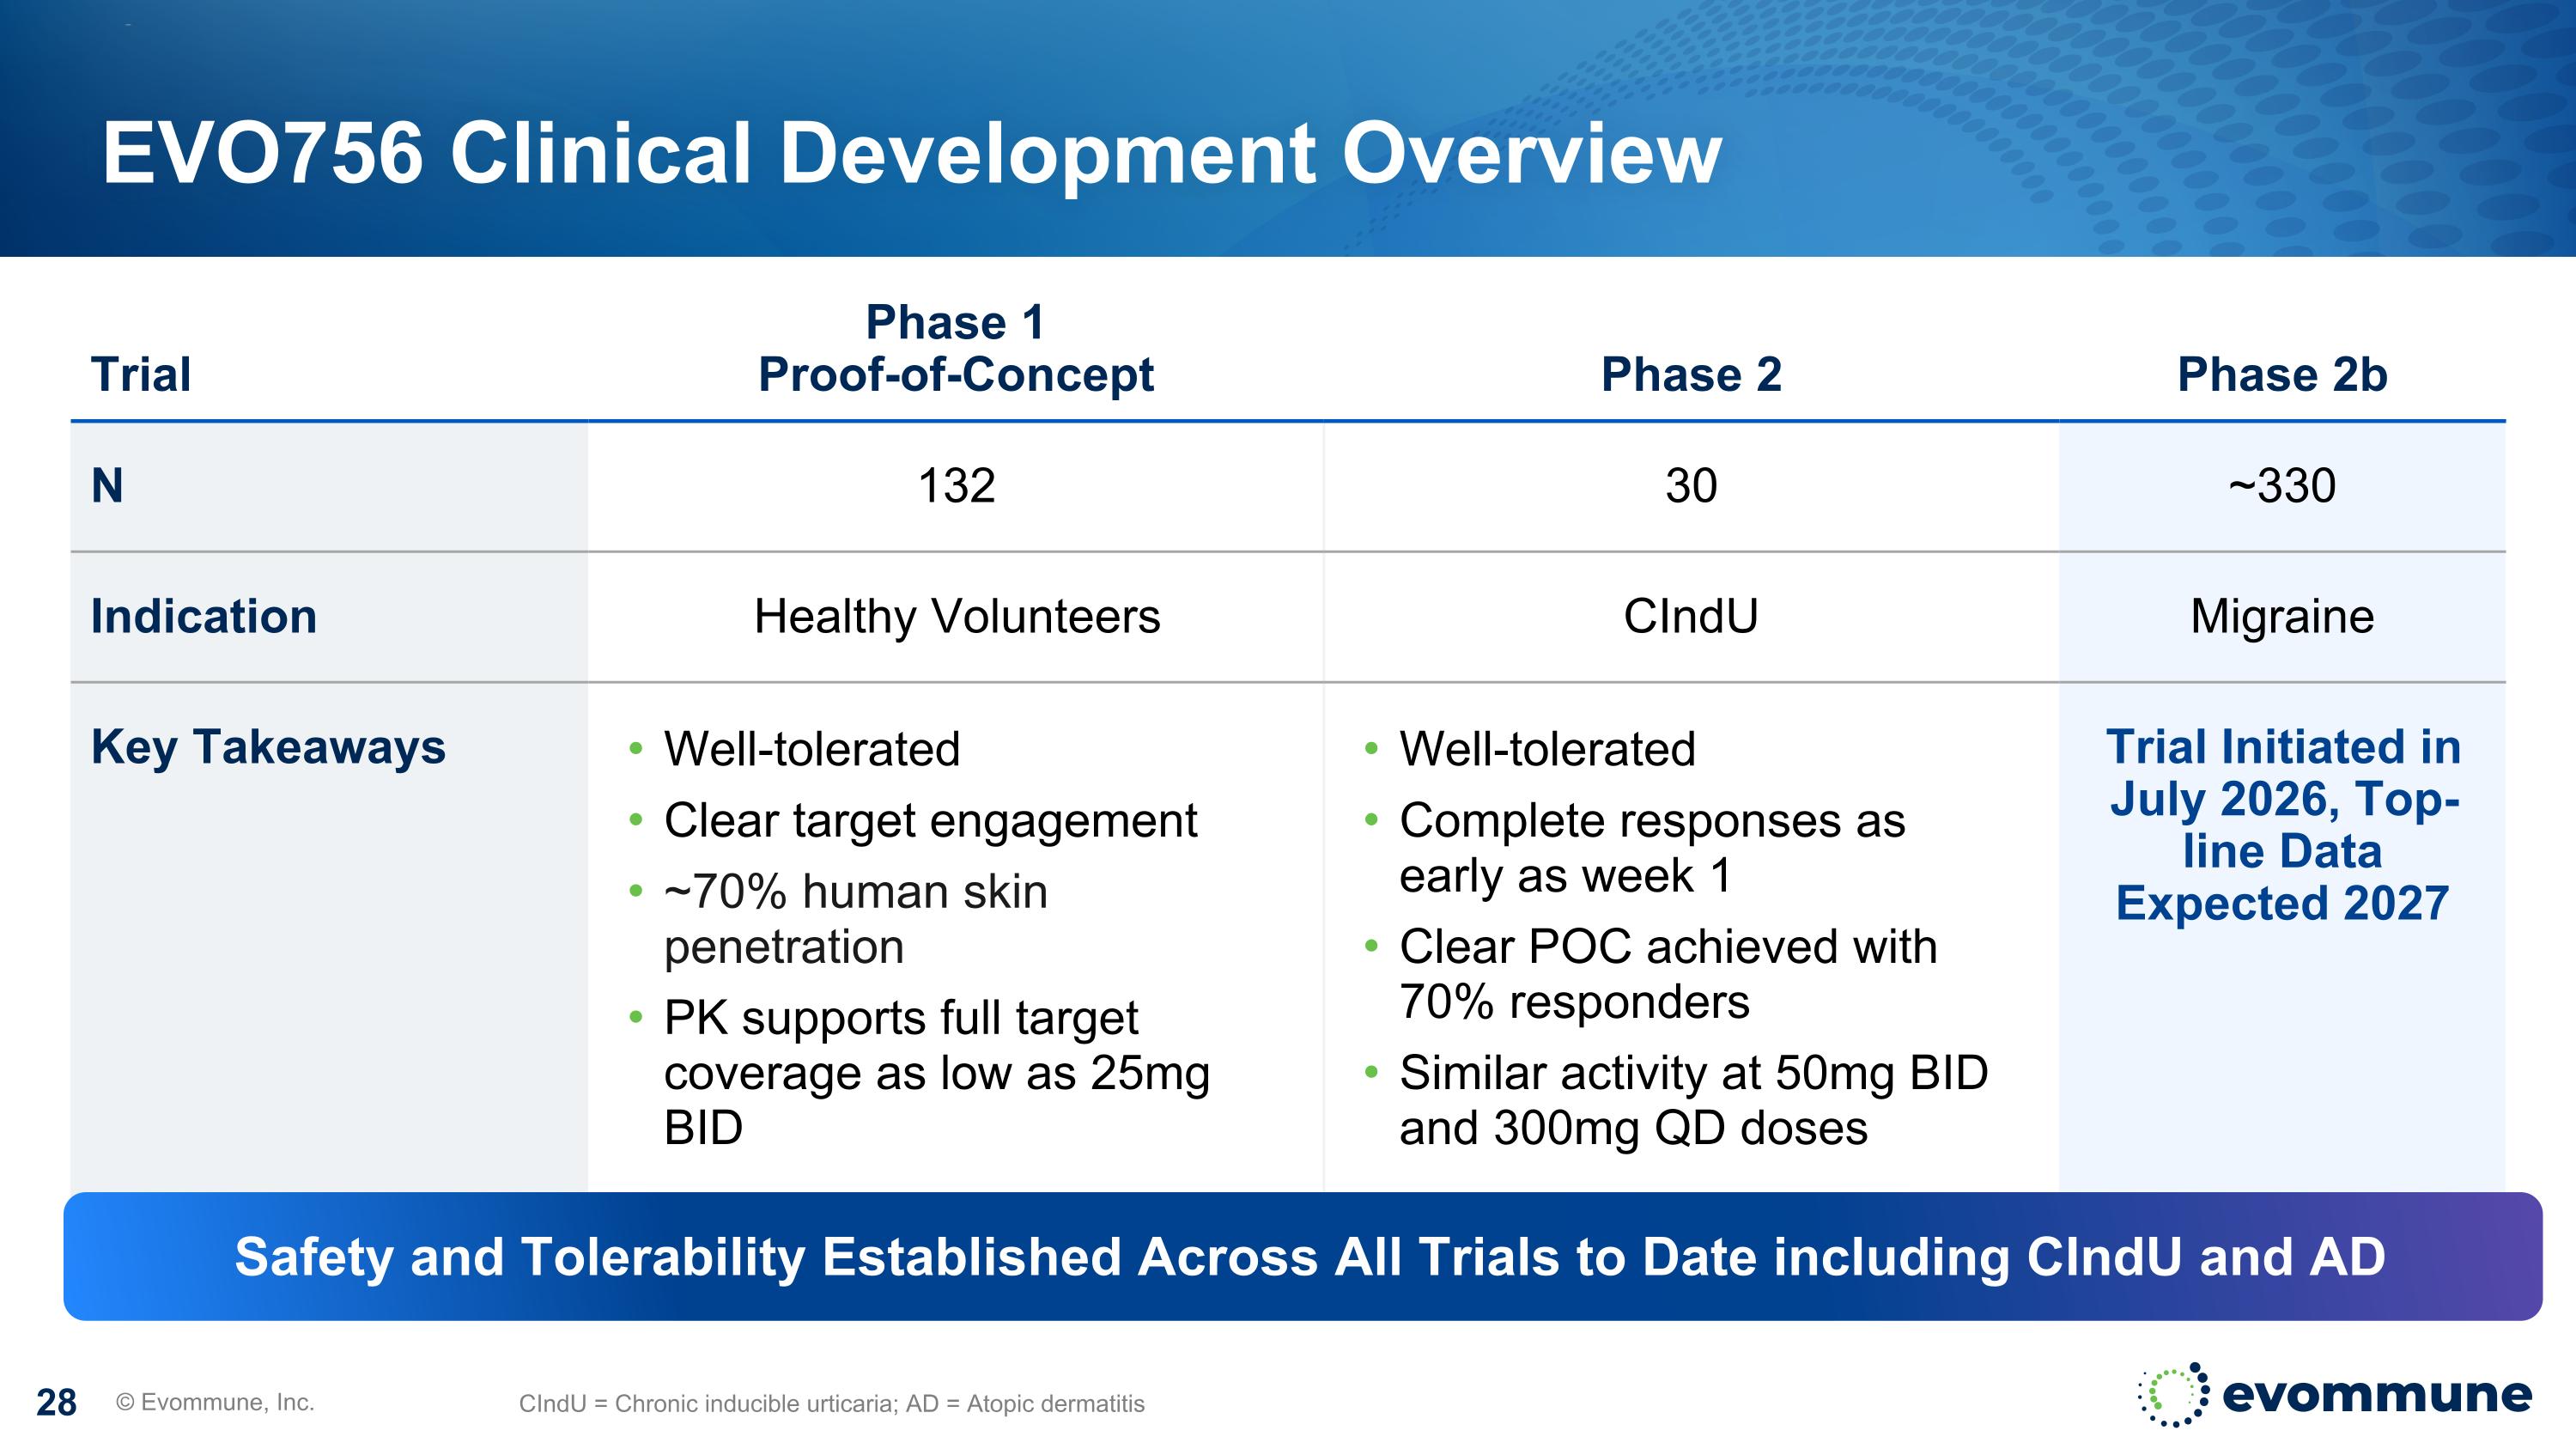
EVO756 Clinical Development Overview © Evommune, Inc. CIndU = Chronic inducible urticaria; AD = Atopic dermatitis Trial Phase 1 Proof-of-Concept Phase 2 Phase 2b N 132 30 ~330 Indication Healthy Volunteers CIndU Migraine Key Takeaways Well-tolerated Clear target engagement ~70% human skin penetration PK supports full target coverage as low as 25mg BID Well-tolerated Complete responses as early as week 1 Clear POC achieved with 70% responders Similar activity at 50mg BID and 300mg QD doses Trial Initiated in July 2026, Top-line Data Expected 2027 Safety and Tolerability Established Across All Trials to Date including CIndU and AD
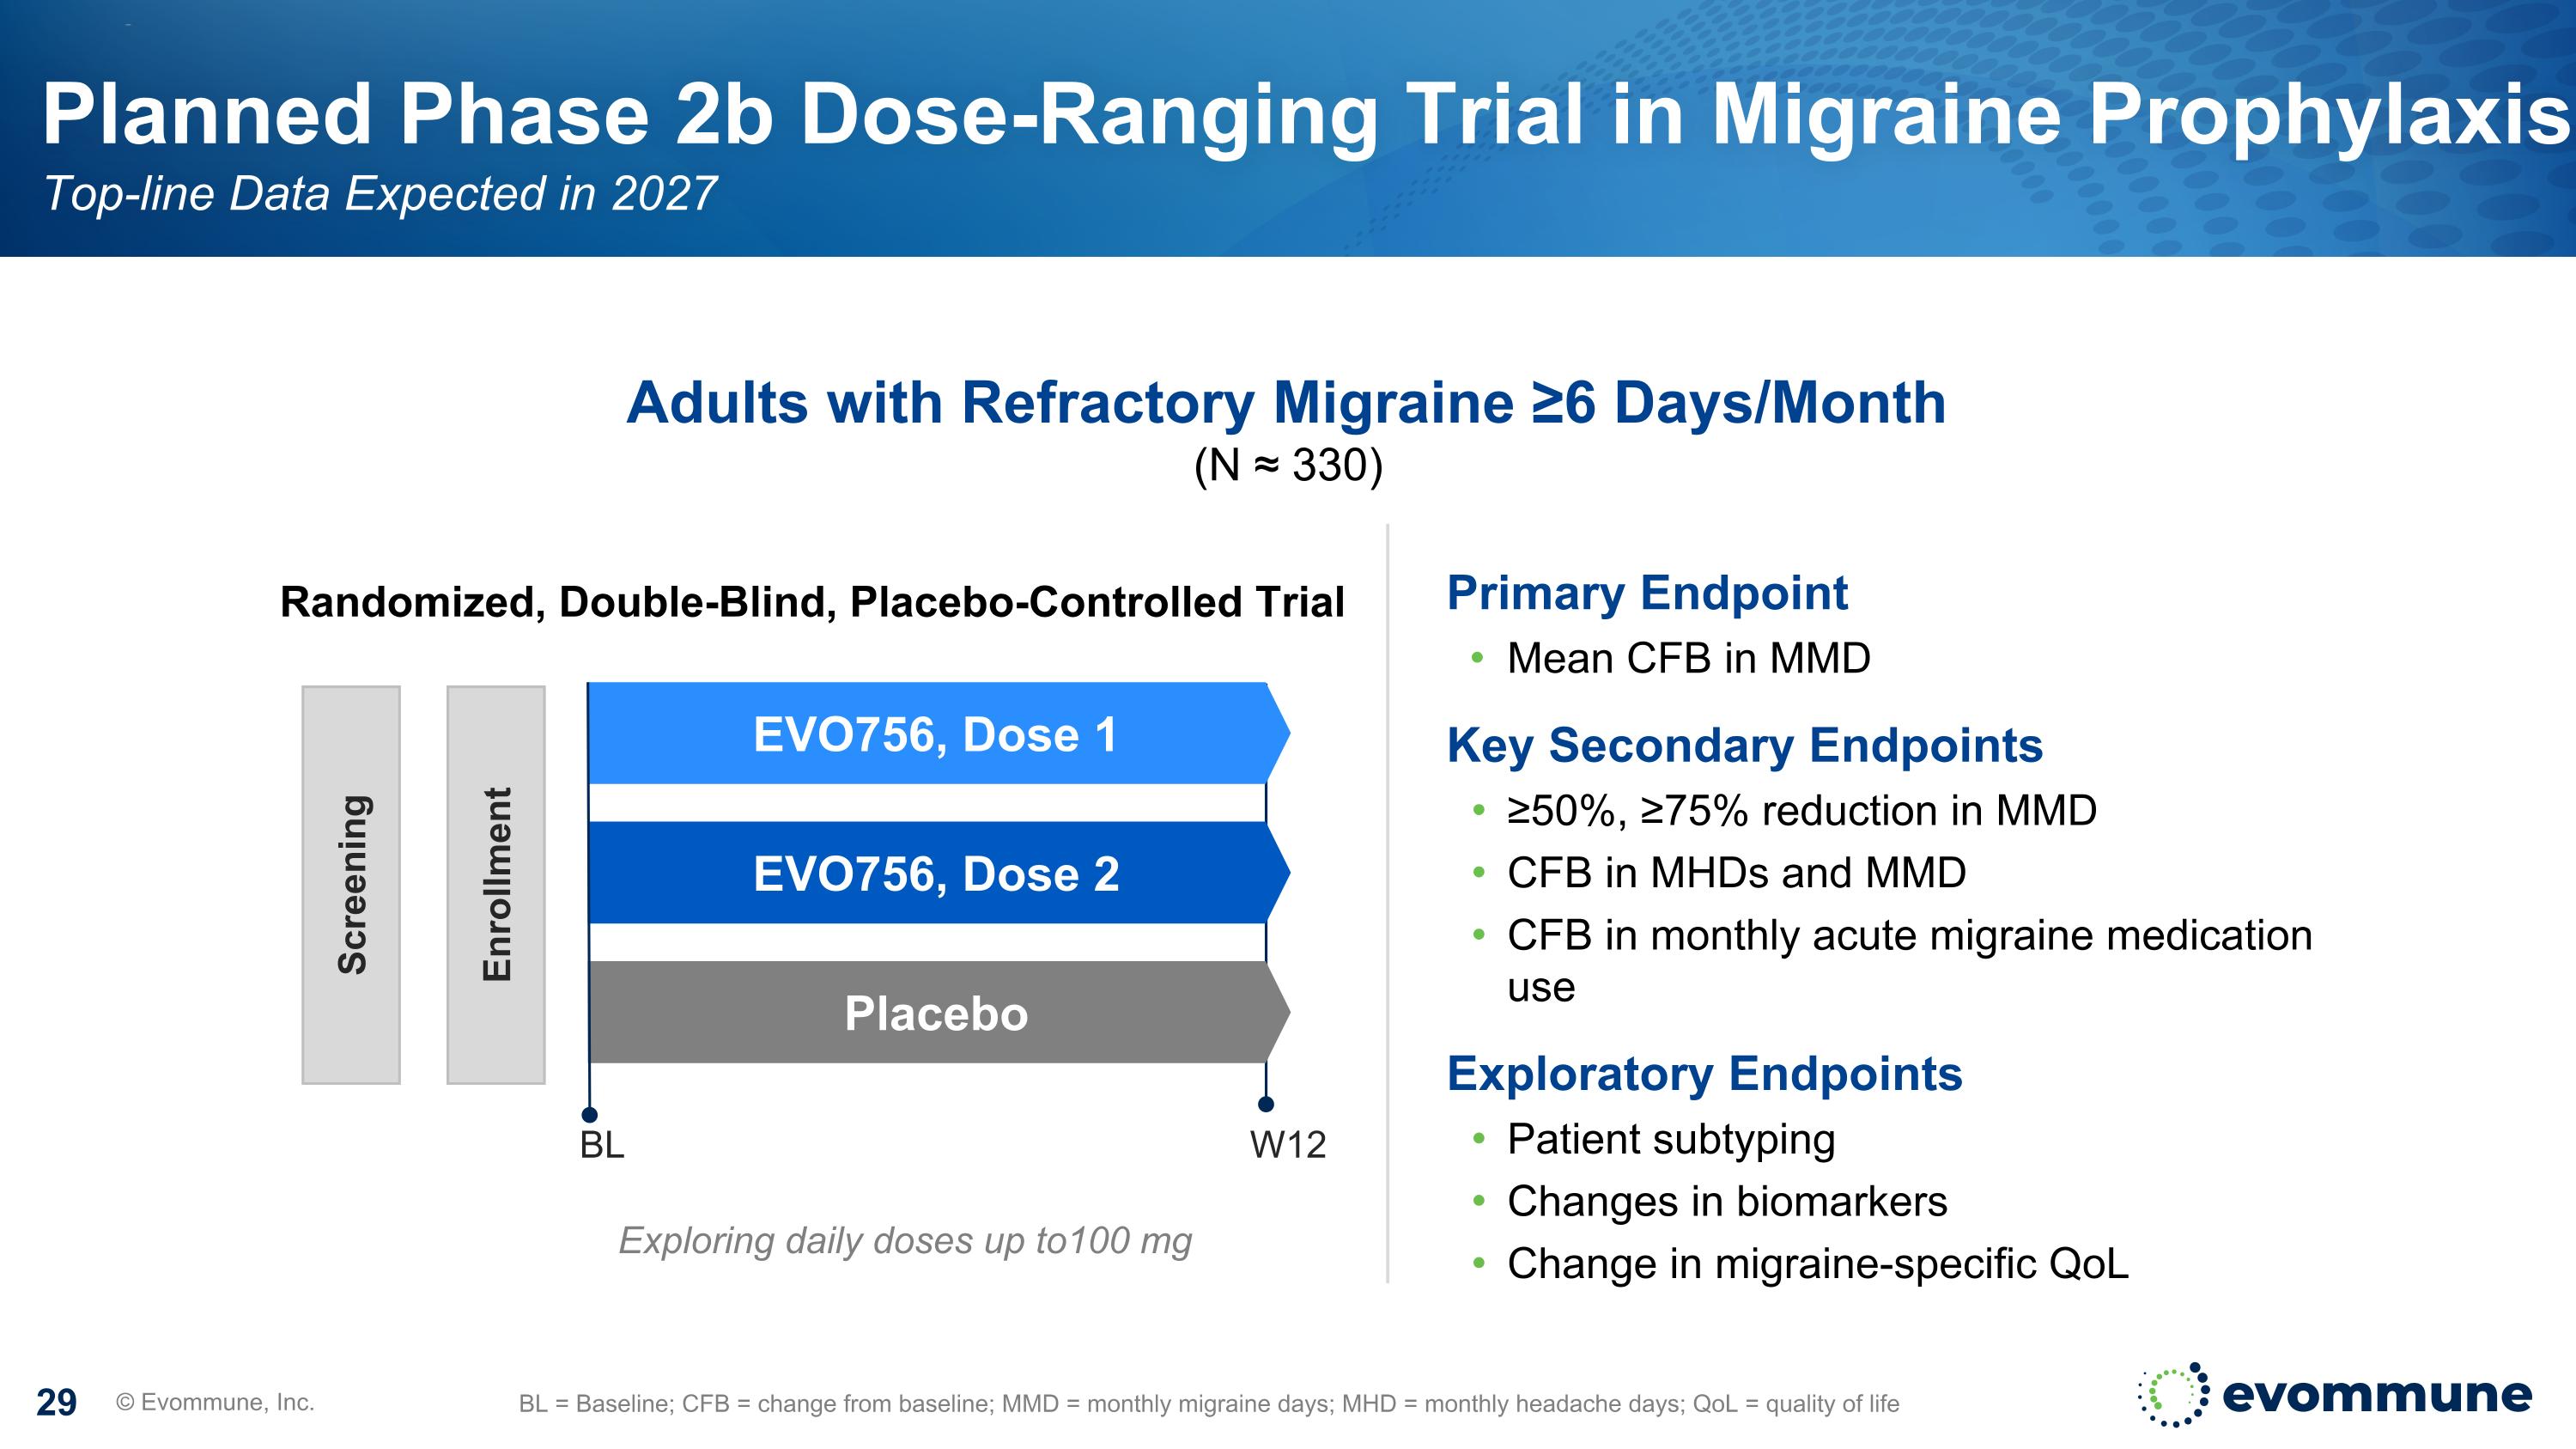
Planned Phase 2b Dose-Ranging Trial in Migraine Prophylaxis Top-line Data Expected in 2027 © Evommune, Inc. BL = Baseline; CFB = change from baseline; MMD = monthly migraine days; MHD = monthly headache days; QoL = quality of life BL Adults with Refractory Migraine ≥6 Days/Month (N ≈ 330) Screening Enrollment W12 EVO756, Dose 1 EVO756, Dose 2 Placebo Randomized, Double-Blind, Placebo-Controlled Trial Primary Endpoint Mean CFB in MMD Key Secondary Endpoints ≥50%, ≥75% reduction in MMD CFB in MHDs and MMD CFB in monthly acute migraine medication use Exploratory Endpoints Patient subtyping Changes in biomarkers Change in migraine-specific QoL Exploring daily doses up to100 mg

EVO646: Oral TLR7/8 Antagonist Potential Best-in-Class Dual Mechanism (Type I Interferon and Pathogenic B-Cell / Autoantibody) for Autoimmune Disease © Evommune, Inc.
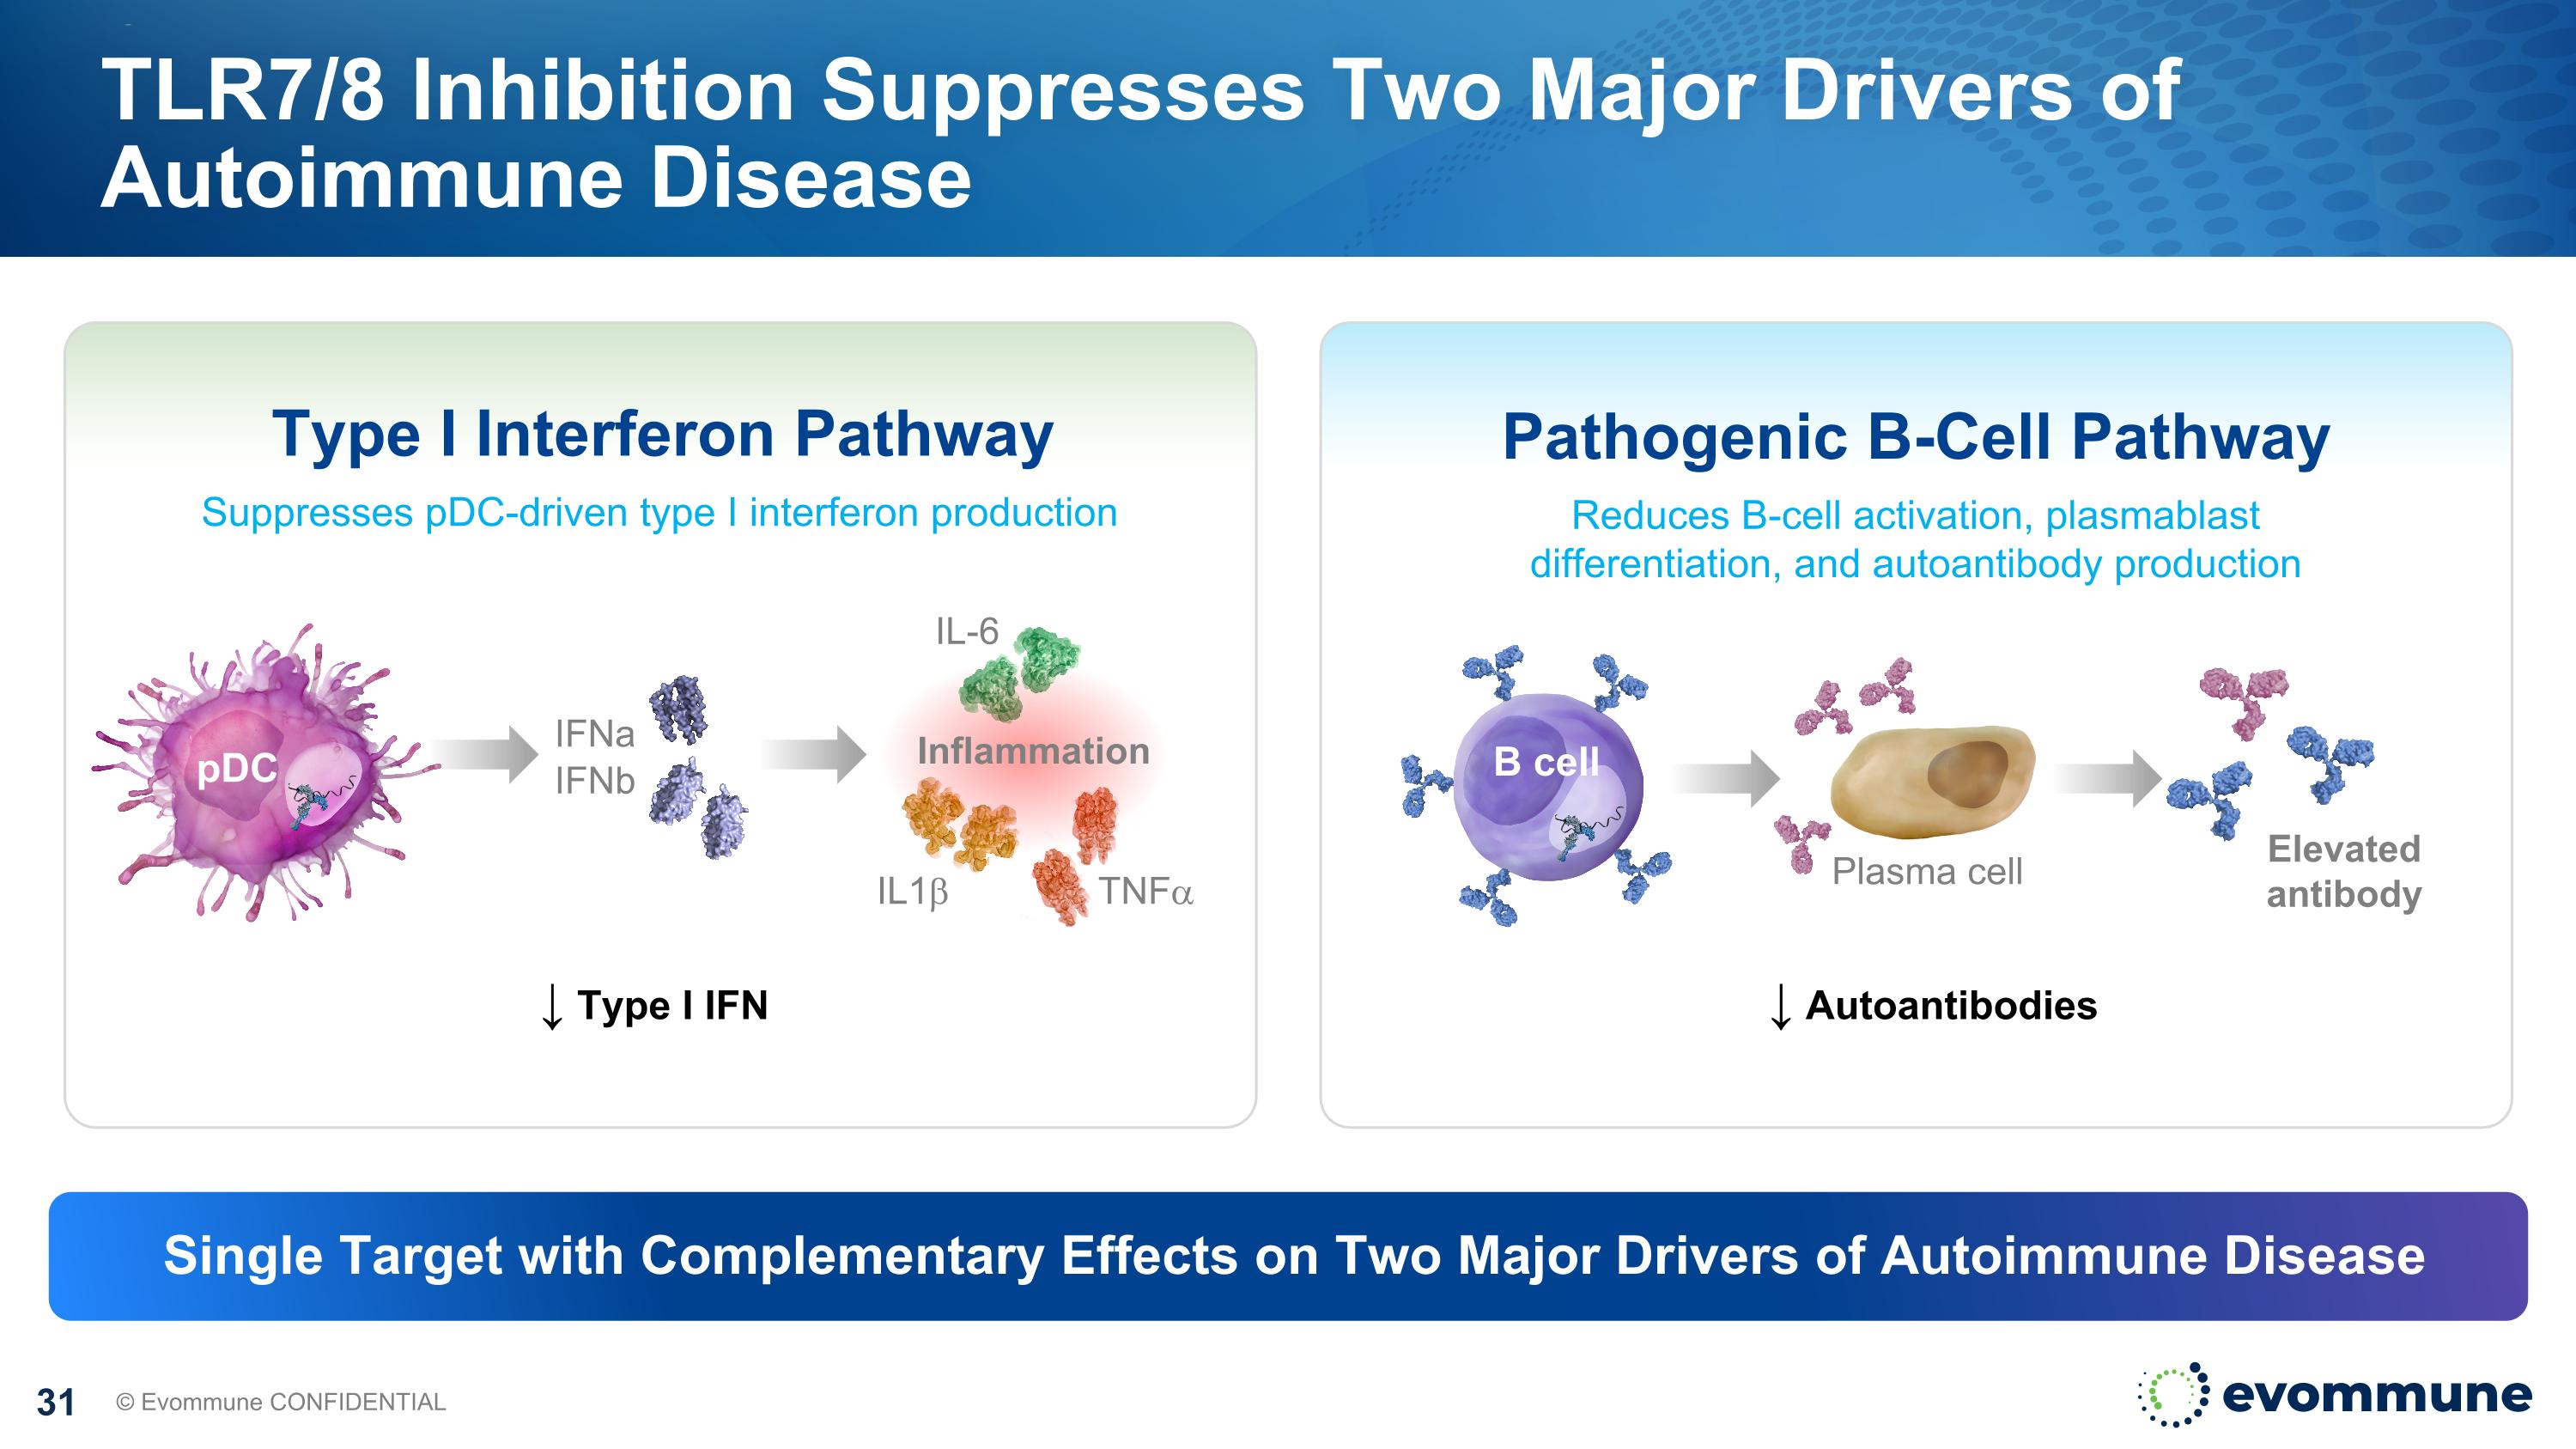
TLR7/8 Inhibition Suppresses Two Major Drivers of Autoimmune Disease © Evommune CONFIDENTIAL Type I Interferon Pathway Pathogenic B-Cell Pathway ↓ Type I IFN ↓ Autoantibodies Elevated antibody B cell IL1b TNFa IL-6 Inflammation IFNa IFNb pDC Plasma cell Single Target with Complementary Effects on Two Major Drivers of Autoimmune Disease Suppresses pDC-driven type I interferon production Reduces B-cell activation, plasmablast differentiation, and autoantibody production
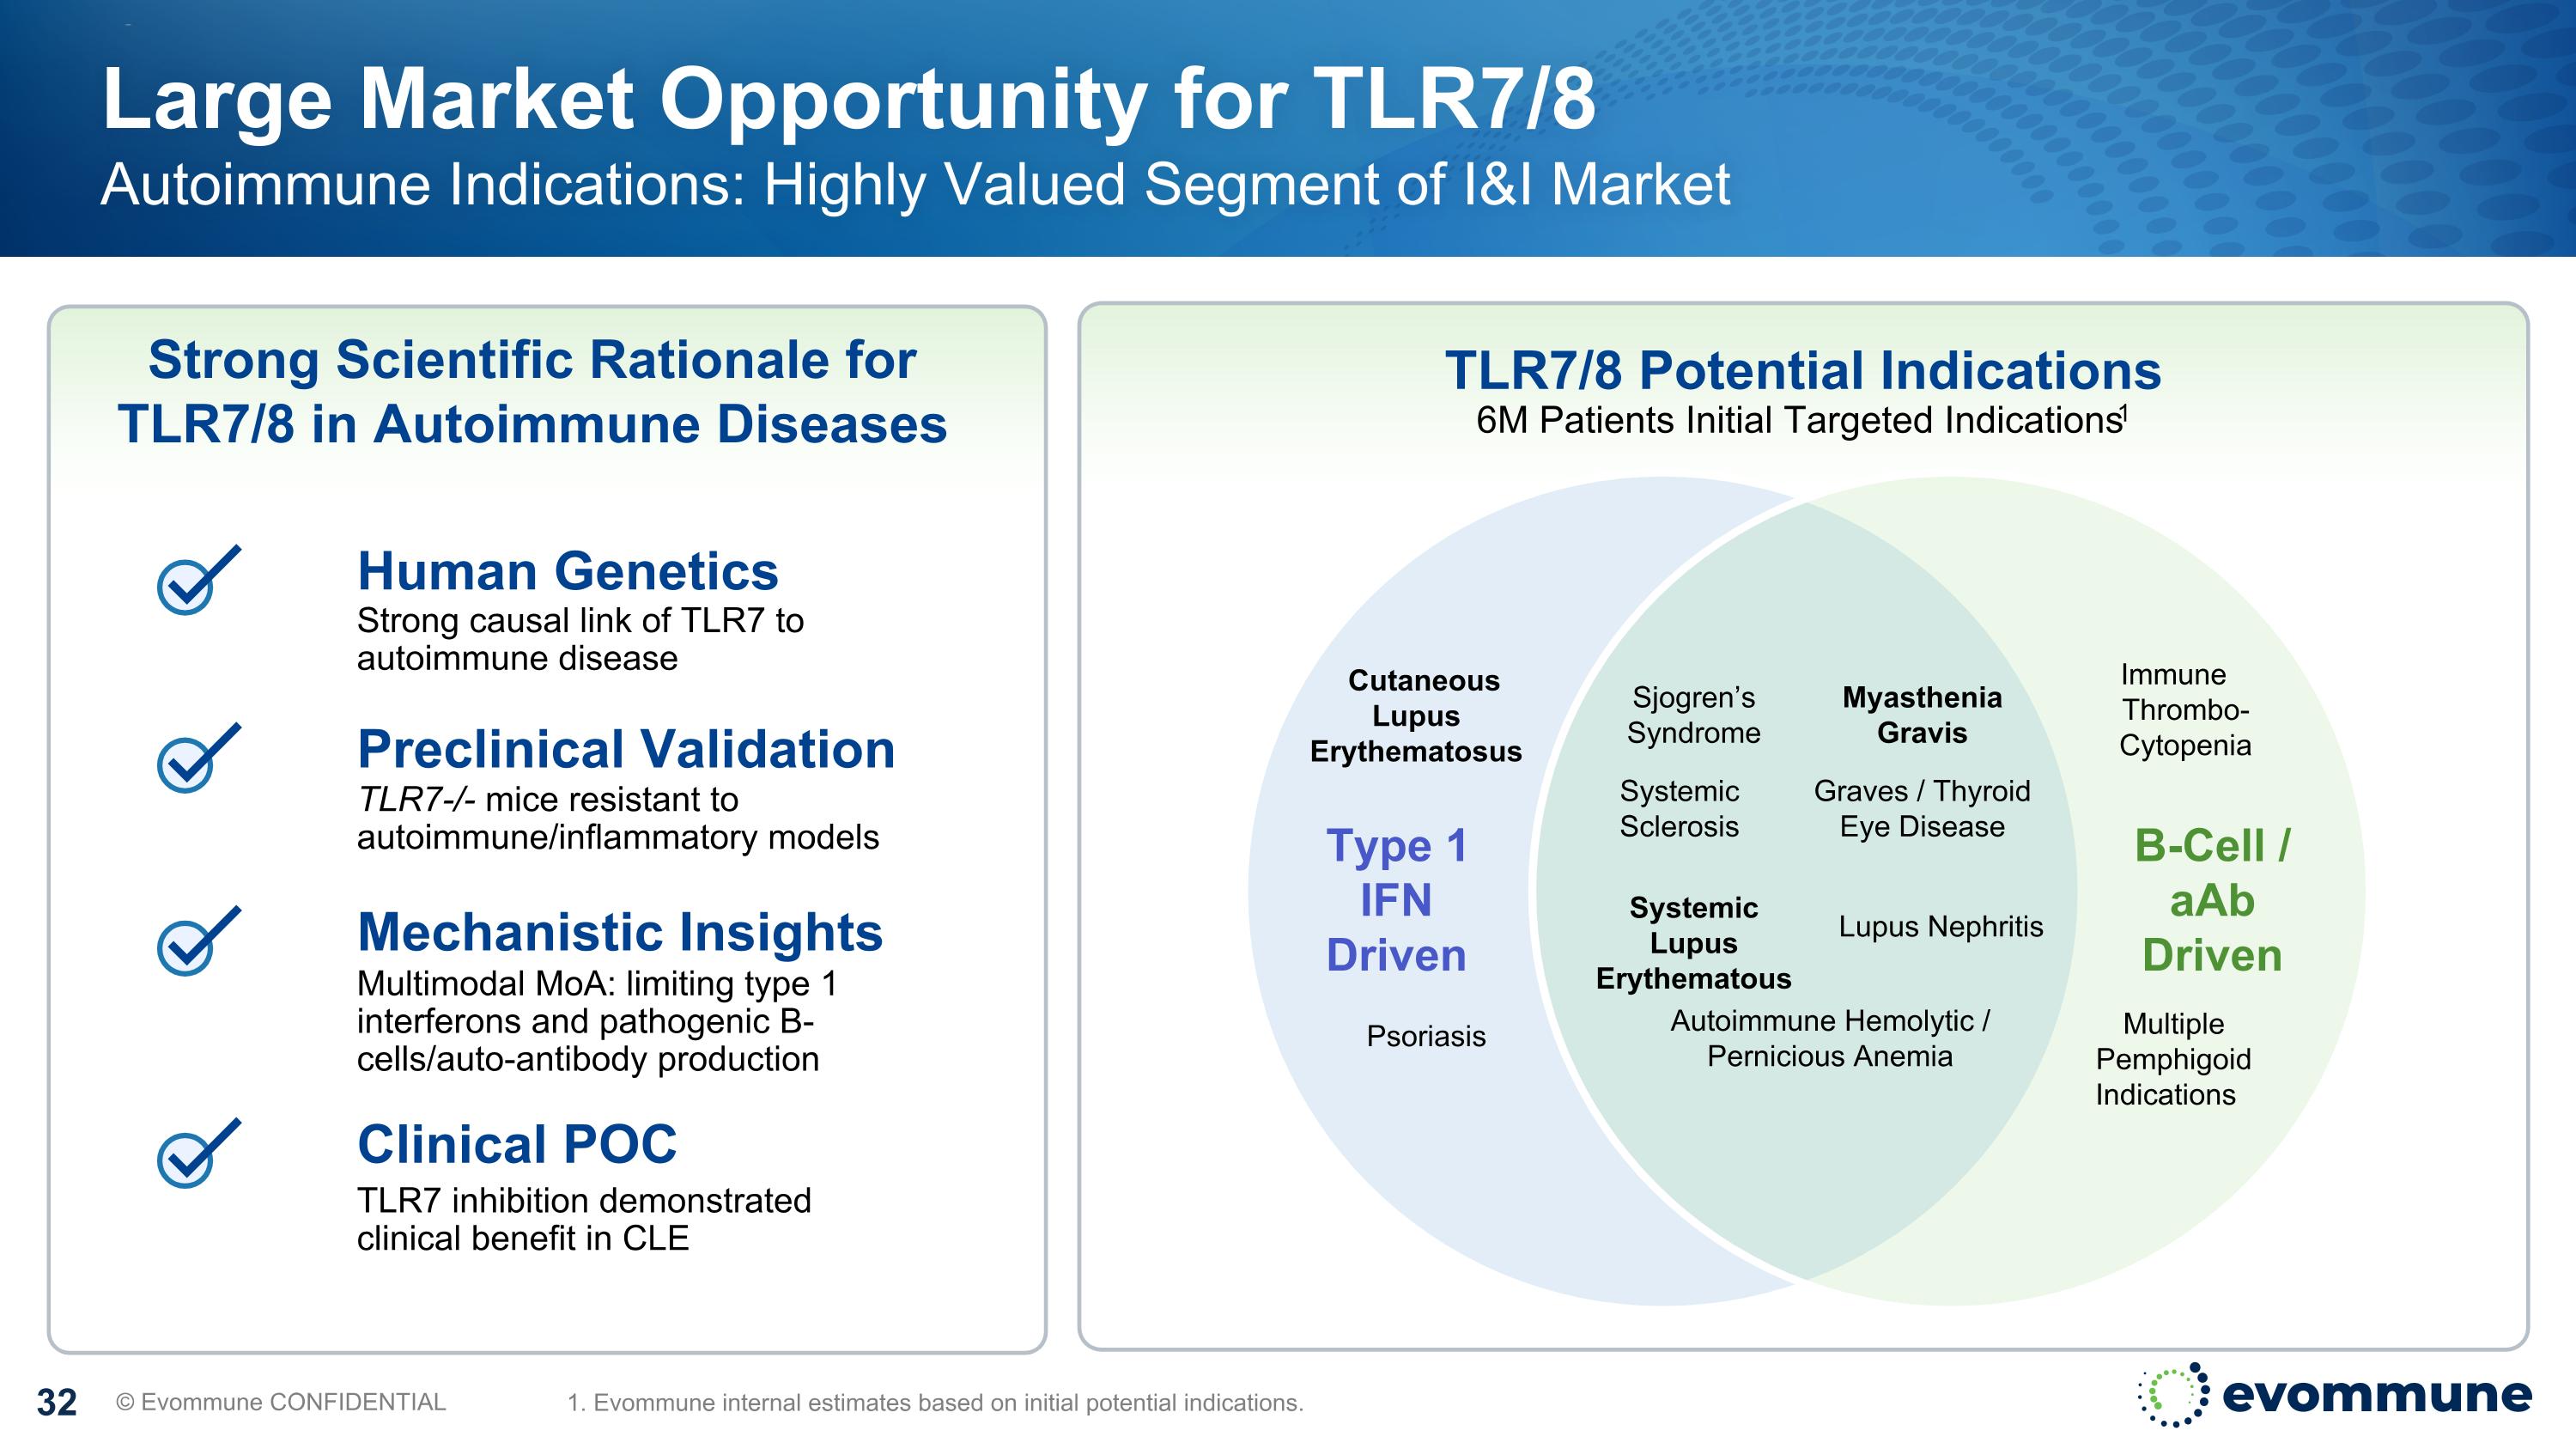
Large Market Opportunity for TLR7/8 Autoimmune Indications: Highly Valued Segment of I&I Market © Evommune CONFIDENTIAL Strong Scientific Rationale for TLR7/8 in Autoimmune Diseases Mechanistic Insights Human Genetics Clinical POC Preclinical Validation Strong causal link of TLR7 to autoimmune disease TLR7-/- mice resistant to autoimmune/inflammatory models Multimodal MoA: limiting type 1 interferons and pathogenic B-cells/auto-antibody production TLR7 inhibition demonstrated clinical benefit in CLE TLR7/8 Potential Indications 6M Patients Initial Targeted Indications1 Type 1 IFN Driven B-Cell / aAb Driven Psoriasis Cutaneous Lupus Erythematosus Systemic Lupus Erythematous Graves / Thyroid Eye Disease Systemic Sclerosis Myasthenia Gravis Immune Thrombo- Cytopenia Multiple Pemphigoid Indications Autoimmune Hemolytic / Pernicious Anemia Sjogren’s Syndrome Lupus Nephritis 1. Evommune internal estimates based on initial potential indications.
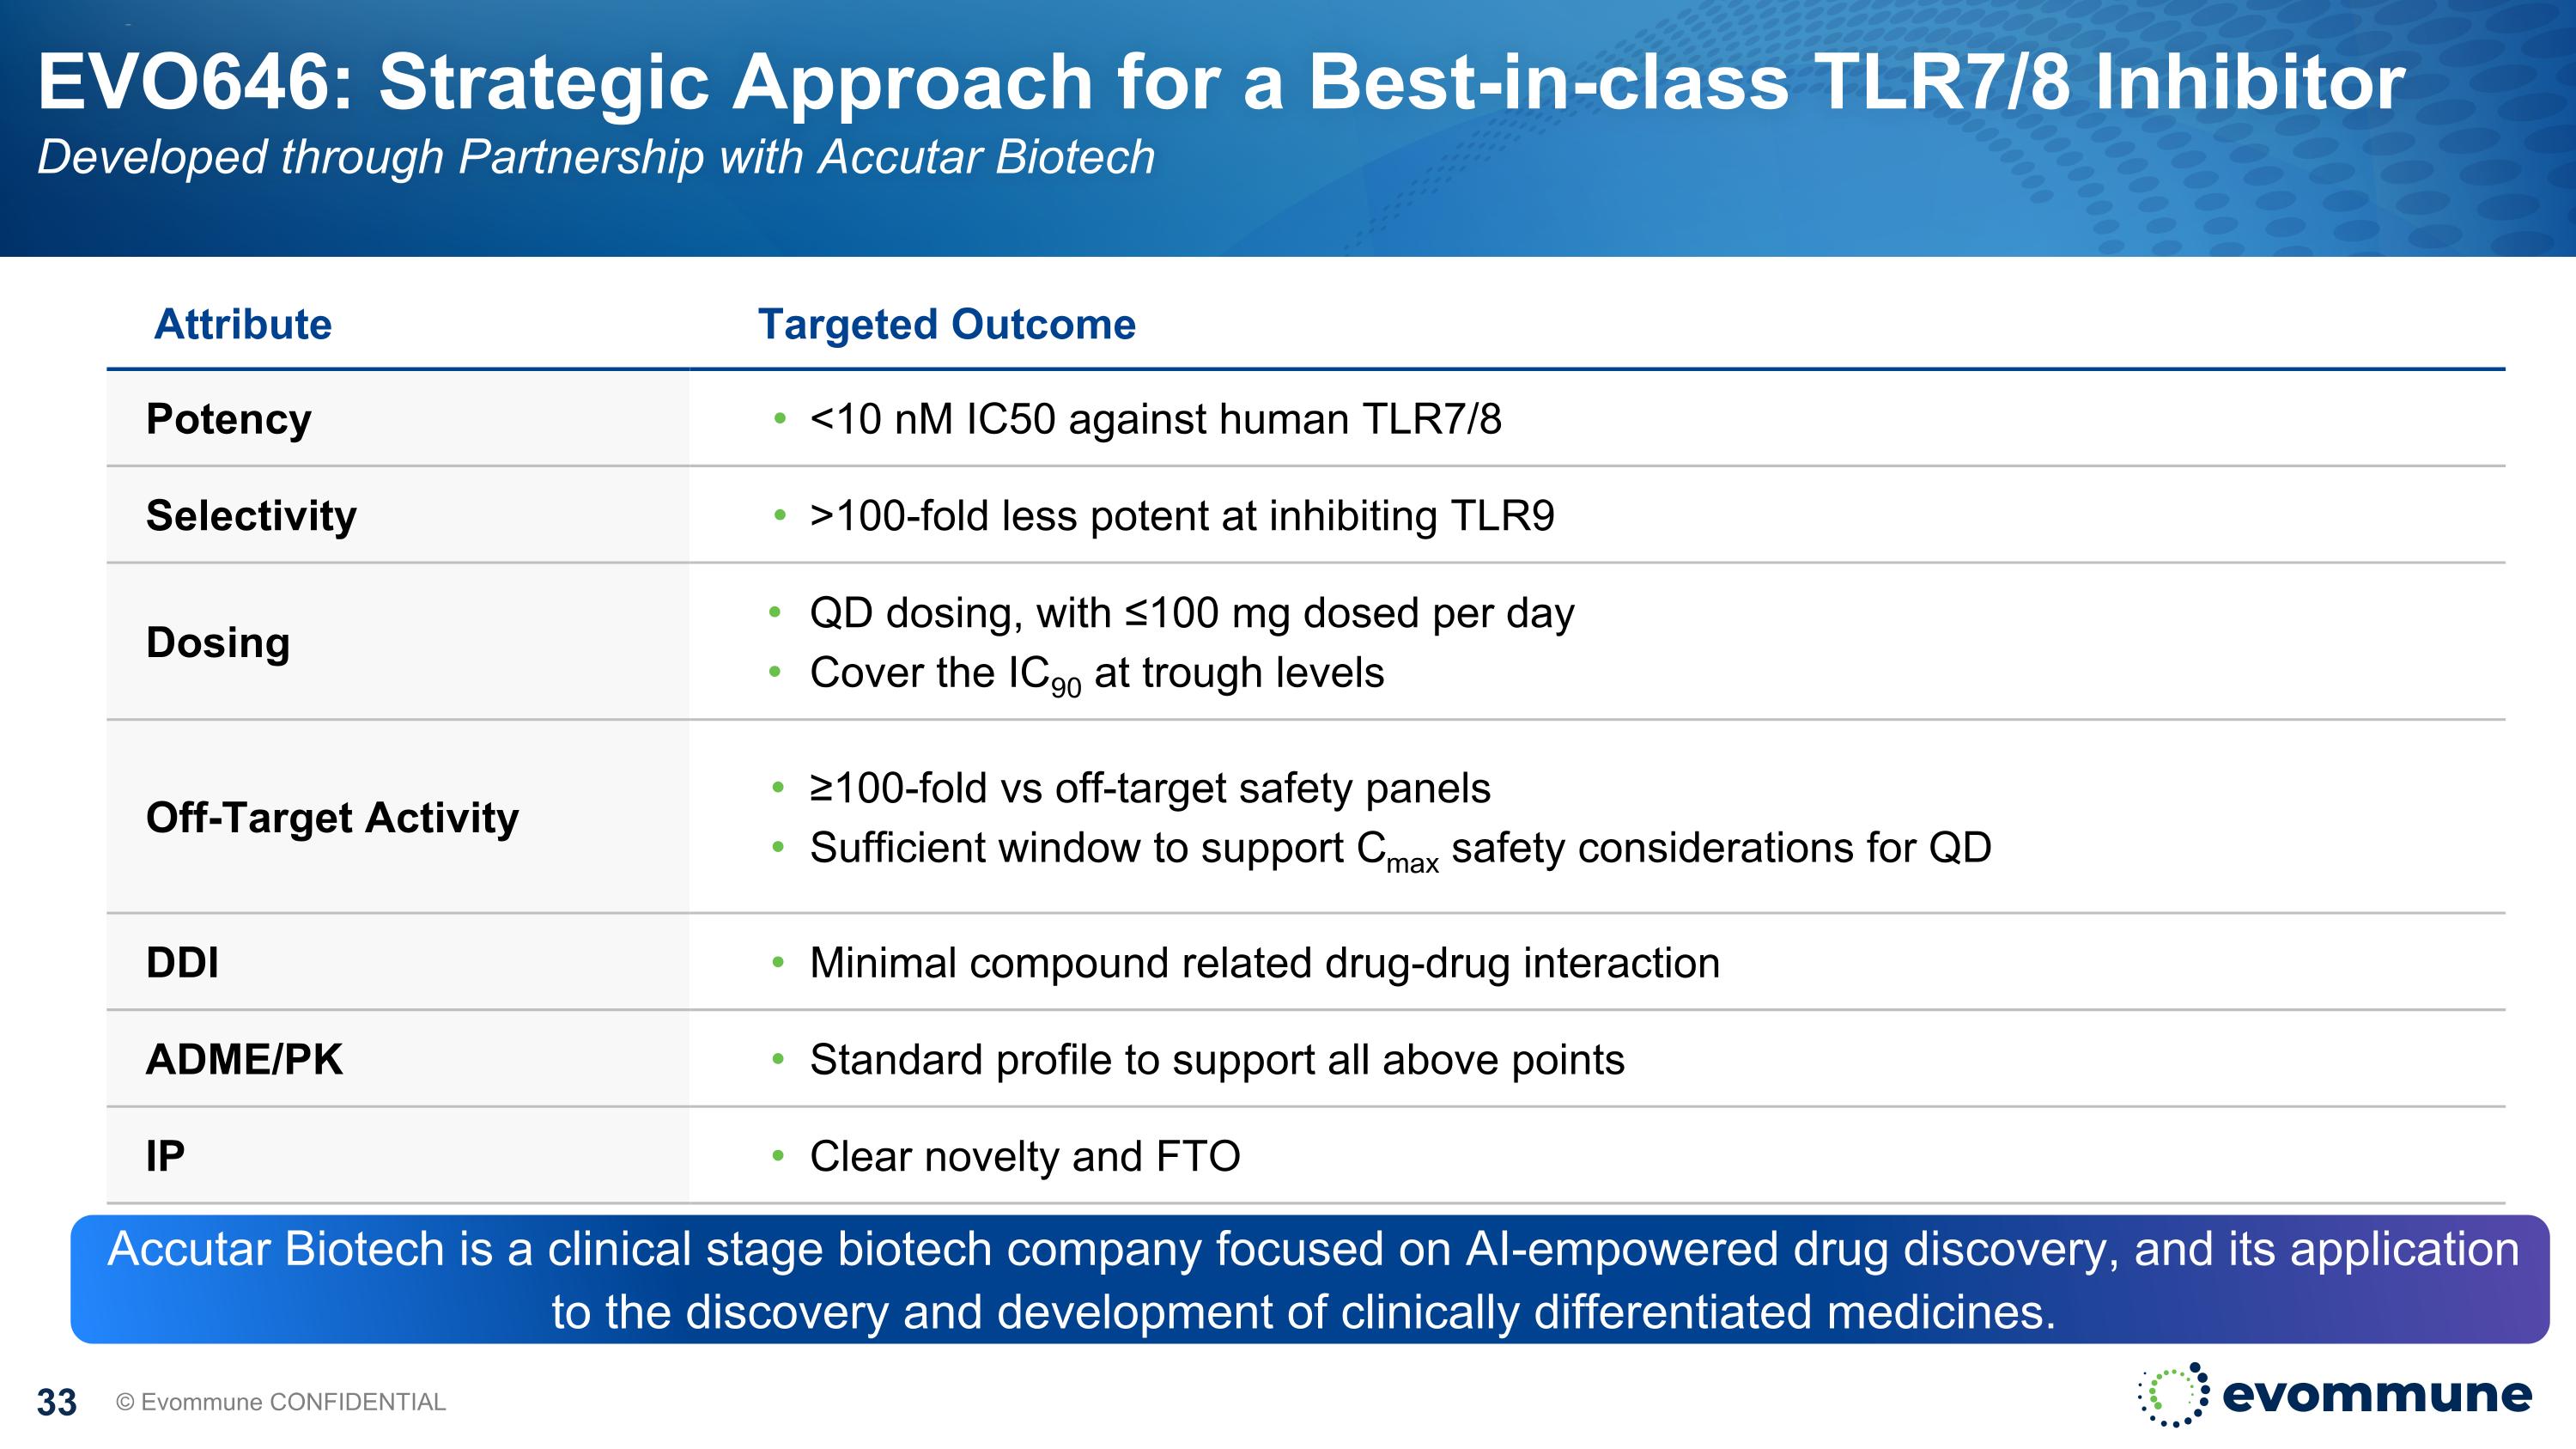
EVO646: Strategic Approach for a Best-in-class TLR7/8 Inhibitor Developed through Partnership with Accutar Biotech © Evommune CONFIDENTIAL Attribute Targeted Outcome Potency <10 nM IC50 against human TLR7/8 Selectivity >100-fold less potent at inhibiting TLR9 Dosing QD dosing, with ≤100 mg dosed per day Cover the IC90 at trough levels Off-Target Activity ≥100-fold vs off-target safety panels Sufficient window to support Cmax safety considerations for QD DDI Minimal compound related drug-drug interaction ADME/PK Standard profile to support all above points IP Clear novelty and FTO Accutar Biotech is a clinical stage biotech company focused on AI-empowered drug discovery, and its application to the discovery and development of clinically differentiated medicines.
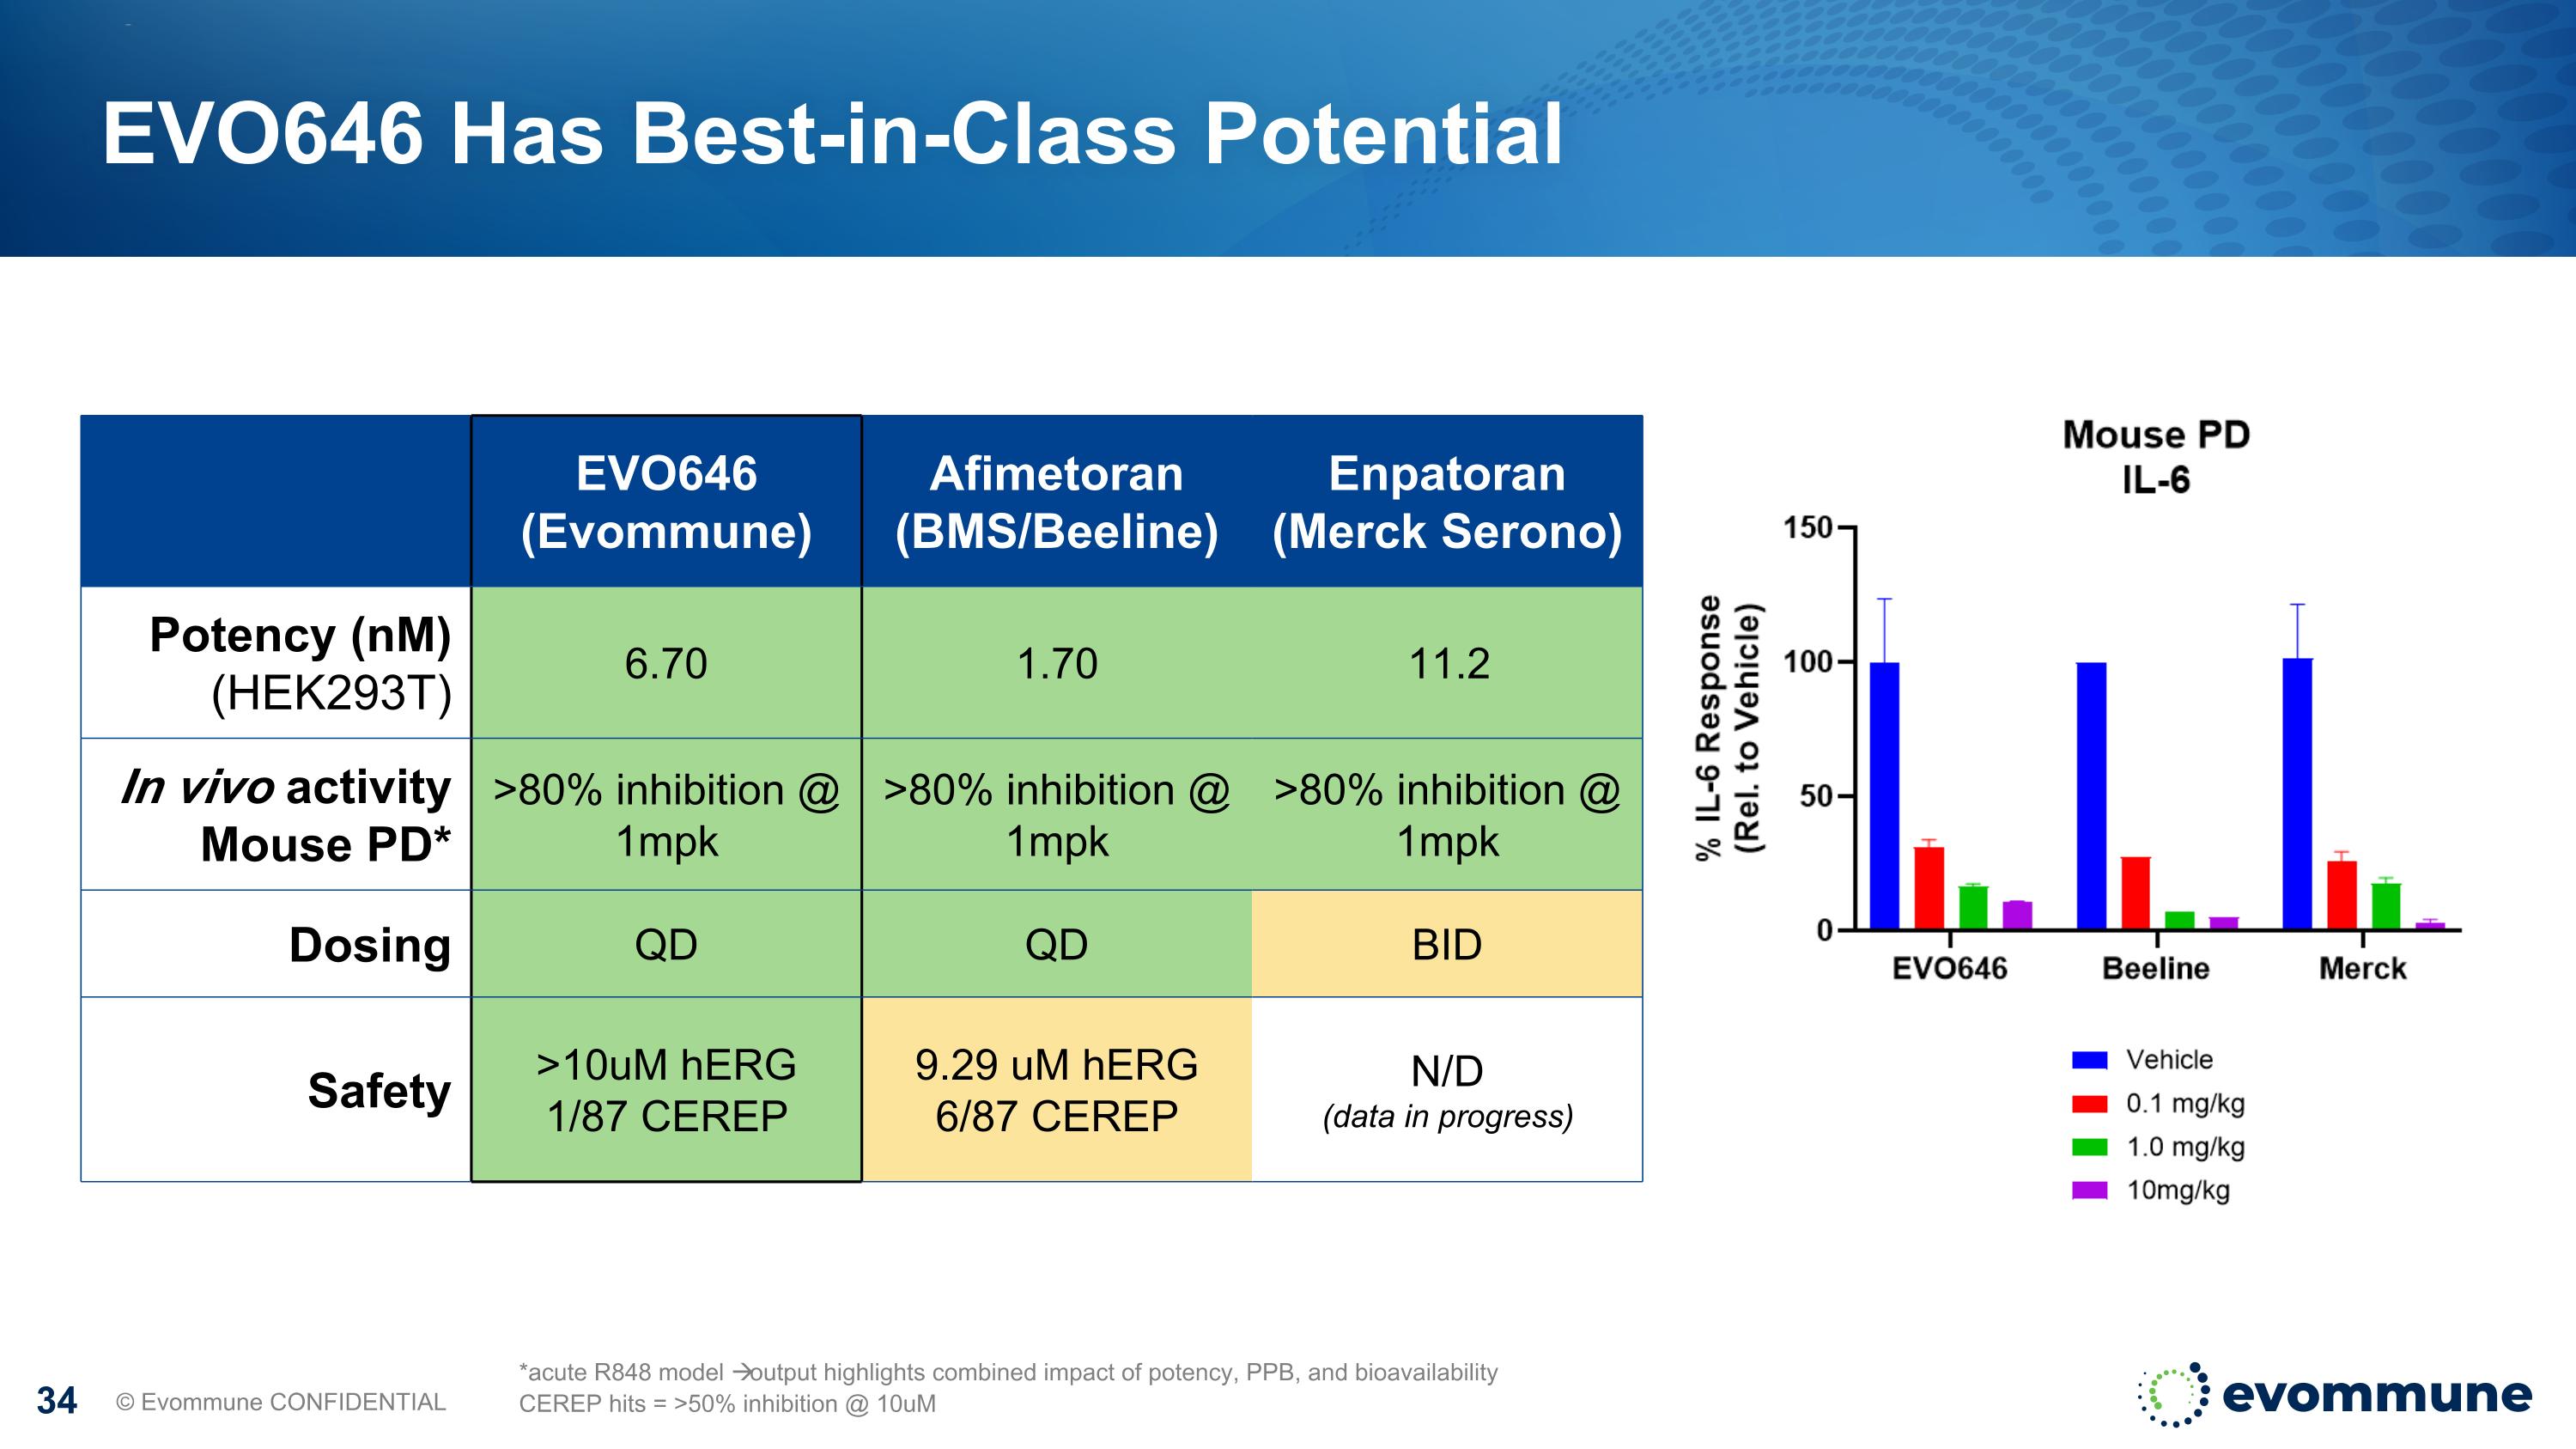
EVO646 Has Best-in-Class Potential EVO646 (Evommune) Afimetoran (BMS/Beeline) Enpatoran (Merck Serono) Potency (nM) (HEK293T) 6.70 1.70 11.2 In vivo activity Mouse PD* >80% inhibition @ 1mpk >80% inhibition @ 1mpk >80% inhibition @ 1mpk Dosing QD QD BID Safety >10uM hERG 1/87 CEREP 9.29 uM hERG 6/87 CEREP N/D (data in progress) © Evommune CONFIDENTIAL *acute R848 model output highlights combined impact of potency, PPB, and bioavailability CEREP hits = >50% inhibition @ 10uM
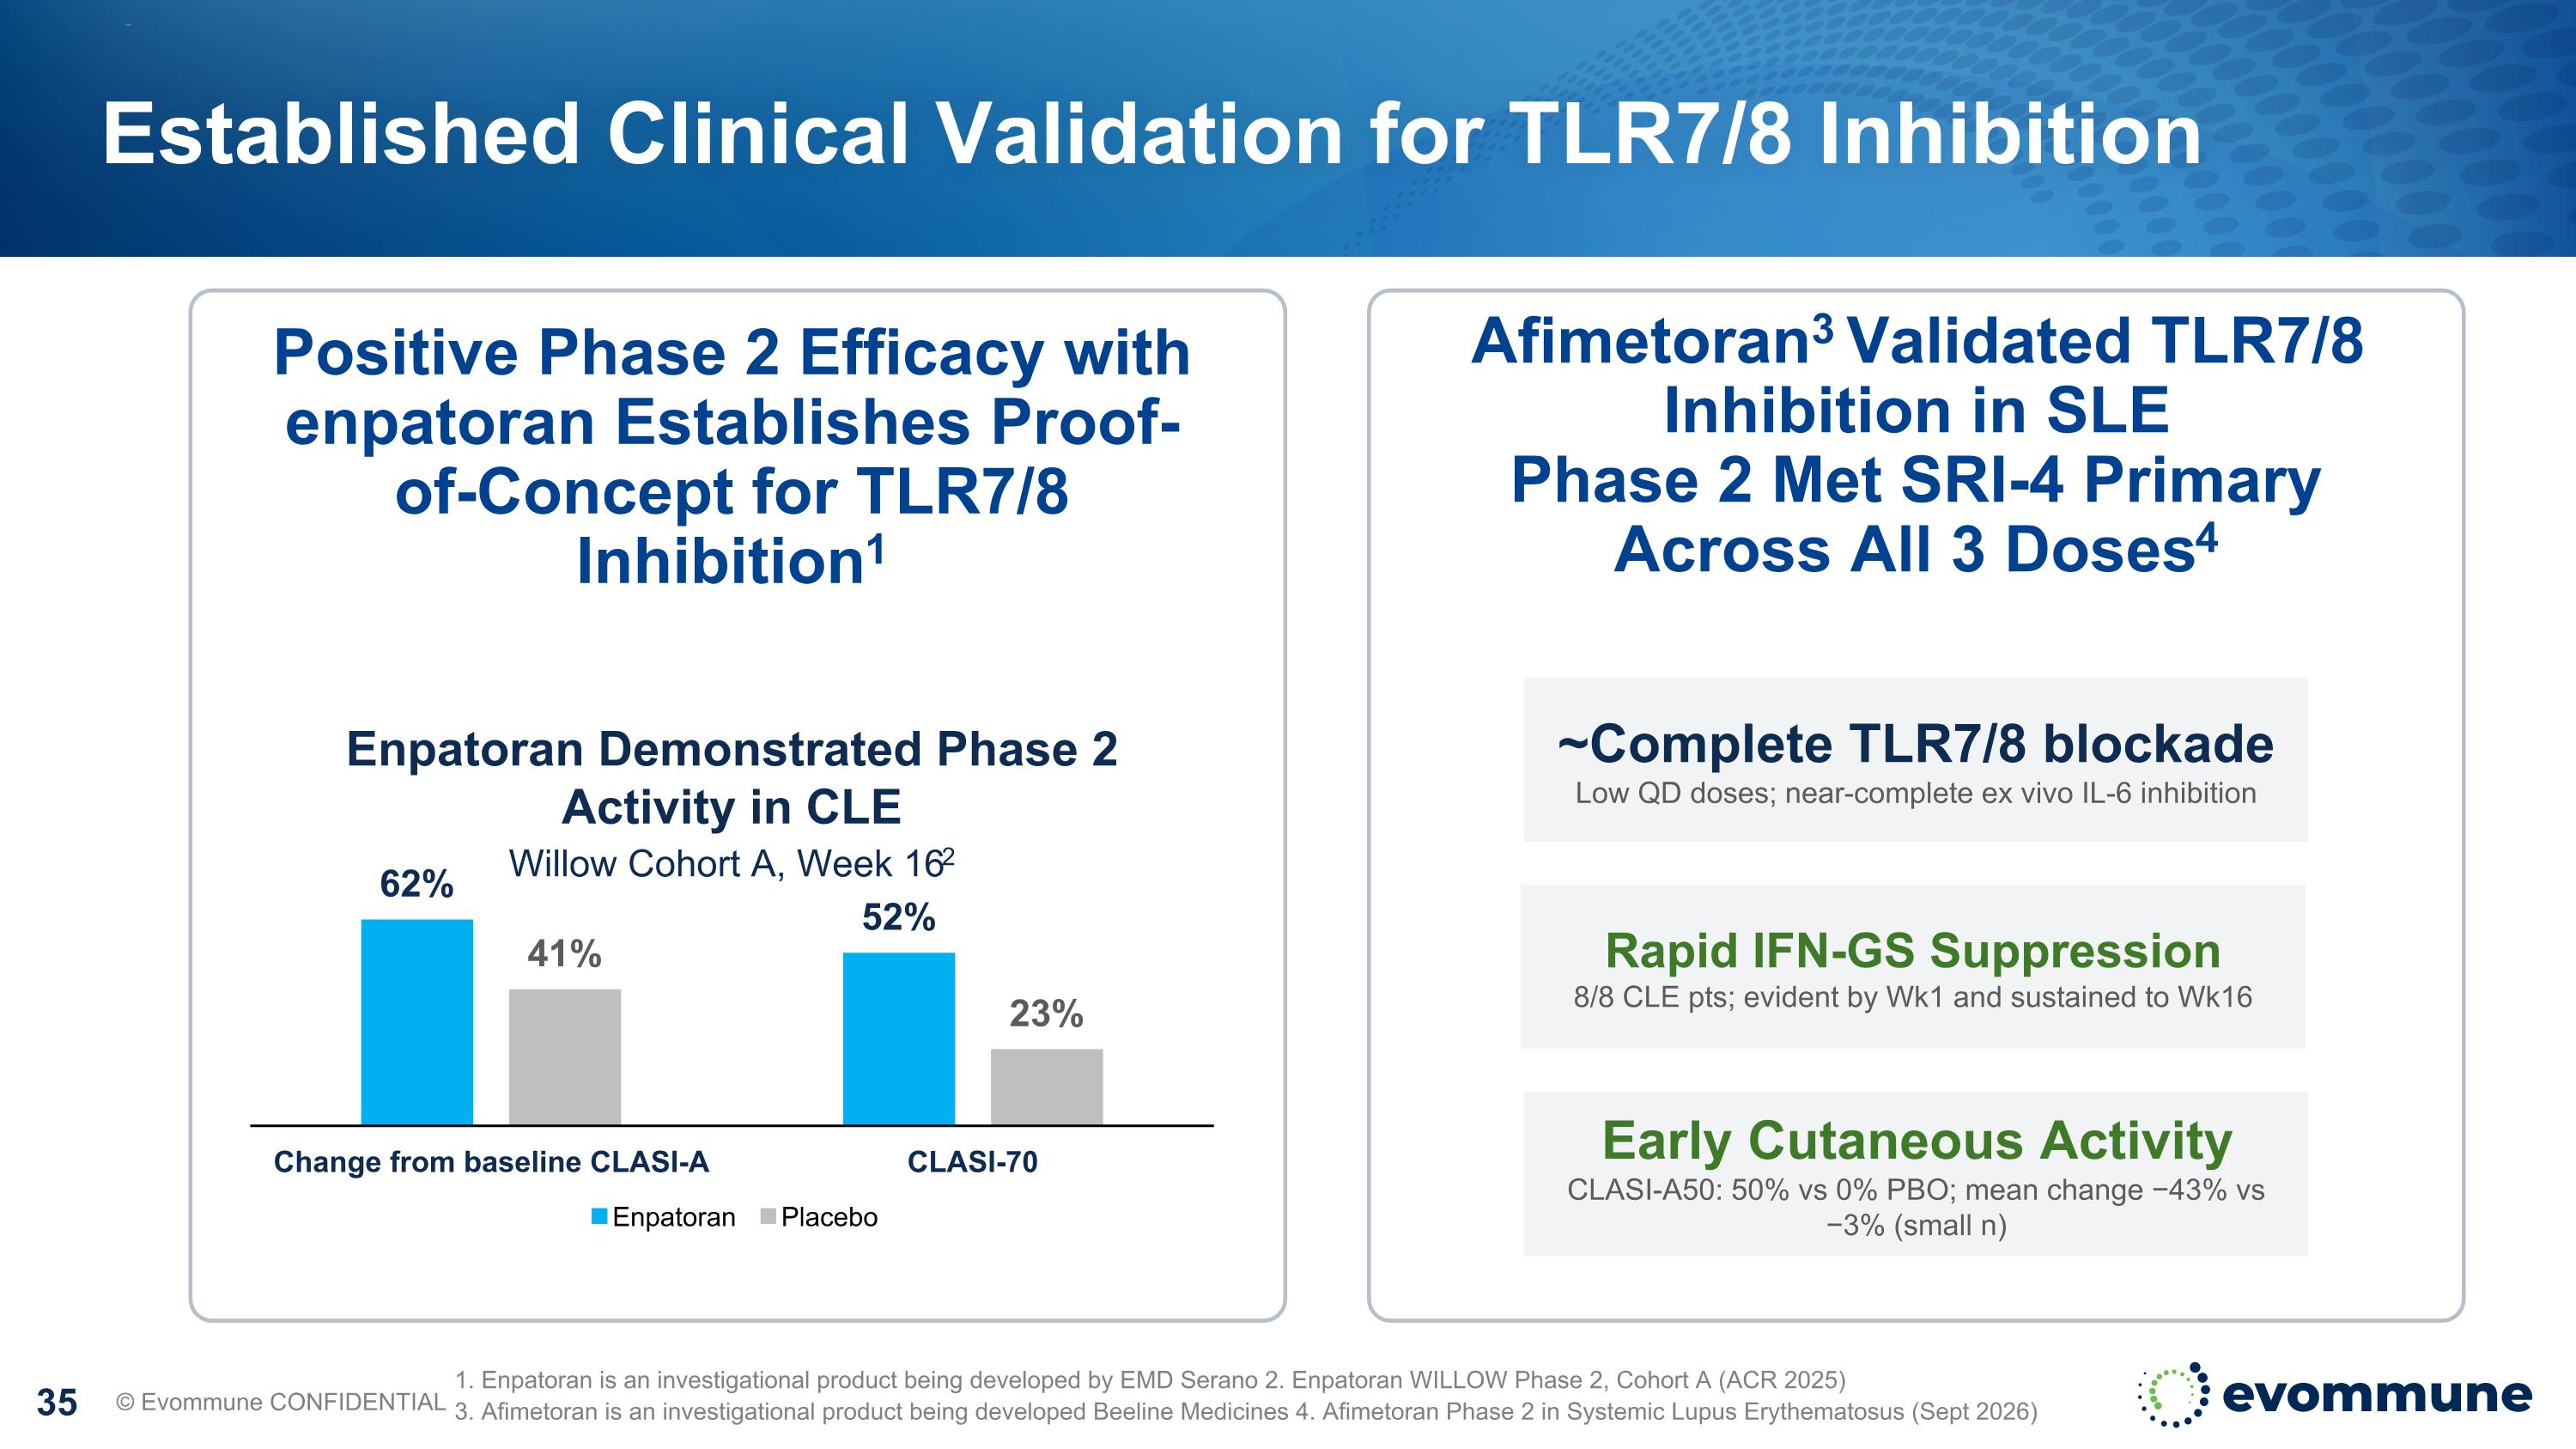
Afimetoran3 Validated TLR7/8 Inhibition in SLE Phase 2 Met SRI-4 Primary Across All 3 Doses4 Established Clinical Validation for TLR7/8 Inhibition © Evommune CONFIDENTIAL 1. Enpatoran is an investigational product being developed by EMD Serano 2. Enpatoran WILLOW Phase 2, Cohort A (ACR 2025) 3. Afimetoran is an investigational product being developed Beeline Medicines 4. Afimetoran Phase 2 in Systemic Lupus Erythematosus (Sept 2026) Positive Phase 2 Efficacy with enpatoran Establishes Proof-of-Concept for TLR7/8 Inhibition1 Enpatoran Demonstrated Phase 2 Activity in CLE Willow Cohort A, Week 162 ~Complete TLR7/8 blockade Low QD doses; near-complete ex vivo IL-6 inhibition Rapid IFN-GS Suppression 8/8 CLE pts; evident by Wk1 and sustained to Wk16 Early Cutaneous Activity CLASI-A50: 50% vs 0% PBO; mean change −43% vs −3% (small n)

Key Milestones Ahead For Evommune (NYSE: EVMN) © Evommune, Inc. ~$287M Cash and Investments; Expected Runway Into 2029 Championing Innovation for Chronic Inflammation EVO301 IL-18BP Plan to initiate Phase 2b in AD with subcutaneous formulation in mid-2027 EVO756 MRGPRX2 Expect top-line data from Phase 2b migraine trial in 2027 EVO646 TLR7/8 Plan to initiate Phase 1 in 1H 2027 Research Anticipate new programs entering the clinic with a steady cadence

Thank You! www.evommune.com © Evommune, Inc.

Appendix © Evommune, Inc.

Proven and Experienced Leadership Team Has Delivered Almost 30 NDAs and BLAs © Evommune, Inc. Footnotes: Acquisition prices from press releases Luis Peña Founder, President & CEO Eugene Bauer, MD Founder, CMO Kyle Carver, MBA CFO Greg Moss, Esq CBO & CLO Jeegar Patel, PhD CSO Janice Drew, MPH Chief of Development Operations Lou Sehl, PhD SVP, Technical Operations Daniel Burge, MD SVP, Clinical Development Leadership in >25 Companies Key Roles in Almost 30 NDA / BLAs (Acquired by Eli Lilly for $1.1B) (Acquired by Sanofi for $1.9B) (Acquired by GlaxoSmithKline for $2.9B) (Acquired by LEO Pharma for $288M) (Acquired by Bristol Myers Squibb for $13.1B) (Acquired by Eli Lilly for $6.5B) (Acquired by Stiefel for $930M) (Acquired by Angiotech for ~$50M) Mark Jackson, MD SVP, Clinical Development